Related Experiment Video
Updated: May 13, 2026


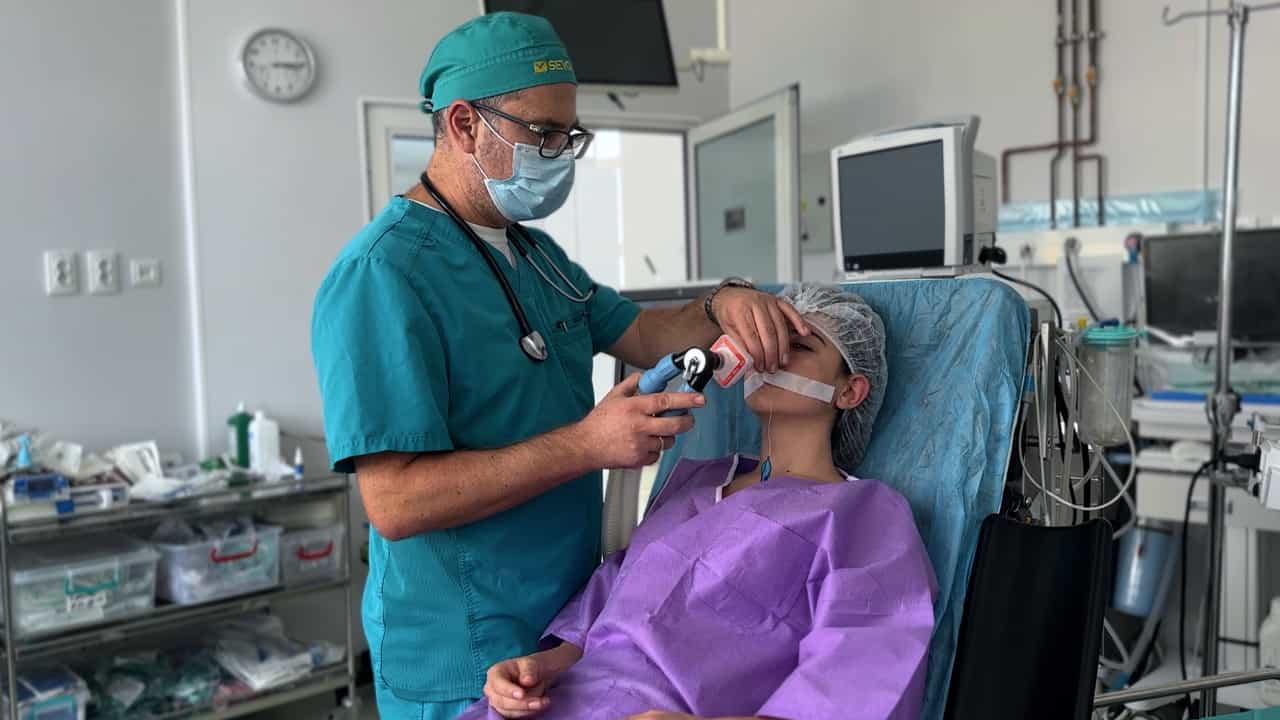
Topical Airway Anesthesia for Awake-endoscopic Intubation Using the Spray-as-you-go Technique with High Oxygen Flow
Published on: January 13, 2017
Oxygen supplementation during awake fibreoptic bronchoscopy in a Nigerian tertiary hospital
U U Onakpoya1, O Adewole, A B Ogunrombi
1Cardiothoracic Surgery Unit,Department of Surgery, Obafemi Awolowo University, Ile- Ife 220005, Nigeria.

Background:
Examination of the airway is necessary in a wide variety of conditions. This study was carried out to determine the need for oxygen supplementation during the conduct of flexible fibreoptic bronchoscopy on the awake patient.
Study Design:
A prospective study of consecutive consenting patients requiring awake flexible bronchoscopy between January 2010 and December 2011 using a fibreoptic bronchoscope in the study centre was conducted. With the aid of transcutaneous pulse oximetry, baseline oxygen saturation values were recorded as well as at the various stages of the procedure as well as during brush cytology, washings, biopsy, transbronchial biopsies and transbronchial needle aspirations and 5, 15 and 30 minutes post-procedure. Data was analysed using SPSS 16 and significant values were taken at pd"0.05.
Results:
Sixty-seven awake fibreoptic bronchoscopies were performed on 61 patients comprising 38 males and 29 females and a mean age of 51.9 ± 18.9 years. The lowest mean SPO2 of 91.2% was attained during brush cytology. Thirty- four patients (50.7%) had the procedure without oxygen supplementation. Supplemental oxygen was required in all seven patients with a baseline SPO2 of d"92% while it was required in 63.2% of patients with baseline SPO2 of 93- 96%. Baseline oxygen saturation was the most important predictor of the need for oxygen supplementation (p= 0.005).
Conclusion:
Routine oxygen supplementation is not mandatory for the safe conduct of flexible bronchoscopy. The baseline oxygen saturation value accurately predicts the need for oxygen administration.

Related Concept Videos
 01:30
Administering Oxygen by Mask
Administering oxygen by mask is a common nursing intervention that provides supplemental oxygen to patients with respiratory distress or chronic lung conditions. This procedure involves delivering oxygen at a specified rate through a face mask connected to an oxygen source.
Equipment
The equipment necessary for this procedure includes:
 01:29
Administering Oxygen by Nasal Cannula
Nasal Cannulas
A nasal cannula is a lightweight tube split into two prongs placed in the nostrils, connected...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...