Related Experiment Video
Updated: May 13, 2026
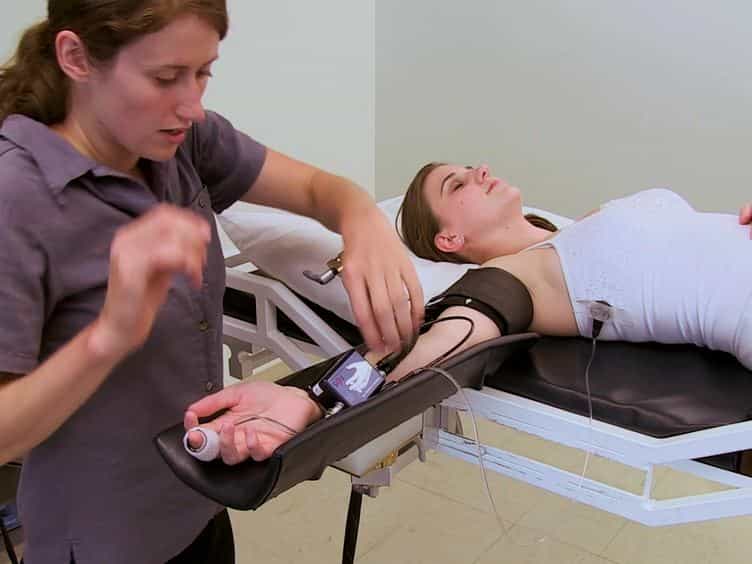

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
History of syncope in the cardiac literature
1UCLA School of Medicine, Los Angeles, CA, USA. dcannom@lacard.com

Insights
Centuries of cardiology literature detail syncope, including vasodepressor syncope, postural orthostatic hypotension, and Morgagni-Stokes-Adams syncope. Modern therapies and clinical guidelines now offer improved care for these conditions.
Area of Science:
- Cardiology
- Clinical Medicine
- Medical History
Background:
- The study reviews historical cardiology literature focusing on syncope.
- Key figures in clinical medicine and physiology contributed to understanding syncope over the past century.
Observation:
- Early clinicians meticulously documented symptoms and signs of vasodepressor syncope, postural orthostatic hypotension, and Morgagni-Stokes-Adams syncope.
- Basic scientists elucidated the underlying physiology of these syncope presentations.
Findings:
- A comprehensive understanding of syncope was established approximately 50 years ago through combined clinical and physiological research.
- Therapeutic advancements, including implantable devices for Morgagni-Stokes-Adams attacks and simpler treatments for other syncope types, have emerged.
Implications:
- The development of clinical guidelines has integrated historical observations and physiological findings, leading to enhanced patient care.
- This historical perspective highlights the progression from clinical description to effective treatment of syncope.
Abstract:
The rich cardiology literature of the past 100 years in which the most important forms of syncope are described - including vasodepressor syncope, postural orthostatic hypotension, and Morgagni-Stokes-Adams syncope - is fascinating. These conditions were of interest to some of our most astute clinicians who were also excellent writers. We thus have available for review the remarkable description of patients with these entities written by clinicians such as Soma Weiss, Sir Thomas Lewis, Laurence Ellis, David Sherf, Milton Shy, and Glenn Drager. In their detailed clinical descriptions we identify the pertinent symptoms and signs we see in our patients today years later. A group of brilliant basic physiologists and cardiologists was able to explain the altered physiology responsible for the clinical presentations of syncope patients. Basic investigations were done by investigators such as Arnold Weissler, James Warren, J. Erlanger and clinical cardiologists including John Parkinson, Cornelio Papp, and William Evans to name just a few. Between the early precise clinical descriptions and the subsequent thorough definition of the altered physiology, a surprisingly complete understanding of these clinical entities was established 50 years ago. It took another generation before clinicians developed methods of caring for patients with these clinical entities. The development of implantable devices, e.g., pacemakers and defibrillators, for use in Morgagni-Adams-Stokes attacks is the best example of curative therapies catching up with clinical diagnoses. Other more simple relevant therapies were developed for patients with vasodepressor syncope and postural orthostatic hypotension. Finally, the development and acceptance of clinical guidelines for the treatment of these conditions brought the original clinical observations and description of altered physiology into focus and ushered in a new generation of improved care for these patients.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 10:25
Multi-system Monitoring for Identification of Seizures, Arrhythmias and Apnea in Conscious Restrained Rabbits
Published on: March 27, 2021
Related Concept Videos
 01:25
Cardiomyopathy I: Introduction and Classification
 01:15
Dysrhythmias I: Introduction
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Pathophysiology of Cardiac Performance
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:30
Introduction Cardiac Emergencies