Related Experiment Video
Updated: May 13, 2026
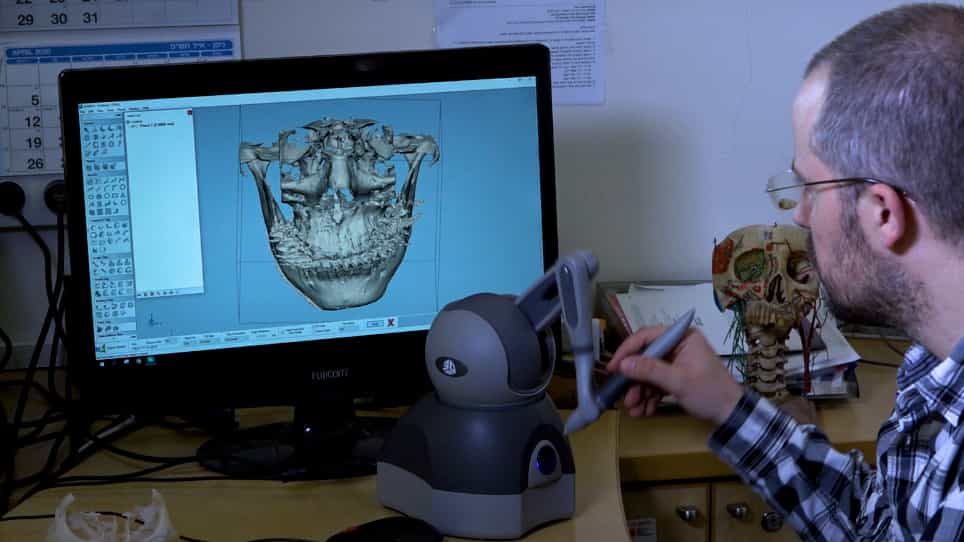

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Treatment of maxillary cleft palate: Distraction osteogenesis vs. orthognathic surgery
Adi Rachmiel1, Michal Even-Almos, Dror Aizenbud
1Department of Oral and Maxillofacial Surgery, Rambam Medical Center, Haifa, Israel.

Purpose:
The purpose of this paper is to compare the treatment of hypoplastic, retruded maxillary cleft palate using distraction osteogenesis vs. orthognathic surgery in terms of stability and relapse, growth after distraction and soft tissue profile changes.
Materials And Methods:
The cleft patients showed anteroposterior maxillary hypoplasia with class III malocclusion and negative overjet resulting in a concave profile according to preoperative cephalometric measurements, dental relationship, and soft tissue analysis. The patients were divided in two groups of treatment : S0 eventeen were treated by orthognathic Le Fort I osteotomy fixed with four mini plates and 2 mm screws, and 19 were treated by maxillary distraction osteogenesis with rigid extraoral devices (RED) connected after a Le Fort I osteotomy. The rate of distraction was 1 mm per day to achieve Class I occlusion with slight overcorrection and to create facial profile convexity. Following a 10 week latency period the distraction devices were removed.
Results:
In the RED group the maxilla was advanced an average of 15.80 mm. The occlusion changed from class III to class I. The profile of the face changed from concave to convex. At a 1-year follow up the results were stable. The mean orthognathic movement was 8.4 mm.
Conclusion:
In mild maxillary deficiency a one stage orthognathic surgery is preferable. However, in patients requiring moderate to large advancements with significant structural deficiencies of the maxilla or in growing patients the distraction technique is preferred.
