Related Experiment Video
Updated: May 13, 2026


Targeting Alpha Synuclein Aggregates in Cutaneous Peripheral Nerve Fibers by Free-floating Immunofluorescence Assay
Published on: June 25, 2019
Diagnosis of familial amyloid polyneuropathy: wide-ranged clinicopathological features
1Nagoya University Graduate School of Medicine, Department of Neurology, Nagoya 466-8550, Japan +81 52 744 2385 ; +81 52 744 2384 ; sobueg@med.nagoya-u.ac.jp.

Importance Of The Field:
Owing to the recent development of biochemical and molecular analyses, familial amyloid polyneuropathy (FAP) is not considered to be as rare as was previously thought. Transthyretin (TTR) Val30Met-associated FAP (FAP ATTR Val30Met) is the most common form of FAP. Although patients with FAP ATTR Val30Met had been considered to be concentrated in geographically restricted areas of Japan, Portugal and Sweden, a late-onset form of this type of FAP was discovered in non-endemic areas and revealed to be widely distributed throughout the world. Therefore, there is an increasing necessity to characterize the variability in the clinical, electrophysiological and histopathological features of this disease.
Areas Covered In This Review:
Recent progress in the diagnostic techniques for FAP is described, focusing especially on those for FAP ATTR Val30Met. Clinical, electrophysiological and histopathological features in early-onset FAP ATTR Val30Met cases from endemic foci and those in late-onset cases from non-endemic areas in Japan are comparatively described.
What The Reader Will Gain:
Patients with FAP ATTR Val30Met from endemic foci and those from non-endemic areas show different clinical, electrophysiological and histopathological features. As compared with the classic FAP phenotype, the clinicopathological features of patients from the non-endemic areas tend to be nonspecific.
Take Home Message:
Awareness of the possibility of sporadic late-onset FAP ATTR Val30Met is needed at the time of the initial clinical and electrophysiological evaluation of neuropathy with an undetermined etiology to avoid a missed diagnosis.
Insights
Familial amyloid polyneuropathy (FAP) associated with transthyretin (TTR) Val30Met is more widespread than previously thought. Late-onset FAP ATTR Val30Met presents differently in non-endemic areas, requiring increased diagnostic awareness.
Area of Science:
- Neurology
- Genetics
- Pathology
Background:
- Familial amyloid polyneuropathy (FAP) is increasingly recognized due to advances in molecular diagnostics.
- Transthyretin (TTR) Val30Met-associated FAP (FAP ATTR Val30Met) is the most prevalent subtype.
- Previously thought to be geographically restricted, FAP ATTR Val30Met has a global distribution, including late-onset forms in non-endemic regions.
Purpose of the Study:
- To characterize the clinical, electrophysiological, and histopathological variability of FAP ATTR Val30Met.
- To compare early-onset FAP ATTR Val30Met from endemic foci with late-onset cases from non-endemic areas in Japan.
Main Methods:
- Review of diagnostic techniques for FAP, with a focus on FAP ATTR Val30Met.
- Comparative analysis of clinical, electrophysiological, and histopathological features between endemic and non-endemic FAP ATTR Val30Met cases.
Main Results:
- Significant differences exist in clinical, electrophysiological, and histopathological features between FAP ATTR Val30Met patients from endemic and non-endemic areas.
- Patients from non-endemic areas often exhibit nonspecific clinicopathological features compared to the classic FAP phenotype.
Conclusions:
- Increased awareness of sporadic late-onset FAP ATTR Val30Met is crucial for accurate diagnosis.
- Early clinical and electrophysiological evaluation is vital for identifying neuropathy of undetermined etiology, preventing missed diagnoses of FAP ATTR Val30Met.

Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:23
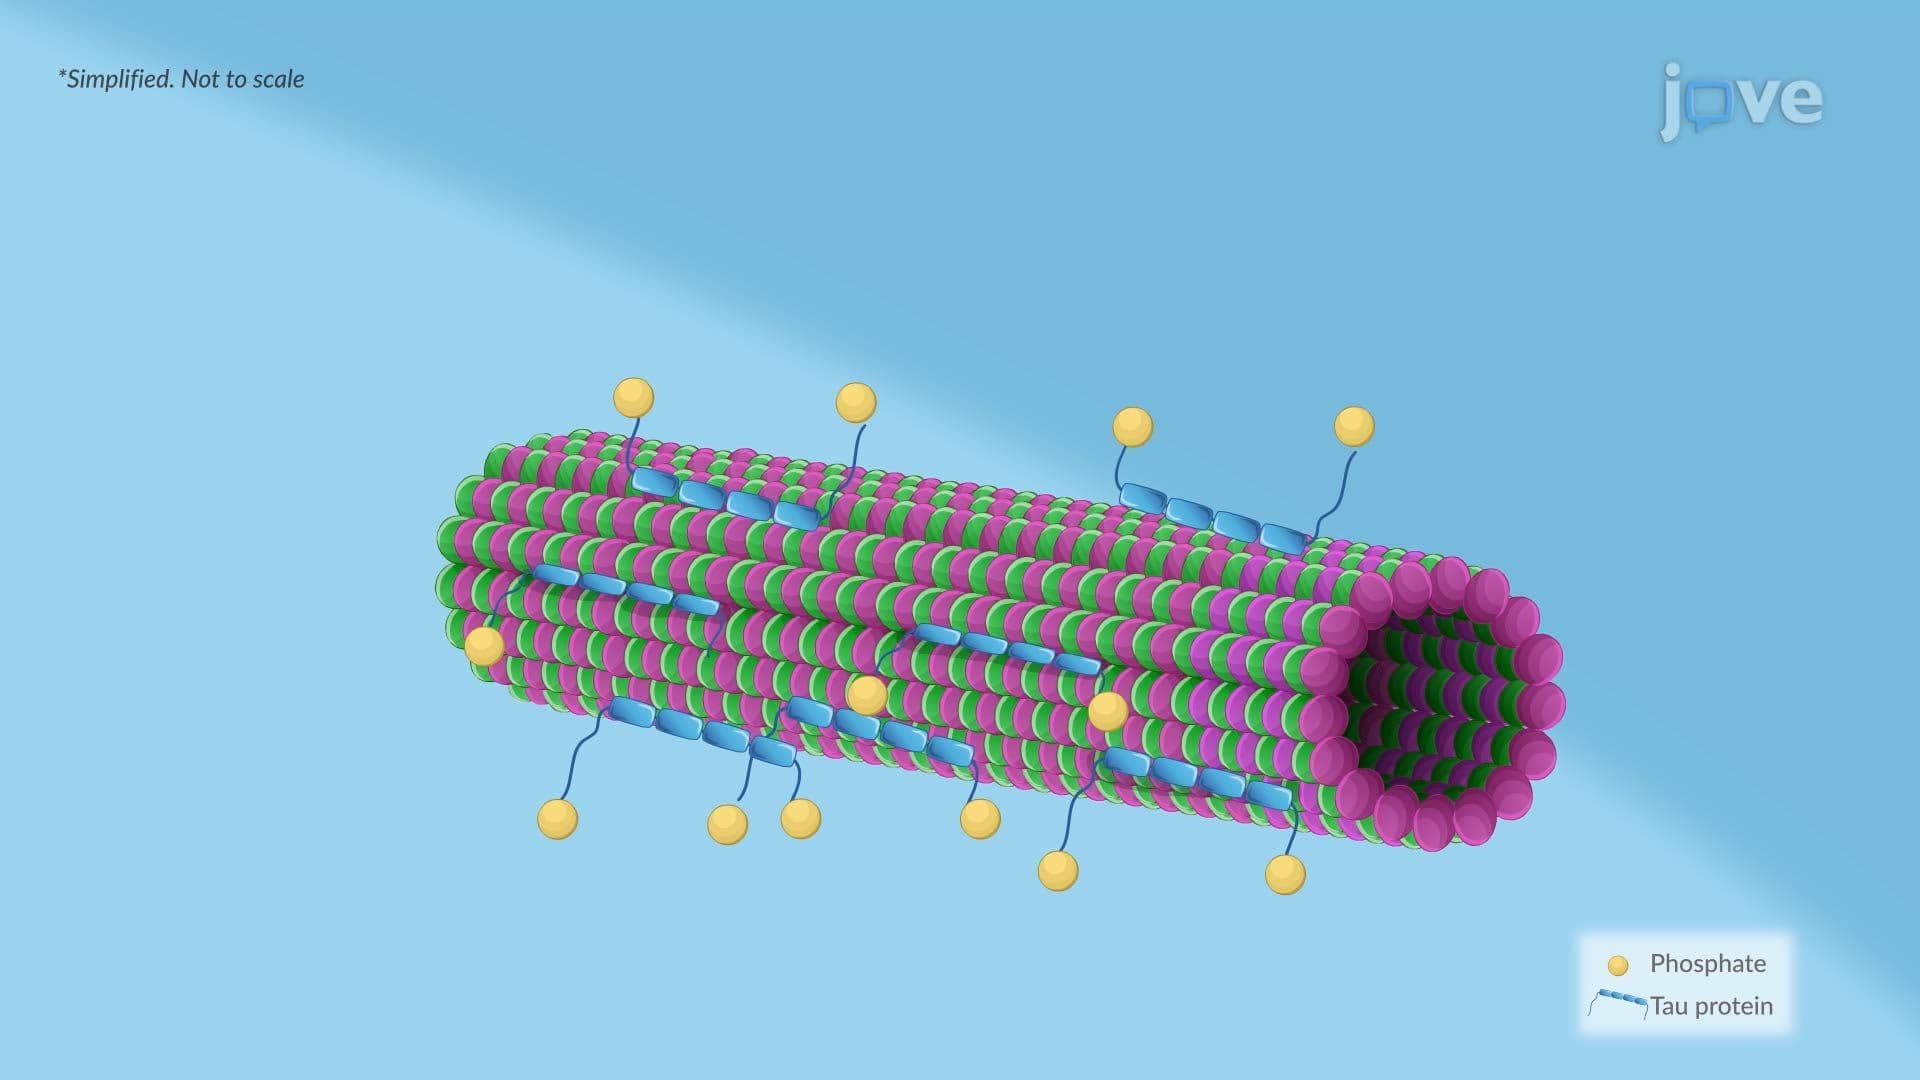
Alzheimer Disease ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:24
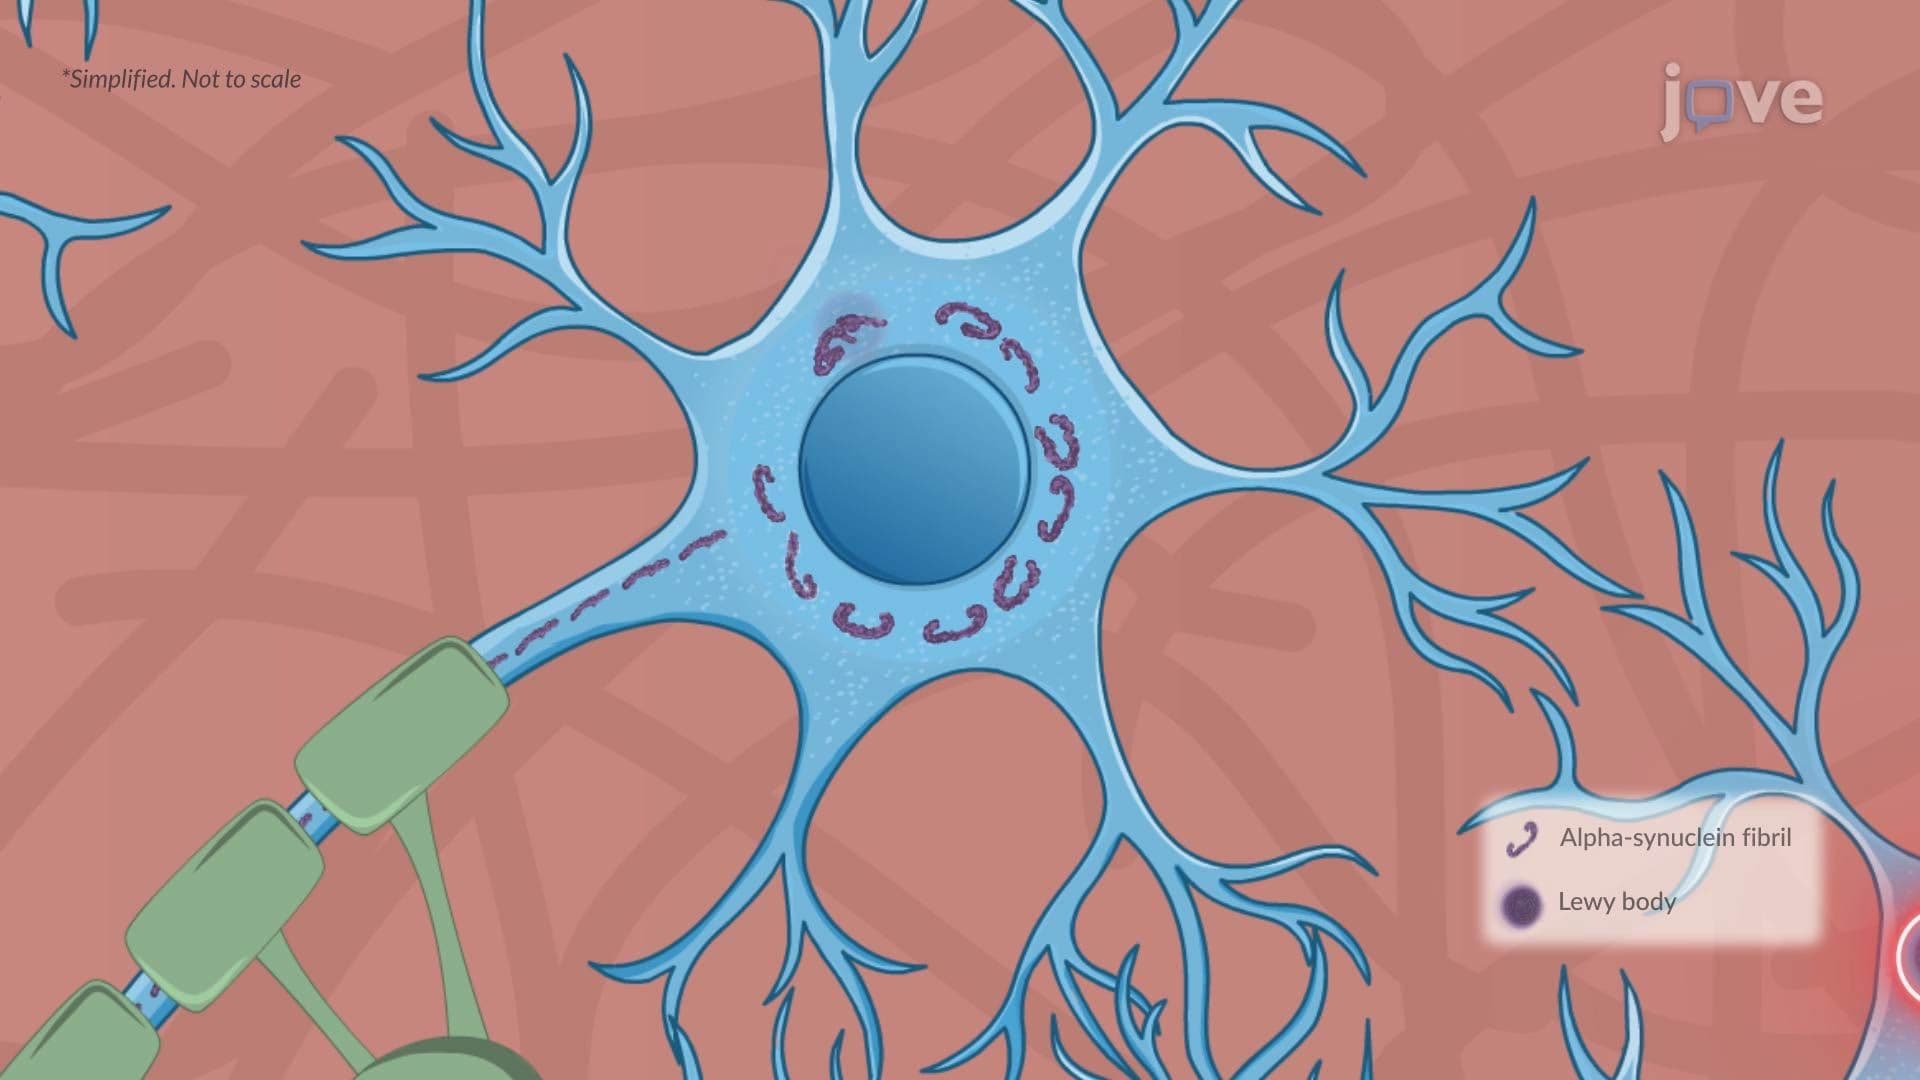
Parkinson Disease ll: Pathophysiology
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...