Related Experiment Video
Updated: May 13, 2026
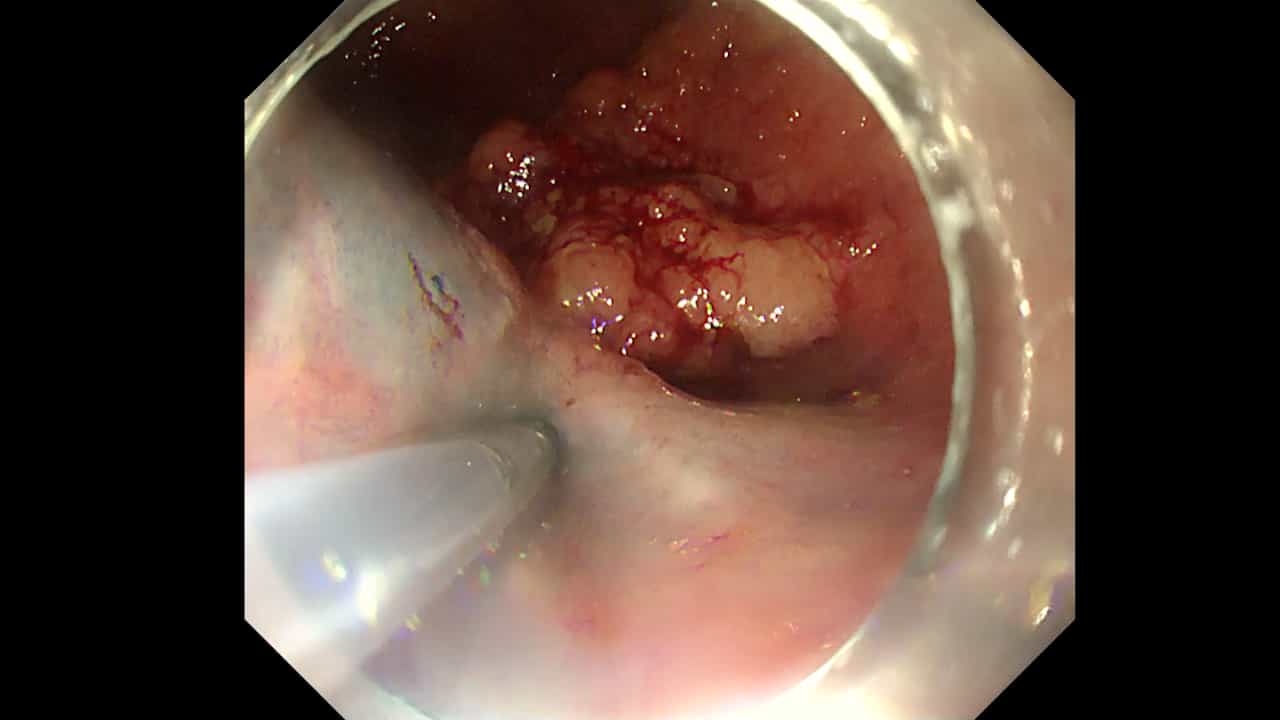
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Current status of endoscopic resection strategy for large, early colorectal neoplasia in Japan
Takeshi Nakajima1, Yutaka Saito, Shinji Tanaka
1Endoscopy Division, National Cancer Center Hospital, 5-1-1 Tsukiji, Chuo-ku, Tokyo 104-0045, Japan. tnakajim@ncc.go.jp

Background:
Conventional endoscopic resection (CER) for early colorectal neoplasia (CRN) is widely accepted as a minimally invasive treatment. Endoscopic submucosal dissection (ESD) was developed in Japan to resect larger lesions, but ESD was not covered by the Japanese national health insurance until April 2012. In addition, treatment strategies vary considerably among medical facilities. To evaluate the current situation in Japan regarding endoscopic treatment of CRNs measuring ≥20 mm, we conducted a prospective multicenter study at 18 medium-volume and high-volume specialized facilities in cooperation with the Japan Society for Cancer of the Colon and Rectum (JSCCR).
Methods:
The JSCCR conducted a multicenter, observational study of all patients treated by CER and ESD of CRNs measuring ≥20 mm.
Results:
From October 2007 to December 2010, CERs and ESDs were performed on 1,845 CRNs (CERs 1,029; ESDs 816). Lesions diagnosed as protruded, flat, and depressed totaled 541, 1224, and 48, respectively. En bloc resection rates and mean procedure times for CER/ESD were 56.9%/94.5% (P < 0.01) and 18 ± 23 min/96 ± 69 min, respectively. The average ESD procedure time was 129 ± 83 min in the ≥40-mm group. As lesion size increased, the CER en bloc resection rate decreased significantly (trend P < 0.01), but the ESD en bloc resection rate remained over 93%. Perforation and delayed bleeding rates of CER/ESD were 0.8%/1.6% (P < 0.05) and 2%/2.2% (P = 0.3), respectively.
Conclusions:
The en bloc resection rate for ESD was significantly higher than for CER, although complication rates were fairly low. Despite a longer procedure time, safety of colorectal ESD has improved in various facilities in Japan. However, ESD for lesions measuring ≥40 mm must be performed by experienced endoscopists due to the longer procedure time.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 10:31
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016