Related Experiment Video
Updated: May 12, 2026
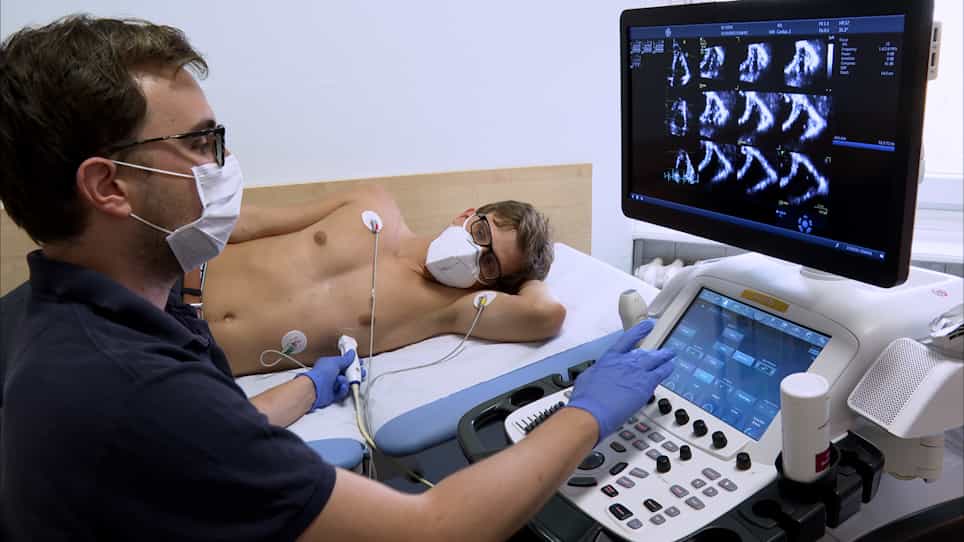

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Symptomatic exercise-induced left ventricular outflow tract obstruction without left ventricular hypertrophy
Eyad K Alhaj1, Bette Kim, Deborah Cantales
1Division of Cardiology, Department of Medicine, St. Luke's-Roosevelt Hospital Center, Columbia University College of Physicians and Surgeons, New York, NY, USA.

Background:
Left ventricular (LV) outflow tract obstruction (LVOTO) is most commonly seen in patients with hypertrophic cardiomyopathy. Postexercise dynamic LVOTO (DLVOTO) has been infrequently identified in symptomatic patients without LV hypertrophy, and its pathophysiology is not well established. The aim of this study was to identify echocardiographic abnormalities that might explain the dynamic development of systolic anterior motion, mitral-septal contact, and LVOTO in these patients.
Methods:
Patients with DLVOTO and normal wall thickness were compared with 20 age-matched and gender-matched controls with normal stress echocardiographic findings. Two other groups were also compared: patients with DLVOTO and mild segmental hypertrophy (segmental wall thickness ≤15 mm) and patients with normal left ventricles but DLVOTO after dobutamine stress.
Results:
Six symptomatic patients were identified (mean age, 48 ± 9 years; range, 37-60 years; five men) with normal wall thickness who developed DLVOTO after exercise during a 6-year period. Five had been hospitalized for cardiac symptoms. The mean postexercise LV outflow tract gradient caused by systolic anterior motion mitral-septal contact was 107 ± 55 mm Hg (range, 64-200 mm Hg). All patients had echocardiographic LV wall thicknesses in the normal range (≤12 mm). Structural abnormalities of the mitral valve were identified in all six patients. These were elongated posterior leaflets (2.0 vs 1.5 cm, P < .0005), elongated anterior leaflets (3.2 vs 2.6 cm, P = .015), increased protrusion height of the mitral valve beyond the mitral annular plane (2.6 vs 0.6 cm, P < .00001), and residual protruding portions of the mitral valve leaflets (0.85 vs 0.24 cm, P < .005). There was anterior positioning of the papillary muscles in the LV cavity, with a greater distance from the plane of the papillary muscles to the posterior wall (1.8 vs 1.3 cm, P = .03). In two patients, potentially provoking medications were stopped; two patients received β-blockers, with reductions of angina. Medium-term prognosis was good; no patient had died after 3.5 years. The mitral valve abnormalities in the 10 patients with DLVOTO and mild segmental hypertrophy were qualitatively and quantitatively very similar to those in patients with DLVOTO without hypertrophy. In contrast, the valves of patients with dobutamine stress DLVOTO were not elongated, but 50% had residual mitral leaflets that protruded past the coaptation point by ≥5 mm.
Conclusions:
DLVOTO after exercise can occur in the absence of LV hypertrophy and may be associated with high gradients and cardiac symptoms. Elongated, redundant mitral valve leaflets with anterior position of the papillary muscles appear to cause the postexercise obstruction.
More Related Videos


Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Heart Failure III: Clinical Manifestations