Related Experiment Video
Updated: May 12, 2026


Assessment of Myofilament Ca2+ Sensitivity Underlying Cardiac Excitation-contraction Coupling
Published on: August 1, 2016
Familial dilated cardiomyopathy mutations uncouple troponin I phosphorylation from changes in myofibrillar Ca²⁺
Massimiliano Memo1, Man-Ching Leung, Douglas G Ward
1Myocardial Function, NHLI, Imperial College London, London, W12 0NN, UK.

Aims:
The pure form of familial dilated cardiomyopathy (DCM) is mainly caused by mutations in genes encoding sarcomeric proteins. Previous measurements using recombinant proteins suggested that DCM mutations in thin filament proteins decreased myofibrillar Ca(2+) sensitivity, but exceptions were reported. We re-investigated the molecular mechanism of familial DCM using native proteins.
Methods And Results:
We used the quantitative in vitro motility assay and native troponin and tropomyosin to study DCM mutations in troponin I, troponin T, and α-tropomyosin. Four mutations reduced myofilament Ca(2+) sensitivity, but one mutation (TPM1 E54K) did not alter Ca(2+) sensitivity and another (TPM1 D230N) increased Ca(2+) sensitivity. In thin filaments from normal human and mouse heart, protein kinase A (PKA) phosphorylation of troponin I caused a two- to three-fold decrease in myofibrillar Ca(2+) sensitivity. However, Ca(2+) sensitivity did not change with the level of troponin I phosphorylation in any of the DCM-mutant containing thin filaments (E40K, E54K, and D230N in α-tropomyosin; R141W and ΔK210 in cardiac troponin T; K36Q in cardiac troponin I; G159D in cardiac troponin C, and E361G in cardiac α-actin). This 'uncoupling' was observed with native mutant protein from human and mouse heart and with recombinant mutant protein expressed in baculovirus/Sf9 systems. Uncoupling was independent of the fraction of mutated protein present above 0.55.
Conclusion:
We conclude that DCM-causing mutations in thin filament proteins abolish the relationship between myofilament Ca(2+) sensitivity and troponin I phosphorylation by PKA. We propose that this blunts the response to β-adrenergic stimulation and could be the cause of DCM in the long term.
Insights
Familial dilated cardiomyopathy (DCM) mutations in thin filament proteins disrupt the normal response to protein kinase A (PKA) phosphorylation. This uncoupling may impair the heart's ability to respond to stress, contributing to DCM development.
Area of Science:
- Cardiology
- Molecular Biology
- Biochemistry
Background:
- Familial dilated cardiomyopathy (DCM) is often caused by mutations in sarcomeric protein genes.
- Previous studies suggested DCM mutations decrease myofibrillar Ca(2+) sensitivity, but findings were inconsistent.
Purpose of the Study:
- To re-investigate the molecular mechanisms of familial DCM using native proteins.
- To clarify the impact of DCM mutations in thin filament proteins on myofilament Ca(2+) sensitivity and its regulation.
Main Methods:
- Quantitative in vitro motility assay using native troponin and tropomyosin.
- Analysis of DCM mutations in troponin I, troponin T, and α-tropomyosin.
- Assessment of protein kinase A (PKA) phosphorylation effects on myofilament Ca(2+) sensitivity.
Main Results:
- Four DCM mutations reduced myofilament Ca(2+) sensitivity; one (TPM1 E54K) had no effect, and another (TPM1 D230N) increased it.
- PKA phosphorylation of troponin I decreased Ca(2+) sensitivity in normal filaments but had no effect in DCM-mutant filaments ('uncoupling').
- This uncoupling was observed with native and recombinant mutant proteins and was independent of mutation fraction above 0.55.
Conclusions:
- DCM-causing mutations in thin filament proteins abolish the link between myofilament Ca(2+) sensitivity and PKA phosphorylation.
- This disruption likely blunts the heart's response to β-adrenergic stimulation, potentially causing long-term DCM.


Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:16
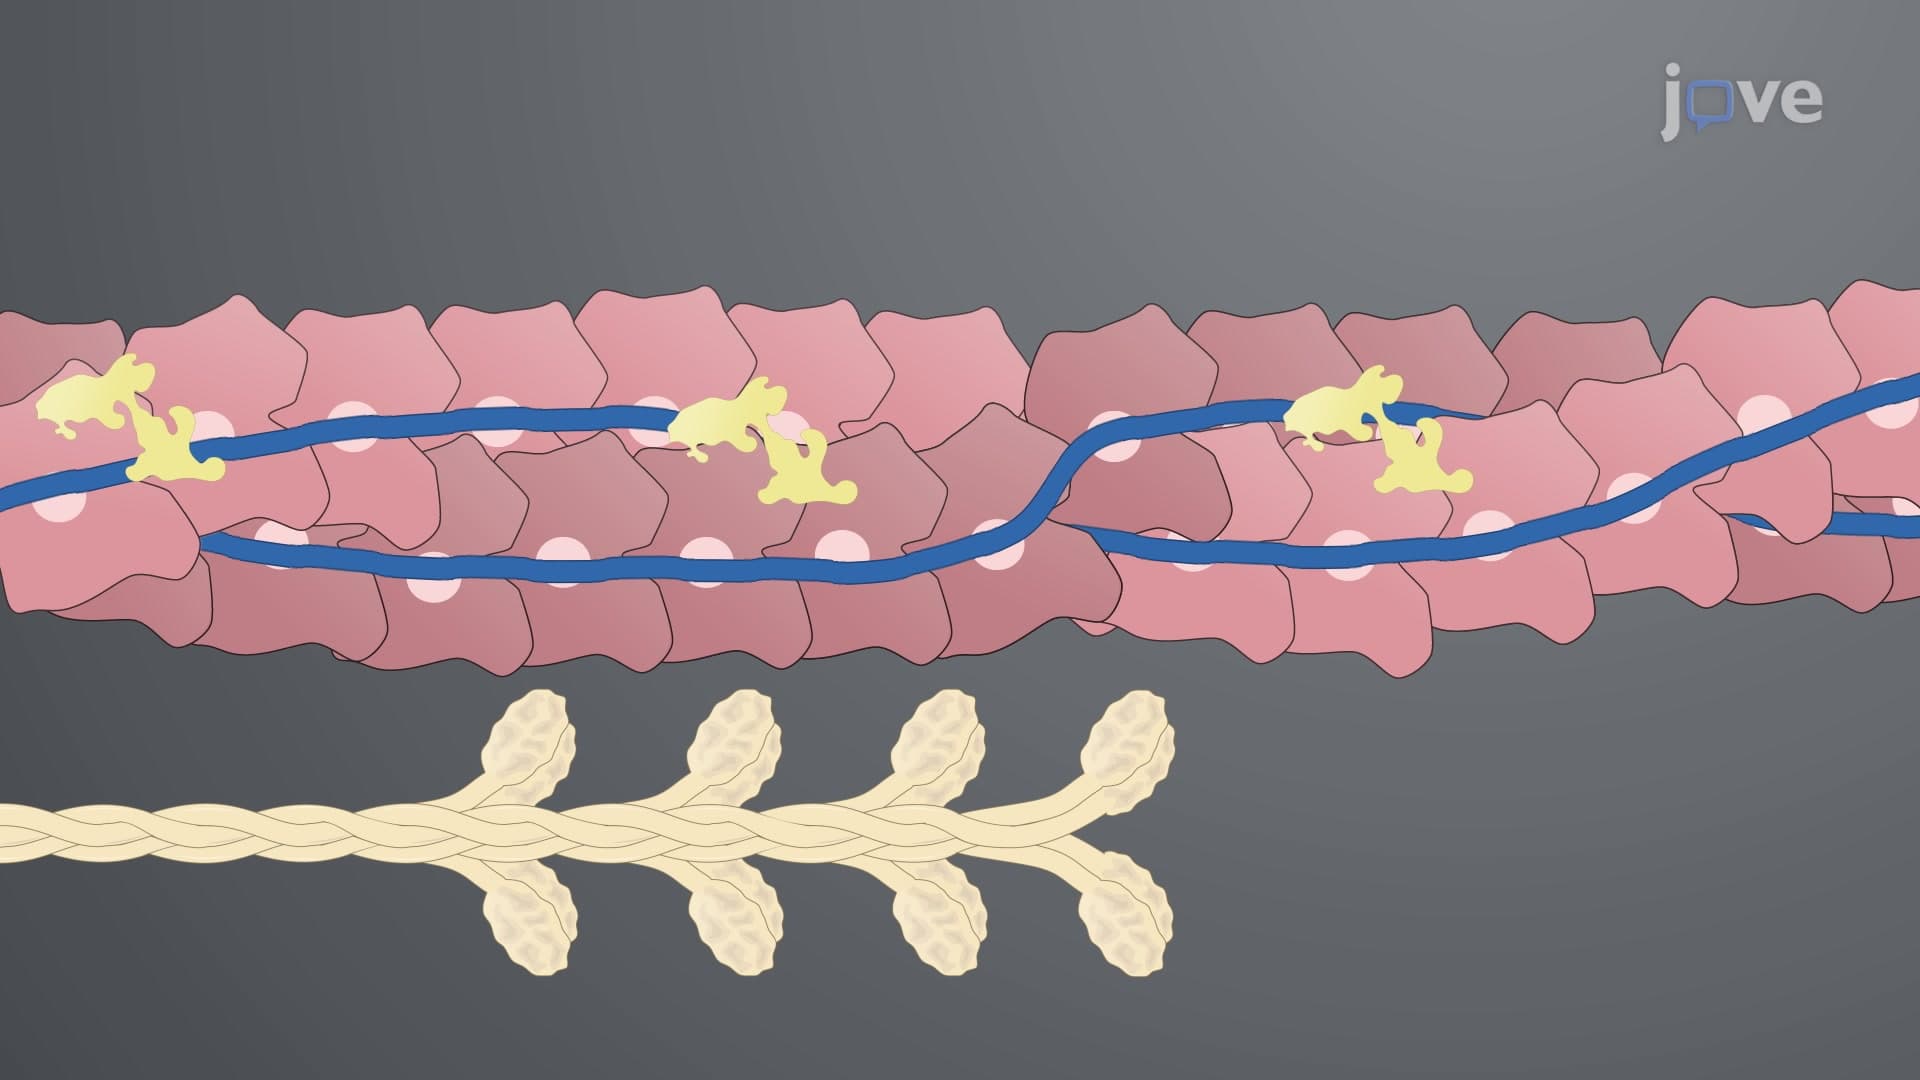
Actin and Myosin in Muscle Contraction
 01:16
Calmodulin-dependent Signaling
The Ca2+-CaM complex does not have enzymatic activity by itself. Instead, the complex binds downstream target proteins, including membrane proteins or enzymes,...
 01:26
Cross-bridge Cycle