Related Experiment Video
Updated: May 12, 2026
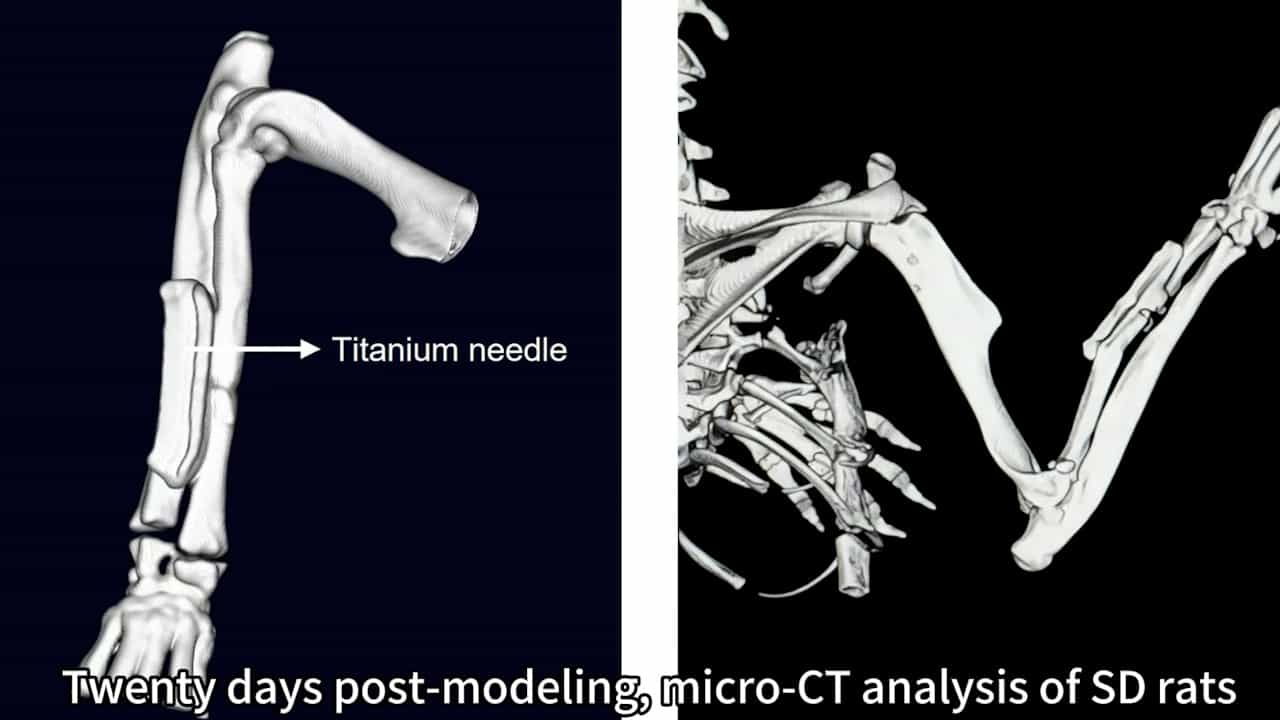

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
WITHDRAWN: Interventions for treating wrist fractures in children
Alwyn Abraham1, Helen H G Handoll, Tahir Khan
1Department of PaediatricOrthopaedics, LeicesterRoyal Infirmary, Leicester, UK. alwyn.abraham@uhl-tr.nhs.uk.

Insights
Removable splints are effective for pediatric buckle wrist fractures, and below-elbow casts are preferable to above-elbow casts. Percutaneous wiring reduces redisplacement but functional outcomes require further study.
Area of Science:
- Orthopedic surgery
- Pediatric trauma
- Evidence-based medicine
Background:
- Wrist fractures are common in children, accounting for approximately one-third of all pediatric fractures.
- Falls onto an outstretched hand are the most frequent cause of pediatric wrist fractures.
Purpose of the Study:
- To evaluate removable splinting versus plaster casts for buckle fractures.
- To assess cast length and position for pediatric wrist fractures.
- To determine the role of surgical fixation for displaced wrist fractures in children.
Main Methods:
- Systematic review of randomized and quasi-randomized controlled trials.
- Searched multiple databases including Cochrane, MEDLINE, EMBASE, and CINAHL up to October 2007.
- Included 10 trials involving 827 children, assessing variable quality.
Main Results:
- Removable splints showed no short-term deformity and were preferred by children and parents for buckle fractures.
- Below-elbow casts were less restrictive and did not increase redisplacement compared to above-elbow casts.
- Percutaneous wiring reduced redisplacement but functional outcomes at three months were not significantly improved.
Conclusions:
- Limited evidence supports removable splintage for buckle fractures, challenging traditional above-elbow cast use.
- Percutaneous wire fixation is effective for preventing redisplacement but long-term functional outcomes need further investigation.
- Further research is needed on optimal splinting for buckle fractures and indications for surgery in displaced wrist fractures.
Background:
Approximately a third of all fractures in children occur at the wrist, usually from falling onto an outstretched hand.
Objectives:
We aimed to evaluate removable splintage versus plaster casts (requiring removal by a specialist) for undisplaced compression (buckle) fractures; cast length and position; and the role of surgical fixation for displaced wrist fractures in children.
Search Methods:
We searched the Cochrane Bone, Joint and Muscle Trauma Group Specialised Register (October 2007), the Cochrane Central Register of Controlled Trials (The Cochrane Library 2007, Issue 4), MEDLINE (from 1966), EMBASE (from 1988), CINAHL (from 1982) and reference lists of articles. Date of last search October 2007.
Selection Criteria:
Any randomised or quasi-randomised controlled trials comparing types and position of casts and the use of surgical fixation for distal radius fractures in children.
Data Collection And Analysis:
Two authors performed trial selection. All three authors independently assessed methodological quality and extracted data.
Main Results:
The 10 included trials, involving 827 children, were of variable quality.Four trials compared removable splintage versus the traditional below-elbow cast in children with buckle fractures. There was no short-term deformity recorded in all four trials and, in one trial, no refracture at six months. The Futura splint was cheaper to use; a removable plaster splint was less restrictive to wear enabling more children to bathe and participate in other activities, and the option preferred by children and parents; the soft bandage was more comfortable, convenient and less painful to wear; home-removable plaster casts removed by parents did not result in significant differences in outcome but were strongly favoured by parents.Two trials found below-elbow versus above-elbow casts did not increase redisplacement of reduced fractures or cast-related complications, were less restrictive during use and avoided elbow stiffness.One trial evaluating the effect of arm position in above-elbow casts found no effect on deformity.Three trials found that percutaneous wiring significantly reduced redisplacement and remanipulation but one of these found no advantage in function at three months.
Authors' Conclusions:
Limited evidence supports the use of removable splintage for buckle fractures and challenges the traditional use of above-elbow casts after reduction of displaced fractures. Although percutaneous wire fixation prevents redisplacement, the effects on longer term outcomes including function are not established.Further research is warranted on the optimum approach, including splintage, for buckle fractures; and on the use of below-elbow casts and indications for surgery for displaced wrist fractures in children.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Venous Thrombosis III: Interprofessional Care