Related Experiment Video
Updated: May 12, 2026
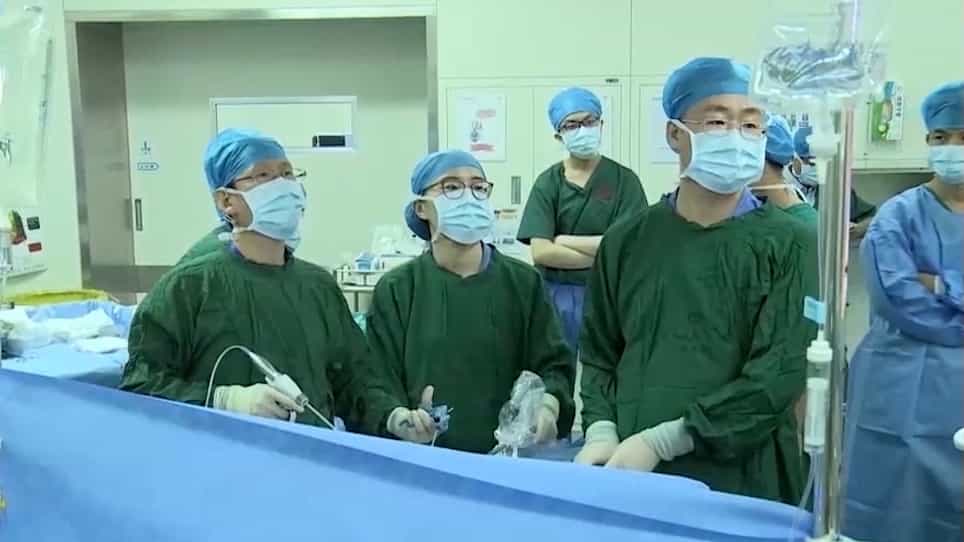
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Concomitant jejunal sarcomatoid carcinoma and gastric GIST in patient with polymyalgia rheumatica: A case report
Francesco Pata1, Manonmani Sengodan, Cheuk-Bong Tang
1Department of General Surgery, Upper Gastrointestinal Unit, Broomfield Hospital, Court Road, Chelmsford CM1 7ET, United Kingdom.

Introduction:
Sarcomatoid carcinoma (SCA) of the small bowel is an extremely rare tumor with only 21 cases reported in literature and GISTs are relatively rare gastrointestinal neoplasms.
Presentation Of Case:
We report a case of an 85 year-old female admitted with intestinal obstruction in June 2010. She suffered from polymyalgia rheumatica and was under surveillance for a presumed gastric GIST. A laparotomy was performed with resection of the jejunal obstruction and complete excision of the gastric mass. Histology confirmed a gastric GIST and sarcomatoid carcinoma of the small bowel. The patient was discharged 21 days after the operation and died on the 88th post-operative day.
Discussion:
Synchronous GISTs and other malignancies have been reported over the last years with increasing frequency. Sarcomatoid carcinoma of the small bowel is an aggressive neoplasm with poor survival rates and surgery is the cornerstones of treatment. Given its unpredictable clinical behaviour and concomitant association with other malignancies, GISTs require adequate surgical resection with careful, long-term follow-up.
Conclusion:
This is the first case of concomitant gastric GIST with Sarcomatoid carcinoma of the small bowel, and the first report of sarcomatoid small bowel carcinoma in association with polymyalgia rheumatica.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:26
Gastritis II: Pathophysiology
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...