Pulmonary vascular impedance in microembolic pulmonary hypertension: effects of synchronous high-frequency jet ventilation
Related Experiment Video
Updated: Oct 17, 2026
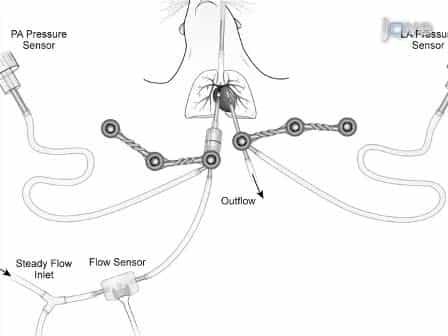
Characterization of the Isolated, Ventilated, and Instrumented Mouse Lung Perfused with Pulsatile Flow
Published on: April 29, 2011
R Naeije1, J M Maarek, H K Chang
1Department of Biomedical Engineering, University of Southern California, Los Angeles.

Abstract:
Increased intrathoracic pressure (ITP) during conventional mechanical ventilation may interfere with the adaptation of right ventricular function to pulmonary hypertension. We studied the effects of synchronous cardiac cycle-specific high frequency jet ventilation (HFJV) in 10 anesthetized dogs before and after embolization of the pulmonary artery with 150-200 microns glass beads. The delivery of the jet was synchronized with early systole, late systole, early diastole and late diastole of the cardiac cycle. Right and left ventricular pressures (Prv and Plv) and pulmonary arterial pressures (Ppa) were measured by transducer-tipped catheters and pulmonary blood flow by an ultrasonic flow probe. Right ventricular end-systolic and end-diastolic volumes (rvESV and rvEDV) were estimated from the thermodilution curve obtained with a Swan-Ganz catheter equipped with a fast response thermistor. Pulmonary hypertension caused significant increases in heart rate (89 +/- 7 to 152 +/- 8 beats/min), rvEDV (80 +/- 7 to 131 +/- 23 ml), diastolic transmural Prv (2 +/- 1 to 5 +/- 1 mm Hg), and rv peak dP/dt (652 +/- 151 to 1035 +/- 160 mm Hg/s). The spectrum of pulmonary vascular input impedance was displaced towards higher frequencies, input resistance was increased and characteristic impedance decreased. The latter change contributed to a relative decrease in the pulsatile component of right ventricular power output. Cardiac output remained unchanged (2.1 +/- 0.2 to 1.9 +/- 0.1 L/min, P NS). Non of these measurements was affected by the timing of the increase in ITP to specific instants in the cardiac cycle compared to apneic periods at any level of pulmonary hypertension. We conclude that in acute microembolic pulmonary hypertension 1 degree a decrease in characteristic impedance contributes to the adaptation of right ventricular function to increased afterload and 2 degrees synchronous cardiac cycle-specific HFJV has no detectable hemodynamic effect.
Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:18
Pulmonary Edema II: Pathophysiology
 01:19
Pulmonary Embolism I: Introduction