Related Experiment Video
Updated: May 12, 2026
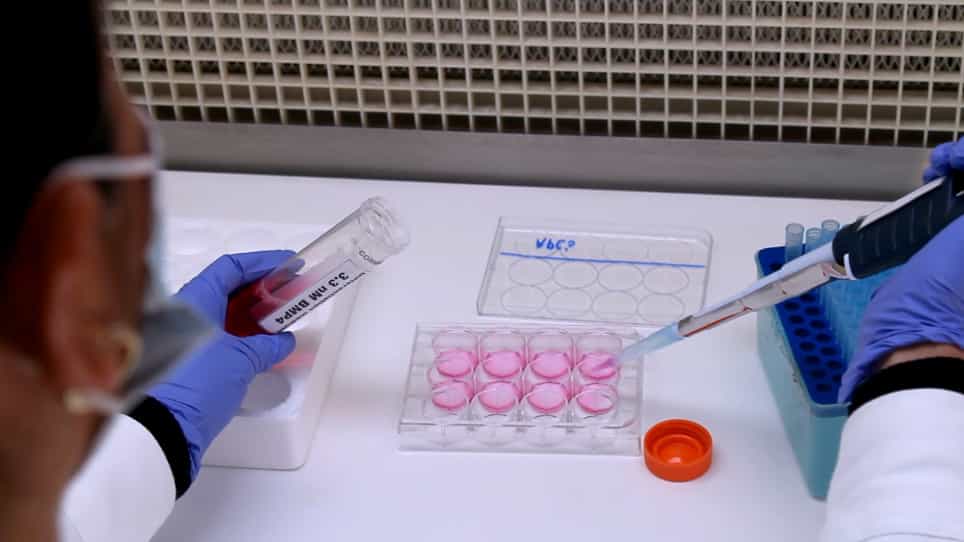

Differentiated Mouse Adipocytes in Primary Culture: A Model of Insulin Resistance
Published on: February 17, 2023
Insulin resistance and beta-cell function in different ethnic groups in Kenya: the role of abdominal fat distribution
D L Christensen1, D Faurholt-Jepsen, K Faerch
1Department of International Health, Immunology, and Microbiology, University of Copenhagen, Øster Farimagsgade 5, 1014, Copenhagen, Denmark, dirklc@sund.ku.dk.

Abstract:
Little is known about the pathophysiology of diabetes in Africans. Thus, we assessed whether insulin resistance and beta-cell function differed by ethnicity in Kenya and whether differences were modified by abdominal fat distribution. A cross-sectional study in 1,087 rural Luo (n = 361), Kamba (n = 378), and Maasai (n = 348) was conducted. All participants had a standard 75-g oral glucose tolerance test (OGTT). Venous blood samples were collected at 0, 30, and 120 min. Serum insulin was analysed at 0 and 30 min. From the OGTT, we assessed the homoeostasis model assessment of insulin resistance by computer model, early phase insulin secretion, and disposition index (DI) dividing insulin secretion by insulin resistance. Abdominal subcutaneous adipose tissue (SAT) and visceral adipose tissue (VAT) thickness were carried out by ultrasonography. Linear regression analyses were done to assess ethnic differences in insulin indices. The Maasai had 32 and 17% higher insulin resistance than the Luo and Kamba, respectively (p < 0.001). Early phase insulin secretion was 16% higher in the Maasai compared to the Luo (p < 0.001). DI was 12% (p = 0.002) and 10% (p = 0.015) lower in the Maasai compared to the Luo and Kamba, respectively. Adjustments of SAT (range 0.1-7.1 cm) and VAT (range 1.5-14.2 cm) largely explained these inter-group differences with the Maasai having the highest combined abdominal fat accumulation. The Maasai had the highest insulin resistance and secretion, but the lowest relative beta-cell function compared to the Luo and Kamba. These differences were primarily explained by abdominal fat distribution.

Related Concept Videos
 01:26
Type II Diabetes I: Introduction
 01:24
Type II Diabetes II: Pathophysiology
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in the...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:28
Insulin: The Receptor and Signaling Pathways