Related Experiment Video
Updated: May 12, 2026
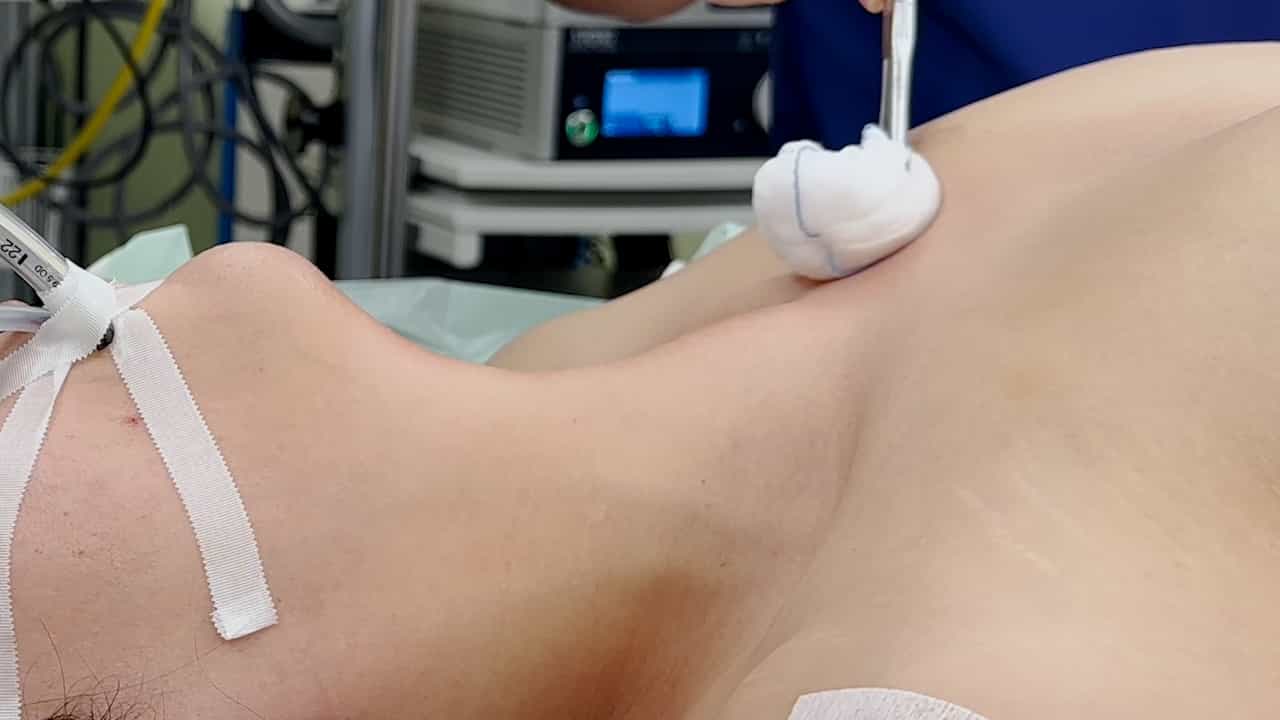

Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Two cases of fetal goiter
Ashish Saini1, Murli Manohar Reddy, Roopal Panchani
1Department of Endocrinology, Sir Ganga Ram Hospital, Old Rajinder Nagar, New Delhi, India.

Introduction:
Anterior fetal neck masses are rarely encountered. Careful routine ultrasound screening can reveal intrauterine fetal goiters (FGs). The incidence of goitrous hypothyroidism is 1 in 30,000-50,000 live births. The consequences of both FG and impaired thyroid function are serious.
Aims And Objectives:
To emphasize role of ultrasound in both invasive and non-invasive management of FG.
Materials And Methods:
Two pregnant patients, during second trimester, underwent routine antenatal ultrasound revealing FG, were investigated and managed.
Results:
Case 1: Revealed FG with fetal hypothyroidism. Intra-amniotic injection l-thyroxine given. Follow-up ultrasound confirmed the reduction of the goiter size. At birth, thyroid dyshormogenesis was suspected and neonate discharged on 50 mcg levothyroxine/day with normal growth and development so far. Case 2: Hypothyroid mother with twin pregnancy revealed FG, in twin 1, confirmed on magnetic resonance imaging (1.5 × 1.63 cm). The other twin had no thyroid swelling. Cordocentesis confirmed hypothyroidism in twin 1. Maternal thyroxine dose increased as per biochemical parameters leading to reduction in FG size. Mother delivered preterm and none of the twins had thyroid swelling. Fetal euthyroidism was confirmed on biochemical screening.
Conclusion:
FG during pregnancy should be thoroughly evaluated, diagnosed and immediately treated; although in utero options for fetal hypothyroidism management are available, emphasis should be laid on non-invasive procedures. Newer and better resolution techniques in ultrasonography are more specific and at the same time are less harmful.

Related Concept Videos
 01:27
Goiter
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:07
Teratogenicity