Related Experiment Video
Updated: May 12, 2026
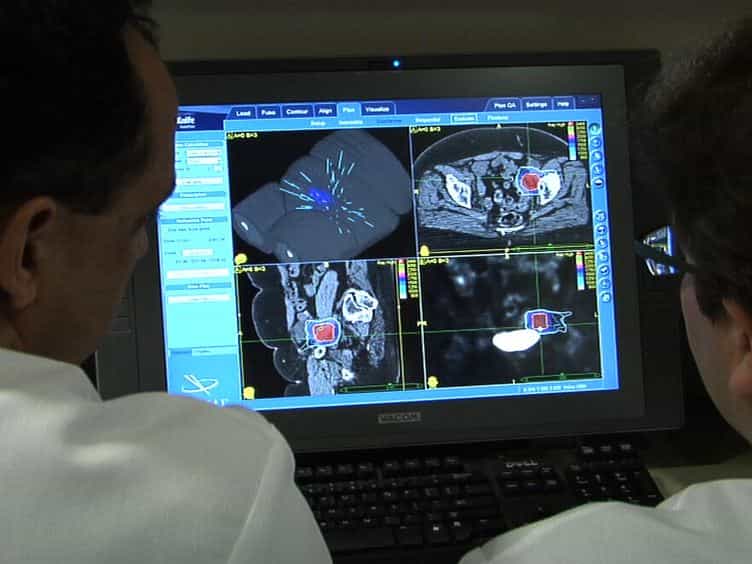
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Adaptive 3D image-guided brachytherapy: a strong argument in the debate on systematic radical hysterectomy for
Renaud Mazeron1, Jennifer Gilmore, Isabelle Dumas
1Department of Radiation Oncology, Institut de Cancérologie Gustave Roussy, Villejuif, France. renaud.mazeron@igr.fr

Purpose:
To evaluate the outcomes of patients with locally advanced cervical cancer treated with three-dimensional image-guided brachytherapy (IGABT) after concomitant chemoradiation (CCRT).
Materials And Methods:
Data from patients treated with CCRT followed by magnetic resonance imaging-guided or computed tomography-guided pulsed-dose-rate brachytherapy, performed according to the Groupe Européen de Curiethérapie-European Society for Radiotherapy and Oncology guidelines, were reviewed. At first, stage I or II patients systematically underwent radical hysterectomy or were offered a randomized study evaluating hysterectomy. Then, hysterectomy was limited to salvage treatment.
Results:
Of 163 patients identified, 27% had stage IB, 57% had stage II, 12% had stage III, and 3% had stage IVA disease. The mean dose delivered (in 2-Gy dose equivalents) to 90% of the high-risk clinical target volume was 78.1 ± 9.6 Gy, whereas the doses delivered to organs at risk were maintained under the usual thresholds. Sixty-one patients underwent a hysterectomy. Macroscopic residual disease was found in 13 cases. With a median follow-up of 36 months (range, 5-79 months), 45 patients had relapsed. The 3-year overall survival rate was 76%. Local and pelvic control rates were 92% and 86%, respectively. According to the Common Toxicity Criteria 3.0, 7.4% of patients experienced late grade 3 or 4 toxicity. Most of those had undergone postradiation radical surgery (2.9% vs. 14.8; p = .005).
Conclusion:
IGABT combined with CCRT provides excellent locoregional control rates with low treatment-related morbidity, justifying the elimination of hysterectomy in the absence of obvious residual disease. Distant metastasis remains an important first relapse and may warrant more aggressive systemic treatment.