Related Experiment Video
Updated: May 12, 2026
Rapid Point-of-Care Assay of Enoxaparin Anticoagulant Efficacy in Whole Blood
Published on: October 12, 2012
A comparative study of varying doses of enoxaparin for thromboprophylaxis in critically ill patients: a

Introduction:
Critically ill patients are predisposed to venous thromboembolism. We hypothesized that higher doses of enoxaparin would improve thromboprophylaxis without increasing the risk of bleeding. Peak anti-factor Xa (anti-Xa) levels of 0.1 to 0.4 IU/ml reflect adequate thromboprophylaxis for general ward patients. Studies conducted in orthopaedic patients demonstrated a statistically significant relationship between anti-Xa levels and wound haematoma and thrombosis. Corresponding levels for critically ill patients may well be higher, but have never been validated in large studies.
Methods:
Eighty critically ill patients weighing 50 to 90 kilograms were randomised in a double-blinded study to receive subcutaneous (sc) enoxaparin: 40 mg once daily (QD), 30 mg twice daily (BID), 40 mg BID, or 1 mg/kg QD, each administered for three days. Anti-Xa activity was measured at baseline, and daily at 4, 12, 16 and 24 hours post administration. Antithrombin, fibrinogen, and platelets were measured at baseline and twice daily thereafter.
Results:
Two patients were transferred prior to participation. On day 1, doses of 40 mg QD (n = 20) and 40 mg BID (n = 19) yielded mean peak anti-Xa of 0.20 IU/ml and 0.17 IU/ml respectively. A dose of 30 mg BID (n = 20) resulted in much lower levels (0.08 IU/ml). Patients receiving 1 mg/kg QD (n = 19) achieved near steady-state mean peak anti-Xa levels from day 1 (0.34 IU/ml). At steady state (day 3), mean peak anti-Xa levels of 0.13 IU/ml and 0.15 IU/ml were achieved with doses of 40 mg QD and 30 mg BID respectively. This increased significantly to 0.33 IU/ml and 0.40 IU/ml for doses of 40 mg BID and 1 mg/kg QD respectively. Thus anti-Xa response profiles differed significantly over the three days between enoxaparin treatment groups (P <0.0001). Doses of 40 mg BID and 1 mg/kg QD enoxaparin yielded target anti-Xa levels for over 80% of the study period. There were no adverse effects.
Conclusions:
Doses of 40 mg QD enoxaparin (Europe) or 30 mg BID (North America) yield levels of anti-Xa which may be inadequate for critically ill patients. A weight-based dose yielded the best anti-Xa levels without bioaccumulation, and allowed the establishment of near steady-state levels from the first day of enoxaparin administration.
Trial Registration:
Current Controlled Trials ISRCTN91570009.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:15
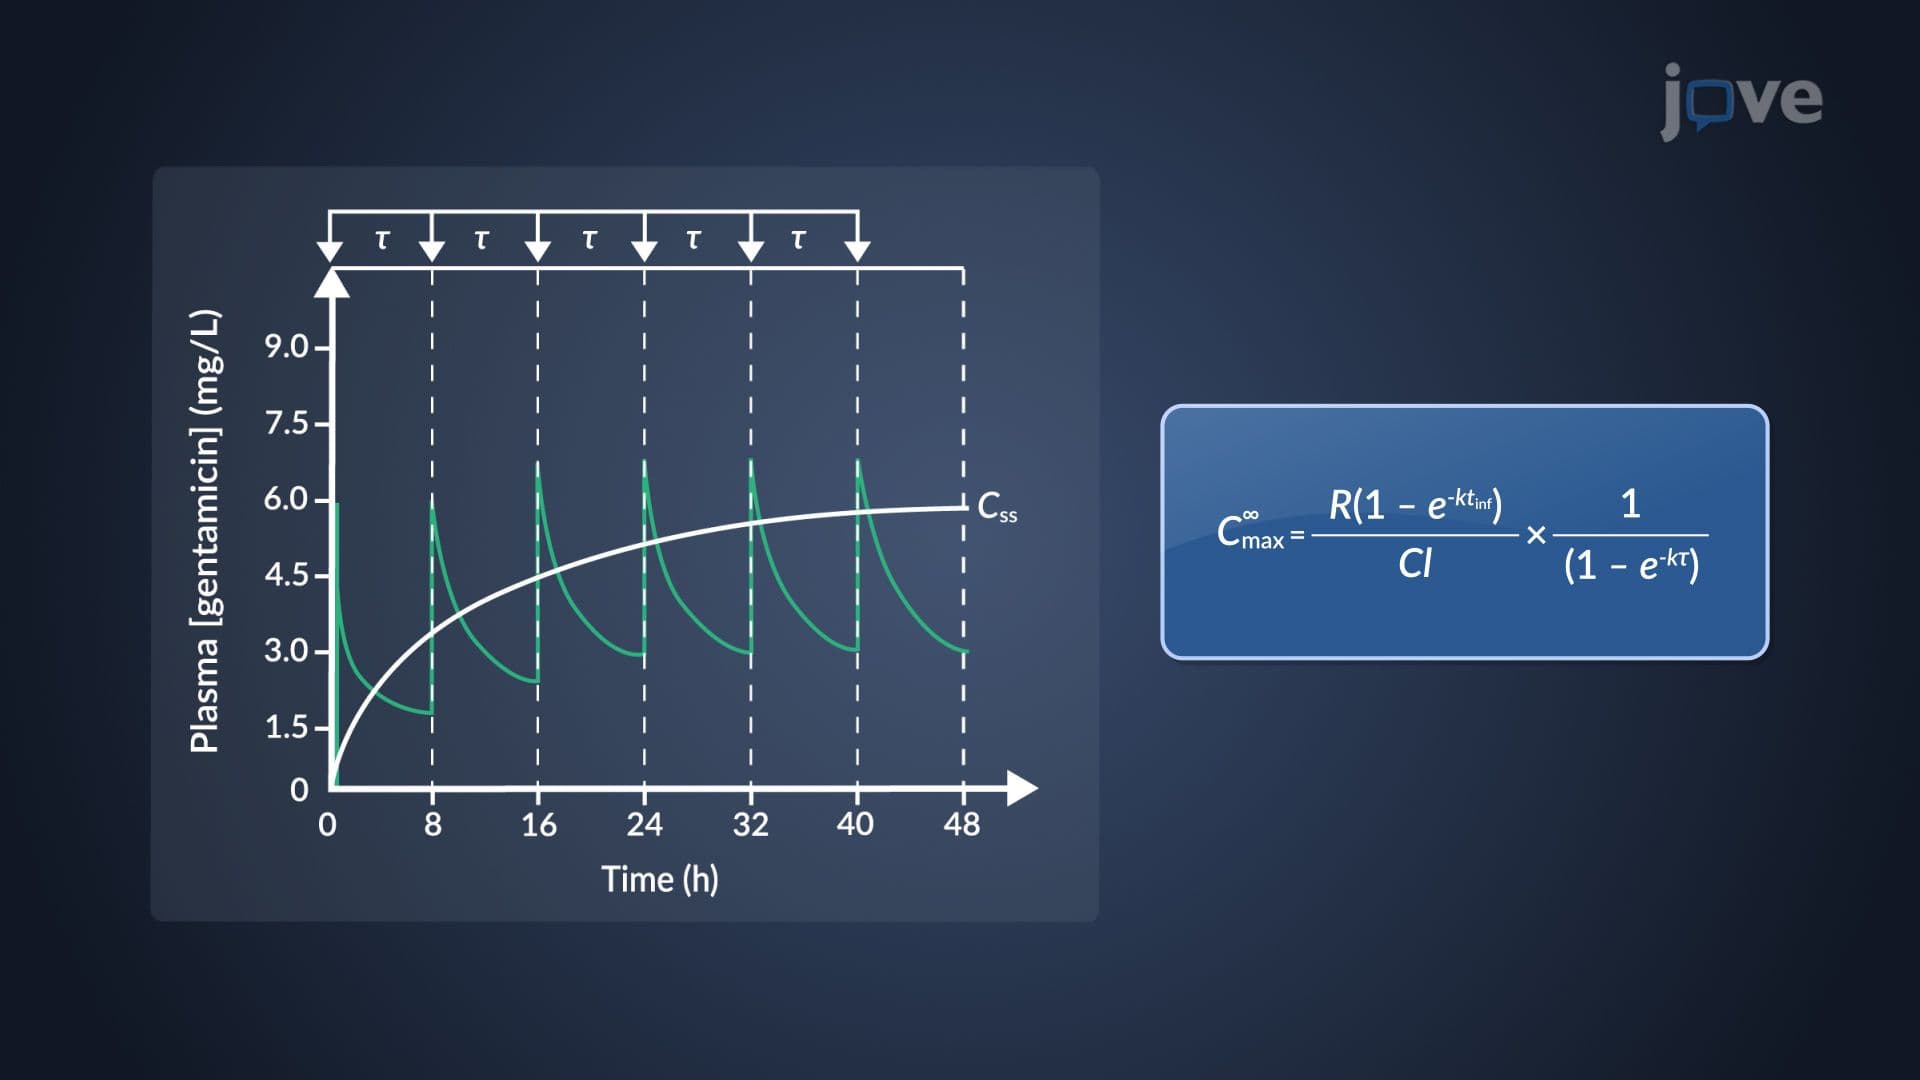
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients