Related Experiment Video
Updated: May 12, 2026
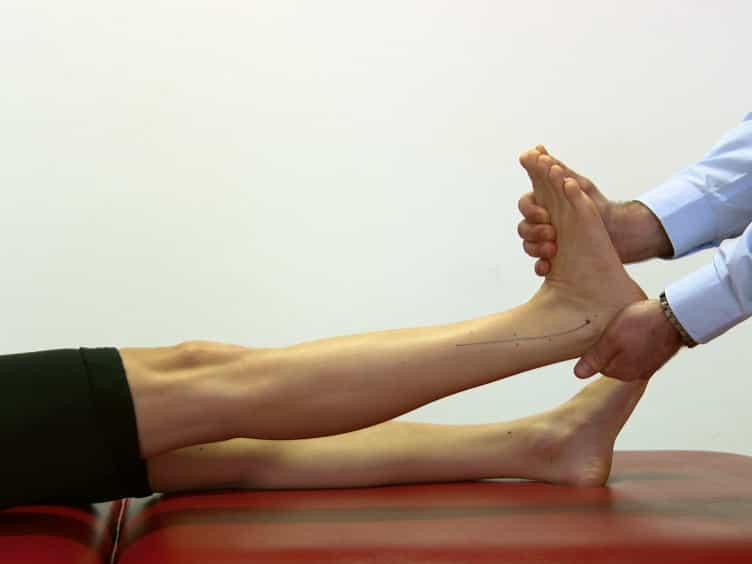
Diagnosis of Musculus Gastrocnemius Tightness - Key Factors for the Clinical Examination
Published on: July 7, 2016
[Piriformis muscle syndrome: etiology, pathogenesis, clinical manifestations, diagnosis, differential diagnosis and
1vjekoslav.grgic@zg.t-com.hr

Abstract:
The term 'piriformis syndrome' (PS), introduced by Robinson in 1947, implies a group of signs and symptoms caused by piriformis muscle (PM) disorders. Since PM disorders lead to irritation/compression of the anatomic structures passing under its belly, the main clinical PS signs and symptoms are actually the clinical signs and symptoms of irritation/ compression of neural and vascular structures passing through the infrapiriform foramen: sciatic nerve/SN, inferior gluteal nerve, posterior femoral cutaneous nerve, pudendal nerve, inferior gluteal artery and vein and inferior pudendal artery and vein. The clinical picture is usually dominated by signs and symptoms of irritation/compression of SN (SN irritation --> low back and buttock pain, sciatica,paresthesias in distribution of SN; SN compression --> low back and buttock pain,sciatica, paresthesias and neurologic deficit in distribution of SN). Irritation/compression of other structures can result in the following signs and symptoms: inferior gluteal nerve --> atrophy of gluteal muscles; posterior femoral cutaneous nerve --> pain, paresthesias and sensory disturbances in the posterior thigh; pudendal nerve --> pudendal neuralgia, painful sexual intercourse (dyspareunia), sexual dysfunction, urination and defecation problems; inferior gluteal artery --> ischemic buttock pain; inferior pudendal artery --> ischemic pain in the area of external sex organs, perineum and rectum, sexual dysfunction, urination and defecation problems; inferior gluteal vein --> venous stasis in gluteal area; inferior pudendal vein --> venous stasis in external sex organs and rectum. Functional/non-organic and organic PM disorders can cause PS: spasm, shortening, hypertrophy, anatomic variations, edema, fibrosis, adhesions, hematoma, atrophy, cyst, bursitis, abscess, myositis ossificans, endometriosis, tumors (functional disorders: PM spasm and shortening). The most common causes for PS are PM spasm, shortening and hypertrophy and anatomic variations of PM and SN. In 5-6% of patients with low back pain and/or unilateral sciatica, the pain is caused by PM disorders. PS diagnosis can be made on the basis of anamnesis, clinical picture, clinical examination, EMNG, perisciatic anesthetic block of PM and radiological exams (pelvis/PM MRI; MR neurography of LS plexus and SN). PS therapy includes medicamentous therapy, physical therapy, kynesitherapy, acupuncture, therapeutic perisciatic blocks, botulinum toxin injections and surgical treatment (tenotomy of PM, neurolysis of SN).

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Irritable Bowel Syndrome
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations