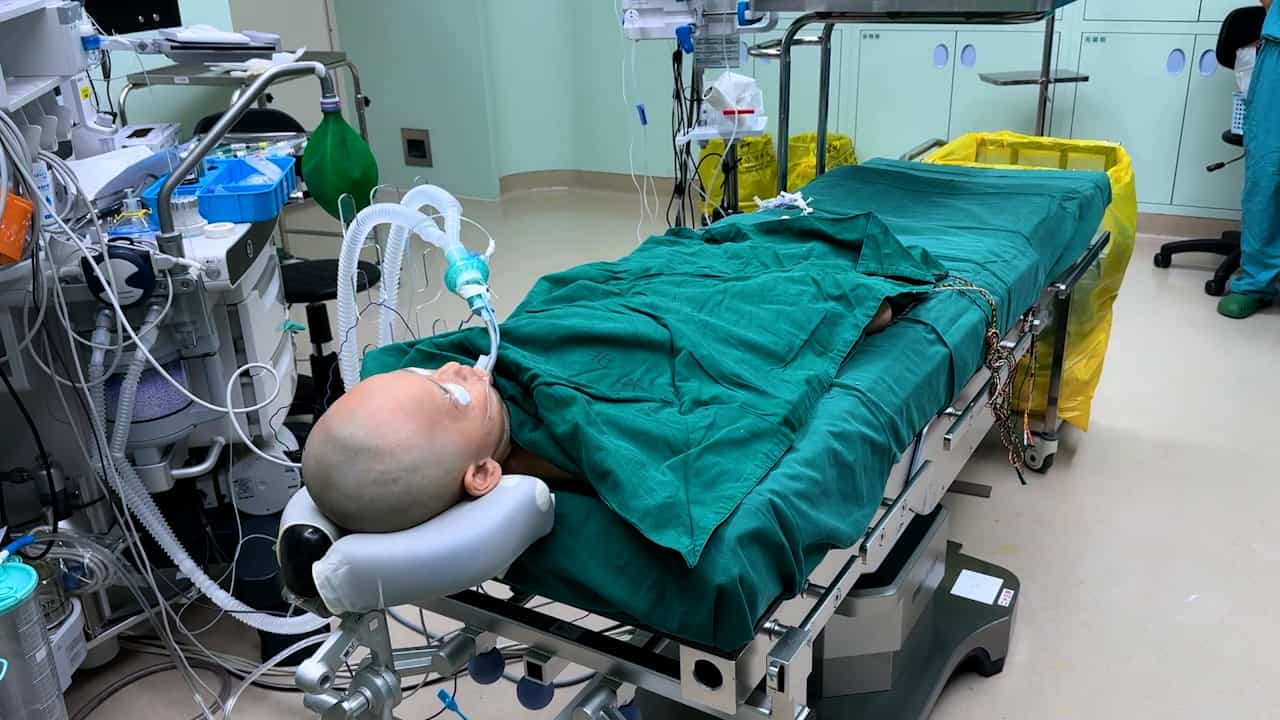

Time to pediatric epilepsy surgery is longer and developmental outcomes lower for government compared with private
Jason S Hauptman1, Andrew Dadour, Taemin Oh
1Department of Neurosurgery, Mattel Children's Hospital, David Geffen School of Medicine, University of California, Los Angeles, California, USA.

Insights
Children with private insurance experienced shorter wait times for epilepsy surgery compared to those with Medicaid. This difference in access was linked to lower developmental scores in children with Medicaid before surgery, suggesting potential delays in care.
Area of Science:
- Pediatric Neurology
- Health Services Research
- Socioeconomic Determinants of Health
Background:
- Socioeconomic factors, including insurance type, may impact the timing of epilepsy surgery referral and subsequent developmental outcomes in pediatric patients.
- Understanding these disparities is crucial for improving access to timely surgical intervention for children with epilepsy.
Purpose of the Study:
- To investigate the association between insurance type (private vs. state-provided Medicaid) and the time interval from seizure onset to epilepsy surgery in pediatric patients.
- To determine if insurance type influences developmental quotients (DQ) in pediatric patients undergoing epilepsy surgery.
Main Methods:
- Retrospective cohort study of 420 pediatric patients undergoing epilepsy surgery.
- Patients were categorized by insurance: Medicaid (California Children's Services) or private insurance (PPO, HMO, Indemnity).
- Time intervals (seizure onset to referral, seizure onset to surgery) and Vineland developmental assessments were compared between insurance groups using log-rank tests.
Main Results:
- Children with Medicaid had significantly longer intervals from seizure onset to referral and to surgery compared to those with private insurance.
- A subset of children with Medicaid showed lower pre- and post-surgery Vineland scores compared to those with private insurance.
- Insurance type did not correlate with seizure severity, surgical approach, etiology, seizure control post-surgery, or complication rates.
Conclusions:
- Private insurance is associated with shorter referral and surgical intervals for pediatric epilepsy surgery compared to Medicaid.
- Shorter intervals in the private insurance group may be linked to better developmental outcomes, although lower scores were observed in the Medicaid group pre-surgery.
- Findings suggest potential delays in access to care for children with state insurance, necessitating further investigation into long-term developmental impacts.
Background:
It is unclear if socioeconomic factors like type of insurance influence time to referral and developmental outcomes for pediatric patients undergoing epilepsy surgery.
Objective:
This study determined whether private compared with state government insurance was associated with shorter intervals of seizure onset to surgery and better developmental quotients for pediatric patients undergoing epilepsy surgery.
Methods:
A consecutive cohort (n = 420) of pediatric patients undergoing epilepsy surgery were retrospectively categorized into those with Medicaid (California Children's Services; n = 91) or private (Preferred Provider Organization, Health Maintenance Organization, Indemnity; n = 329) insurance. Intervals from seizure onset to referral and surgery and Vineland developmental assessments were compared by insurance type with the use of log-rank tests.
Results:
Compared with private insurance, children with Medicaid had longer intervals from seizure onset to referral for evaluation (log-rank test, P = .034), and from seizure onset to surgery (P = .017). In a subset (25%) that had Vineland assessments, children with Medicaid compared with private insurance had lower Vineland scores presurgery (P = .042) and postsurgery (P = .003). Type of insurance was not associated with seizure severity, types of operations, etiology, postsurgical seizure-free outcomes, and complication rate.
Conclusion:
Compared with Medicaid, children with private insurance had shorter intervals from seizure onset to referral and to epilepsy surgery, and this was associated with lower Vineland scores before surgery. These findings may reflect delayed access for uninsured children who eventually obtained state insurance. Reasons for the delay and whether longer intervals before epilepsy surgery affect long-term cognitive and developmental outcomes warrant further prospective investigations.

Related Concept Videos
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion