Related Experiment Video
Updated: May 12, 2026

Combined Near-infrared Fluorescent Imaging and Micro-computed Tomography for Directly Visualizing Cerebral Thromboemboli
Published on: September 25, 2016
Carotid artery free-floating thrombus caused by paradoxical embolization from greater saphenous vein ascending
Luigi Irace1, Roberto Gabrielli, Maria Sofia Rosati
1Department of Emergency Policlinico Umberto I, Sapienza University of Rome, Rome Italy.

Stroke of unknown origin in young patients is seen to be closely correlated with patent foramen ovale (PFO) than stroke in patients with established stroke mechanisms. We report a case of a young woman without cardiovascular risk factors who was admitted to our emergency department with listlessness and altered mental status. The clinical examination revealed right lower limb swelling. Magnetic resonance imaging and contrast-enhanced computed tomographic scans revealed a free floating thrombus of the left internal carotid artery (ICA) with a large bilateral frontal ischemic lesion. The diagnosis of a medium-sized PFO with moderate right-to-left contrast shunting was made after transesophageal echocardiography. No other cardiac sources for embolization were detected, while an ascending thrombophlebitis of the right greater saphenous vein was detected by venous Doppler ultrasonography. These findings support the diagnosis of ICA free-floating thrombus caused by paradoxical embolization (via the PFO) of clot from the greater saphenous vein. The patient underwent emergency saphenofemoral disconnection with femoral vein thrombectomy and subsequently carotid artery thrombectomy under general anesthesia. No carotid atheromatous wall lesions were detected at surgical exploration; no immunologic pathology, hypercoagulable status, or malignancy were recorded. No hemorrhagic cerebral complications were observed in the postoperative period, and the patient had an improvement of her neurologic status (a reduction of the National Institutes of Health Stroke Scale score from 7 to 3). Her recovery was uneventful. The patient was transferred for rehabilitation on postoperative day 5 with oral anticoagulation. Six-month ultrasound follow-up revealed deep and superficial venous system and carotid artery patency. The patient was asymptomatic and anticoagulation was discontinued. Paradoxical cerebral embolization through a PFO is a rare phenomenon that, in our patient, appeared to have resulted in stroke caused by a free-floating thrombus in the ICA. Accurate evaluation of carotid and lower limb veins by duplex scan is mandatory in cases of stroke of unknown origin, and urgent surgical repair can be useful in order to improve the clinical outcome.
Stroke of unknown origin in young patients is seen to be closely correlated with patent foramen ovale (PFO) than stroke in patients with established stroke mechanisms. We report a case of a young woman without cardiovascular risk factors who was admitted to our emergency department with listlessness and altered mental status. The clinical examination revealed right lower limb swelling. Magnetic resonance imaging and contrast-enhanced computed tomographic scans revealed a free floating thrombus of the left internal carotid artery (ICA) with a large bilateral frontal ischemic lesion. The diagnosis of a medium-sized PFO with moderate right-to-left contrast shunting was made after transesophageal echocardiography. No other cardiac sources for embolization were detected, while an ascending thrombophlebitis of the right greater saphenous vein was detected by venous Doppler ultrasonography. These findings support the diagnosis of ICA free-floating thrombus caused by paradoxical embolization (via the PFO) of clot from the greater saphenous vein. The patient underwent emergency saphenofemoral disconnection with femoral vein thrombectomy and subsequently carotid artery thrombectomy under general anesthesia. No carotid atheromatous wall lesions were detected at surgical exploration; no immunologic pathology, hypercoagulable status, or malignancy were recorded. No hemorrhagic cerebral complications were observed in the postoperative period, and the patient had an improvement of her neurologic status (a reduction of the National Institutes of Health Stroke Scale score from 7 to 3). Her recovery was uneventful. The patient was transferred for rehabilitation on postoperative day 5 with oral anticoagulation. Six-month ultrasound follow-up revealed deep and superficial venous system and carotid artery patency. The patient was asymptomatic and anticoagulation was discontinued. Paradoxical cerebral embolization through a PFO is a rare phenomenon that, in our patient, appeared to have resulted in stroke caused by a free-floating thrombus in the ICA. Accurate evaluation of carotid and lower limb veins by duplex scan is mandatory in cases of stroke of unknown origin, and urgent surgical repair can be useful in order to improve the clinical outcome.
Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
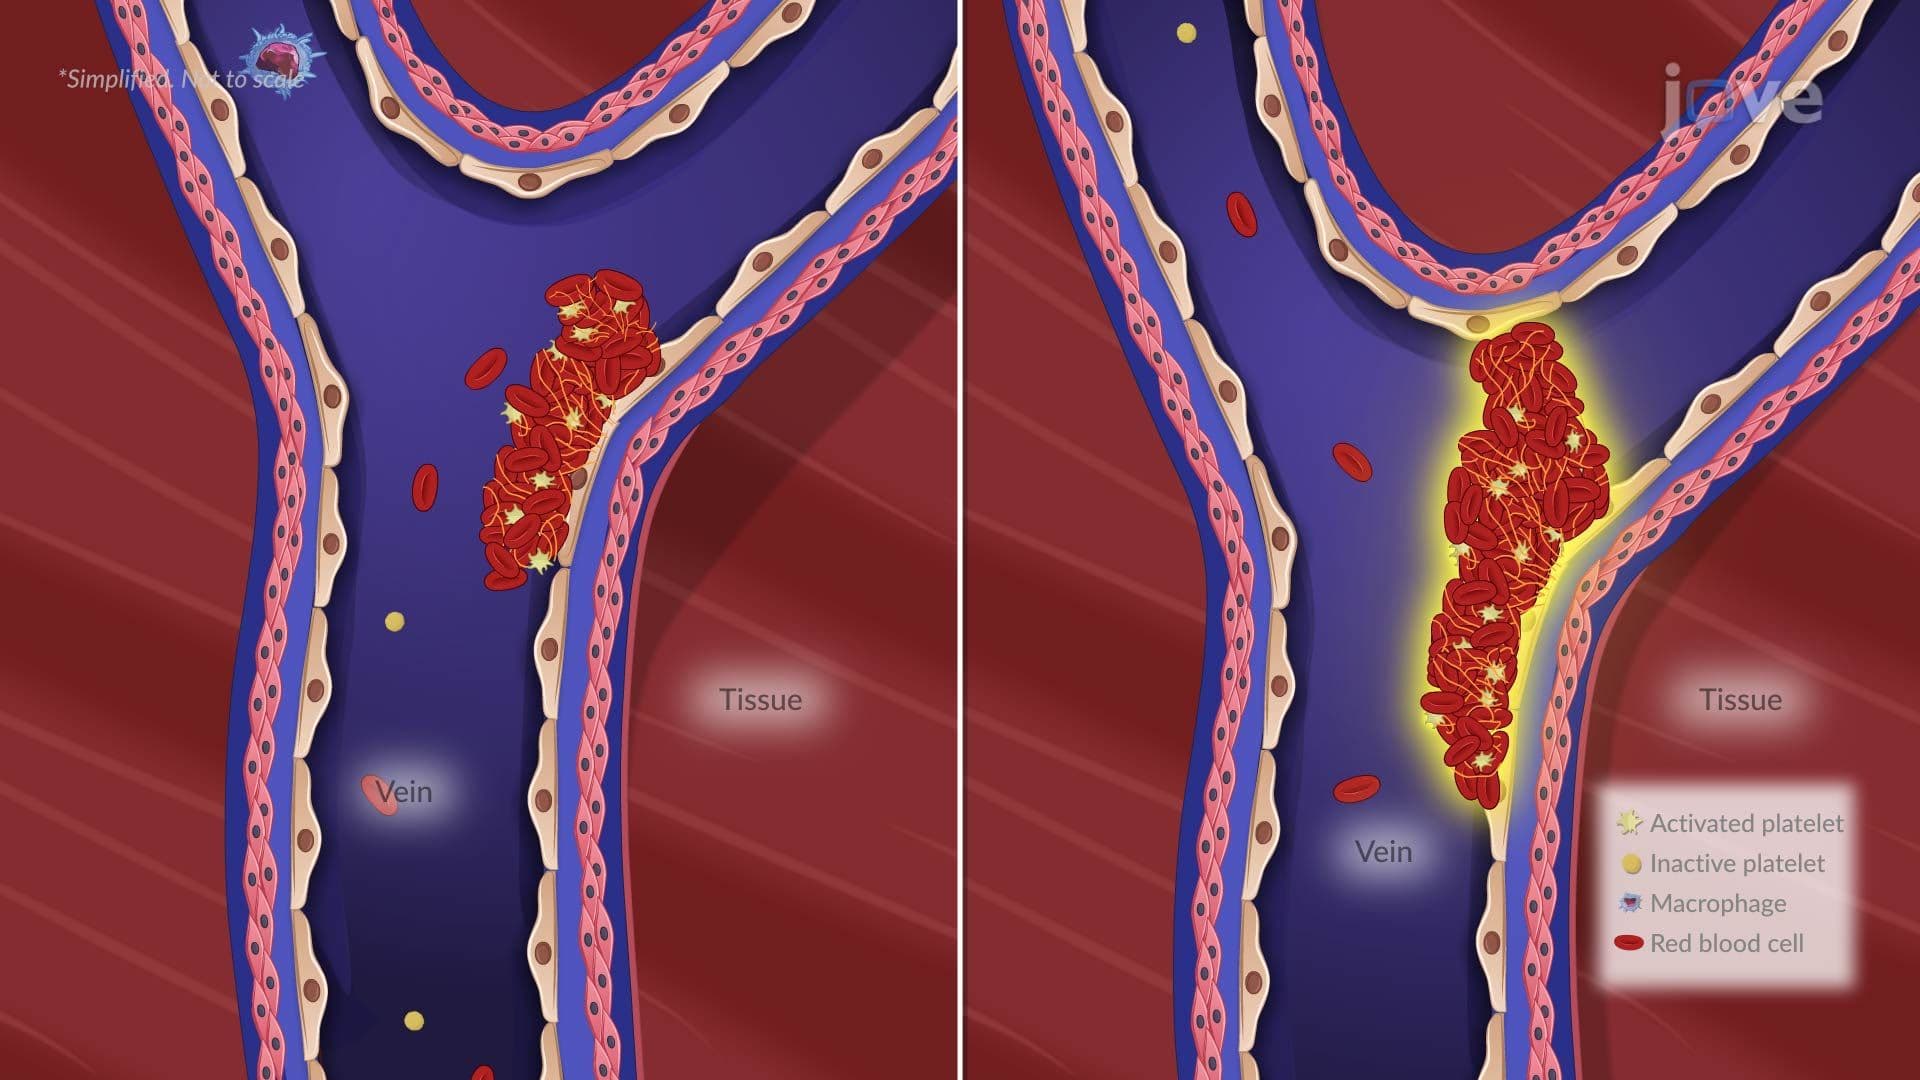 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism I: Introduction
 01:30
Peripheral Artery Disease I: Introduction
 01:26
Transient Ischemic Attack l: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care