Related Experiment Video
Updated: May 11, 2026
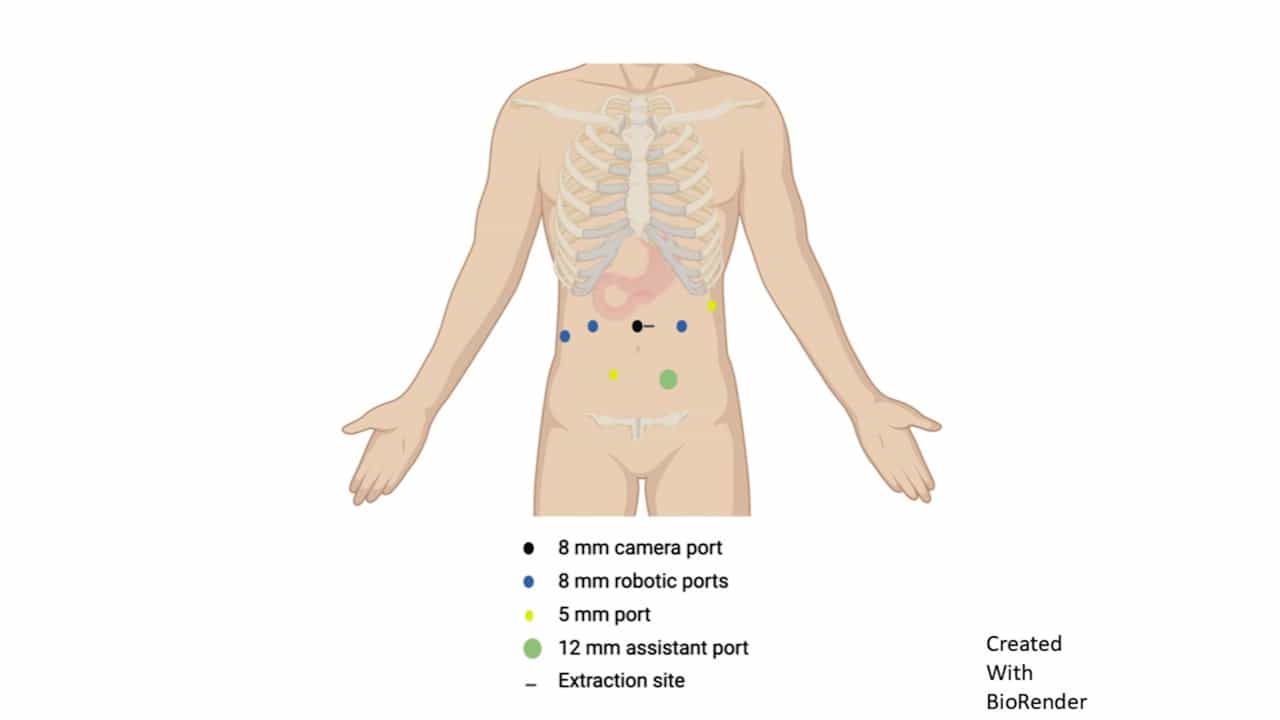

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Resistance to treatment in gastrointestinal stromal tumours: what radiologists should know
S H Tirumani1, J P Jagannathan, J L Hornick
1Department of Imaging, Dana Farber Cancer Institute, Harvard Medical School, Boston, MA 02215, USA.stirumani@partners.org

Abstract:
Gastrointestinal stromal tumour resistance to treatment with imatinib occurs due to pre-existing or acquired mutations. Computed tomography and positron-emission tomography play an essential role in prompt recognition of resistance to treatment. Primary resistance to treatment, which is encountered in the first 6 months of treatment, is associated with specific mutations. Imaging of these tumours shows no anatomical or metabolic response to treatment. Secondary resistance to treatment, which develops after an initial response, is associated with a variety of mutations acquired after the start of treatment. Imaging findings of secondary resistance are of disease progression.
Insights
Gastrointestinal stromal tumour (GIST) resistance to imatinib is caused by mutations. Imaging like CT and PET scans help detect this resistance early, whether it
Area of Science:
- Oncology
- Medical Imaging
- Molecular Biology
Background:
- Gastrointestinal stromal tumours (GIST) can develop resistance to imatinib therapy.
- This resistance is often linked to genetic mutations within the tumour.
- Early identification of resistance is crucial for effective patient management.
Purpose of the Study:
- To highlight the role of imaging in detecting imatinib resistance in GIST.
- To differentiate between primary and secondary resistance mechanisms.
- To correlate imaging findings with specific mutation types.
Main Methods:
- Review of clinical data and imaging findings (CT, PET) in GIST patients.
- Analysis of mutation status in relation to treatment response.
- Correlation of imaging features with primary and secondary resistance patterns.
Main Results:
- Imatinib resistance in GIST is driven by pre-existing or acquired mutations.
- Computed tomography (CT) and positron-emission tomography (PET) are vital for recognizing resistance.
- Primary resistance (within 6 months) shows no imaging response and links to specific mutations.
- Secondary resistance develops after initial response, linked to acquired mutations, with imaging showing disease progression.
Conclusions:
- Imaging plays a key role in the prompt recognition of imatinib resistance in GIST.
- Distinguishing primary and secondary resistance through imaging and mutation analysis is important.
- Understanding resistance mechanisms guides further therapeutic strategies.
