Related Experiment Video
Updated: May 11, 2026
CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
[Faults and failure of tonsil surgery and other standard procedures in otorhinolaryngology]
1Klinik für HNO-Krankheiten, Plastische Kopf- und Hals-Chirurgie, Allergologie Kliniken Maria Hilf, Mönchengladbach. jochen.windfuhr@mariahilf.de

Septoplasty, tonsillectomy (with and without adenoidectomy) and cervical lymph node excision are amongst the most common 50 inpatient operations in Germany. Intracapsular tonsillectomies (i.e., tonsillotomies) are increasingly performed. The aim of this study was to evaluate alleged medical malpractice, technical traps and pitfalls associated with tonsillectomy (TE), adenoidectomy (AE), tonsillotomy (TT), septoplasty (SP) and cervical lymph node excision (LN).A questionnaire was sent to the Regional Medical Conciliation Boards, Medical Services of the Health Insurance Companies (MDK) and Regional Institutes of Forensic Medicine in Germany to collect anonymized cases of complications or medico legal implications following TE, TT, AE, LN and SP. The results were discussed in the light of the contemporary medical literature and published verdicts in Germany.The response rate of our survey was 55.9%. The Institutes of Forensic Medicine contributed 9 cases, 49 cases were submitted by the Regional Conciliation Boards and none by MDK. All forensic cases were associated with exsanguinations following tonsillectomy including 2 children (5 and 8 years of age) and 7 adults (aged 20-69 years). The fatal post-tonsillectomy hemorrhage (PTH) had occurred 8.7 days on average; 4 patients experienced the bleeding episode at home (day 5, 8, 9 and 17, respectively). Repeated episodes of bleeding requiring surgical intervention had occurred in 6 patients. 3 Conciliation Boards submitted expert opinions concerning cases TT (1), AE (4), LN (3), SP (16) and TE (25). Cases with lethal outcome were not registered. Only 3 of the 49 cases were assessed as surgical malpractice (6.1%) including lesion of the spinal accessory nerve, wrong indication for TE and dental lesion after insertion of the mouth gag. The review of the medico legal literature yielded 71 published verdicts after AE and TE (29), LN (28) and SP (14) of which 37 resulted in compensation of malpractice after LN (16; 57%), TE (11; 41%), SP (8; 57%) and AE (2; 100%). There were 16 cases of PTH amongst 27 trials after TE resulting either in death (5) or apallic syndrome (5). Bleeding complications had occurred on the day of surgery in only 2 patients. 16 trials were based on malpractice claims following SP encompassing lack of informed consent (6), anosmia (4), septal perforation (2), frontobasal injury (2) and dry nose (2). Trials based on LN were associated exclusively with a lesion of the spinal accessory nerve (28), including lack of informed consent in 19 cases. 49 cases (69%) were decided for the defendant, 22 (31%) were decided for the plaintiff with monetary compensation in 7 of 29 AE/TE-trials, 9 of 28 LN-trials and 6 of 14 SP-trials. Lack of informed consent was not registered for AE/TE but LN (11) and SP (2).Complicated cases following TE, TT, ATE, SP and LN are not systematically collected in Germany. It can be assumed, that not every complicated case is published in the medical literature or law journals and therefore not obtainable for scientific research. Alleged medical malpracice is proven for less than 6% before trial stage. Approximately half of all cases result in a plaintiff verdict or settlement at court. Proper documentation of a thorough counselling, examination, indication, informed consent and follow-up assists the surgeon in litigation. An adequate complication management of PTH is essential, including instructions for the patients/parents, instructions for the medical staff, readily available surgical instruments and appropriate airway management in an interdisciplinary approach. Electrosurgical tonsillectomy techniques were repeatedly labeled as a risk factor for bleeding complications following TE. Institutions should analyse the individual PTH rate on a yearly basis. Contradictory expert opinions and verdicts of the courts concerning spinal accesory nerve lesions following LN are due to a lack of a surgical standard.
Septoplasty, tonsillectomy (with and without adenoidectomy) and cervical lymph node excision are amongst the most common 50 inpatient operations in Germany. Intracapsular tonsillectomies (i.e., tonsillotomies) are increasingly performed. The aim of this study was to evaluate alleged medical malpractice, technical traps and pitfalls associated with tonsillectomy (TE), adenoidectomy (AE), tonsillotomy (TT), septoplasty (SP) and cervical lymph node excision (LN).A questionnaire was sent to the Regional Medical Conciliation Boards, Medical Services of the Health Insurance Companies (MDK) and Regional Institutes of Forensic Medicine in Germany to collect anonymized cases of complications or medico legal implications following TE, TT, AE, LN and SP. The results were discussed in the light of the contemporary medical literature and published verdicts in Germany.The response rate of our survey was 55.9%. The Institutes of Forensic Medicine contributed 9 cases, 49 cases were submitted by the Regional Conciliation Boards and none by MDK. All forensic cases were associated with exsanguinations following tonsillectomy including 2 children (5 and 8 years of age) and 7 adults (aged 20-69 years). The fatal post-tonsillectomy hemorrhage (PTH) had occurred 8.7 days on average; 4 patients experienced the bleeding episode at home (day 5, 8, 9 and 17, respectively). Repeated episodes of bleeding requiring surgical intervention had occurred in 6 patients. 3 Conciliation Boards submitted expert opinions concerning cases TT (1), AE (4), LN (3), SP (16) and TE (25). Cases with lethal outcome were not registered. Only 3 of the 49 cases were assessed as surgical malpractice (6.1%) including lesion of the spinal accessory nerve, wrong indication for TE and dental lesion after insertion of the mouth gag. The review of the medico legal literature yielded 71 published verdicts after AE and TE (29), LN (28) and SP (14) of which 37 resulted in compensation of malpractice after LN (16; 57%), TE (11; 41%), SP (8; 57%) and AE (2; 100%). There were 16 cases of PTH amongst 27 trials after TE resulting either in death (5) or apallic syndrome (5). Bleeding complications had occurred on the day of surgery in only 2 patients. 16 trials were based on malpractice claims following SP encompassing lack of informed consent (6), anosmia (4), septal perforation (2), frontobasal injury (2) and dry nose (2). Trials based on LN were associated exclusively with a lesion of the spinal accessory nerve (28), including lack of informed consent in 19 cases. 49 cases (69%) were decided for the defendant, 22 (31%) were decided for the plaintiff with monetary compensation in 7 of 29 AE/TE-trials, 9 of 28 LN-trials and 6 of 14 SP-trials. Lack of informed consent was not registered for AE/TE but LN (11) and SP (2).Complicated cases following TE, TT, ATE, SP and LN are not systematically collected in Germany. It can be assumed, that not every complicated case is published in the medical literature or law journals and therefore not obtainable for scientific research. Alleged medical malpracice is proven for less than 6% before trial stage. Approximately half of all cases result in a plaintiff verdict or settlement at court. Proper documentation of a thorough counselling, examination, indication, informed consent and follow-up assists the surgeon in litigation. An adequate complication management of PTH is essential, including instructions for the patients/parents, instructions for the medical staff, readily available surgical instruments and appropriate airway management in an interdisciplinary approach. Electrosurgical tonsillectomy techniques were repeatedly labeled as a risk factor for bleeding complications following TE. Institutions should analyse the individual PTH rate on a yearly basis. Contradictory expert opinions and verdicts of the courts concerning spinal accesory nerve lesions following LN are due to a lack of a surgical standard.
Related Concept Videos
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:26
Tonsillitis II: Management
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
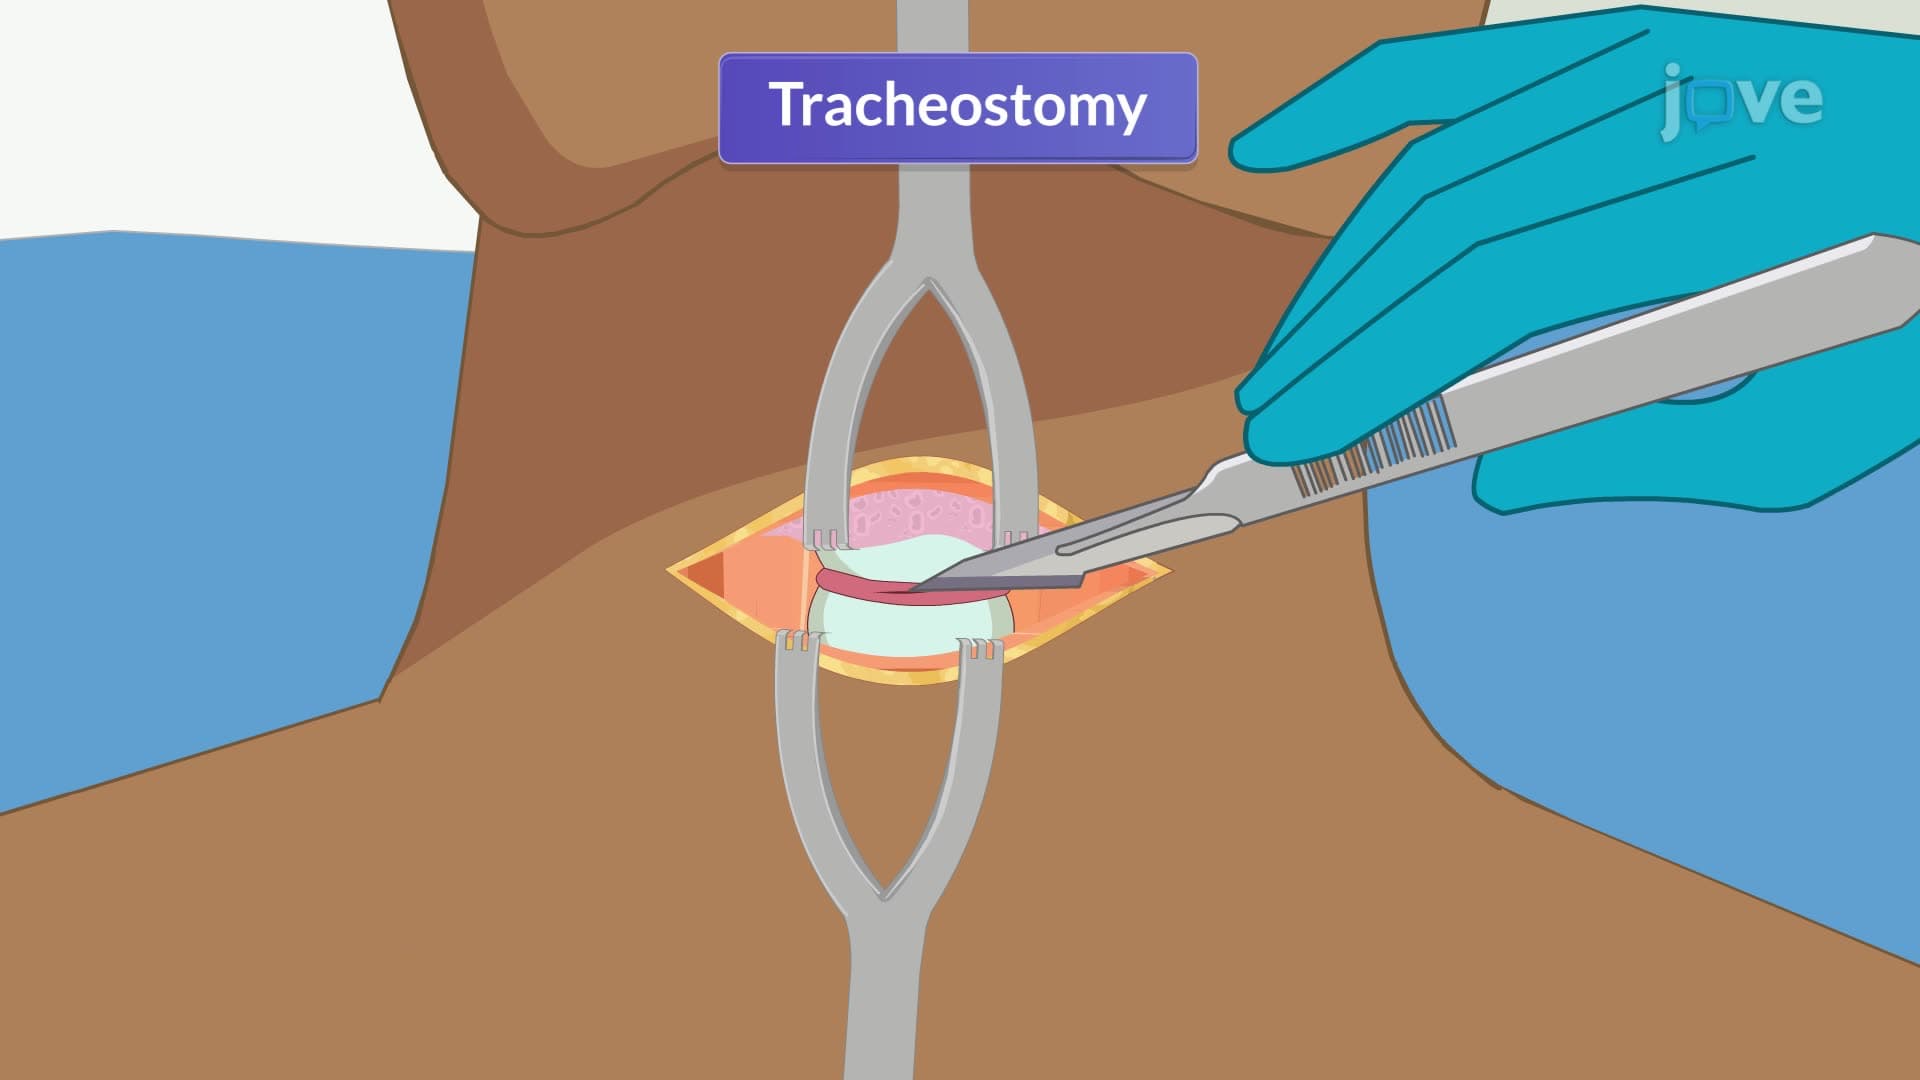
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...