Spontaneous anterior interosseous nerve syndrome: clinical analysis of eleven surgical cases
Related Experiment Video
Updated: May 11, 2026
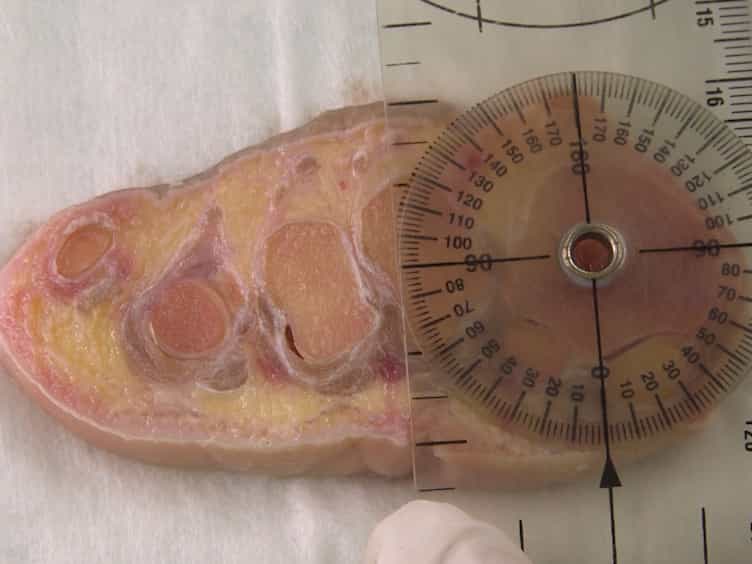
An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Il-Jung Park1, Youn-Tae Roh, Changhoon Jeong
1Department of Orthopaedic Surgery, Bucheon St. Mary's Hospital, The Catholic University of Korea , Bucheon , Korea.

Abstract:
The aetiology of anterior interosseous nerve (AIN) syndrome and an optimal treatment strategy remain controversial. Eleven patients with spontaneous AIN syndrome, who were treated by surgical exploration, were reviewed at a mean of 32.5 months after the operation. Eight men and three women were included in the study. None of the patients had a history of trauma and there was no evidence of a neuropathy other than AIN syndrome. Six patients showed complete paralysis of the flexor pollicis longus (FPL) and the flexor digitorum profundus of the index finger (FDS1). Five patients had incomplete paralysis, with isolated lesions of the FPL in two and the FDP1 in three. Surgery was performed 7.8 months after the onset of paralysis. The most common structure of nerve compression was a fibrous band of the flexor digitorum sublimis muscle. However, no definitive compression site or anatomic abnormality could be found in four patients. Ten of the 11 patients had recovered muscle strength above grade 4 within 12 months of the operation. Good results were obtained in 10 patients and fair in only one at final assessment. Four patients (one man and three women) raised cosmetic concerns due to excessive scar formation on the upper forearm. Surgical exploration is recommended only in cases where AIN syndrome is apparent, no other neuronal lesions are apparent, and where there was no recovery after 6 months of conservative treatment. Careful preoperative examination is essential to avoid misdiagnosis and inappropriate operation, particularly in cases of incomplete AIN syndrome.