Incidence of concomitant airway anomalies when using the university of California, Los Angeles, protocol for neonatal mandibular distraction
Related Experiment Video
Updated: May 11, 2026
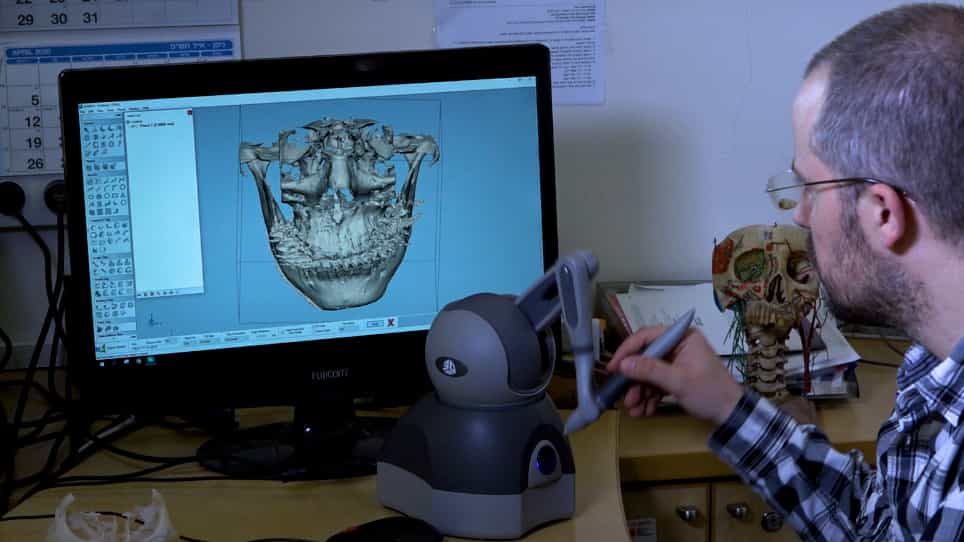
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Brian T Andrews1, Kenneth L Fan, Jason Roostaeian
1Los Angeles, Calif. From the Division of Plastic and Reconstructive Surgery, David Geffen School of Medicine, University of California, Los Angeles.

Background:
In newborns with micrognathia and severe upper airway obstruction, understanding potential airway lesions is important for determining appropriate treatment: observation, mandibular distraction, or tracheostomy. When concomitant airway anomalies are present, mandibular distraction is often unsuccessful at alleviating causes of obstruction, mandating the need for tracheostomy. The first part of this study evaluates 10-year results using the University of California, Los Angeles, algorithm for surgical candidacy to identify patients who will benefit from neonatal mandibular distraction. The second part describes the concomitant airway abnormalities found at the time of diagnostic laryngoscopy/bronchoscopy and how these anomalies affect neonatal distraction candidacy of these patients.
Methods:
Newborns admitted to the neonatal intensive care unit with micrognathia and upper airway obstruction (n = 133) were subjected to a decision tree model protocol formulated by a multidisciplinary team at the University of California, Los Angeles, to decide on appropriate treatment. Concomitant airway abnormalities were recorded and outcomes were documented for the first 5 years of life.
Results:
Fifty-five percent of patients underwent internal mandibular distraction with 97 percent success. Home observation with a nasopharyngeal tube was chosen in 11 percent of patients, and 34 percent had tracheostomies. On endoscopic examination, 51.7 percent of the nondistracted patients had concomitant airway anomalies: laryngomalacia (53.3 percent), tracheal web (20.0 percent), vocal cord paralysis (13.3 percent), epiglottal collapse (6.7 percent), and infraglottal narrowing (6.7 percent).
Conclusions:
For the management of neonatal upper airway obstruction with micrognathia, a decision tree algorithm is useful to determine candidates for mandibular distraction. Diagnostic laryngoscopy/bronchoscopy is an important component of this algorithm because a multitude of airway anomalies may be present.
Clinical Question/Level Of Evidence:
: Therapeutic, IV.
More Related Videos
 10:42
A Postoperative Evaluation Guideline for Computer-Assisted Reconstruction of the Mandible
Published on: January 28, 2020
 08:03
Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
