Related Experiment Video
Updated: May 11, 2026
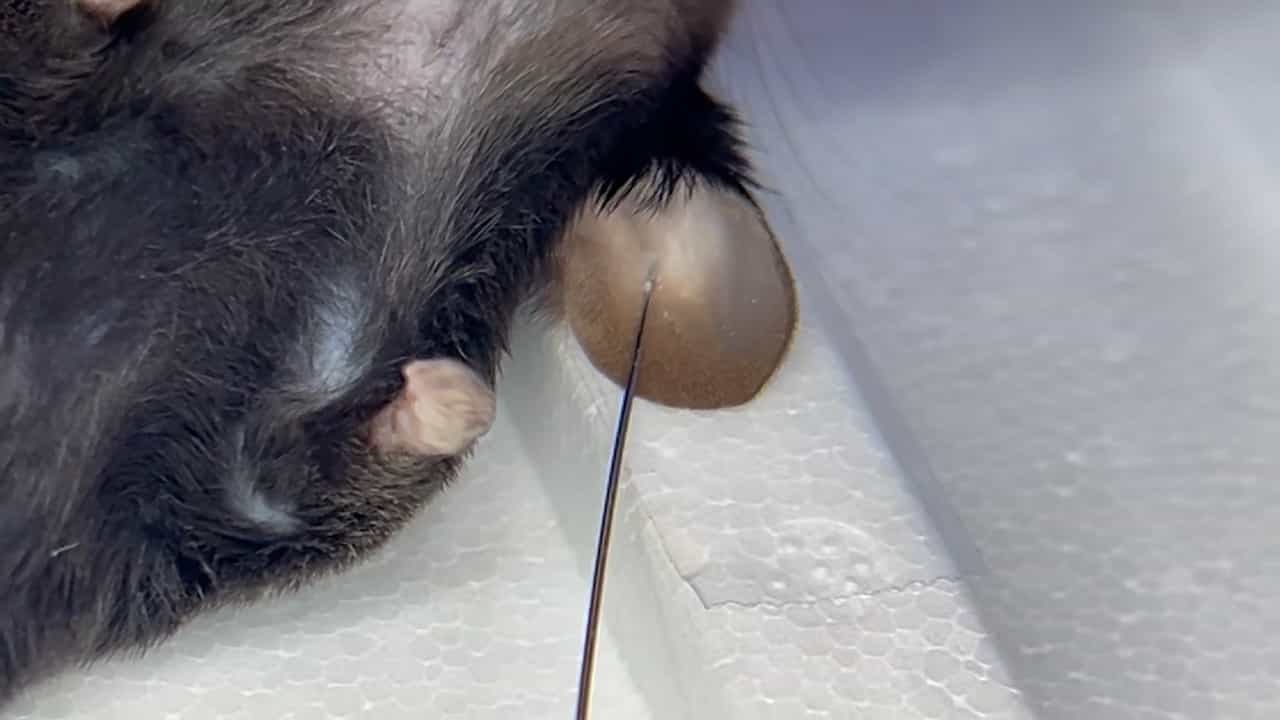

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
Interventions for the prevention of mycobacterium avium complex in adults and children with HIV
Muhammed Mubashir B Uthman1, Olalekan A Uthman, Ismail Yahaya
1Department of Epidemiology & Community Health, Faculty of Clinical Sciences, College of Health Sciences, University of Ilorin,Ilorin, Nigeria. uthmanmb@yahoo.com

Background:
Mycobacterium avium complex (MAC) infection is a common complication of advanced acquired immunodeficiency syndrome (AIDS) disease and is an independent predictor of mortality and shortened survival.
Objectives:
To determine the effectiveness and safety of interventions aimed at preventing MAC infection in adults and children with HIV infection.
Search Methods:
We searched MEDLINE, EMBASE, and The Cochrane Library (search date December 2012).
Selection Criteria:
Randomised controlled trials comparing different strategies for preventing MAC infection in HIV-infected individuals.
Data Collection And Analysis:
Two reviewers independently assessed trial eligibility and quality, and extracted data. Where data were incomplete or unclear, a third reviewer resolved conflicts and/or trial authors were contacted for further details. Development of MAC infection and survival were compared using risk ratios (RR) and 95% confidence intervals (CI). The quality of evidence has been assessed using the GRADE methodology.
Main Results:
Eight studies met the inclusion criteria. Placebo-controlled trials: There was no statistically significant difference between clofazimine and no treatment groups in the number of patients that developed MAC infection (RR 1.01; 95% CI 0.37 to 2.80). Rifabutin (one study; RR 0.48; 95% CI 0.35 to 0.67), azithromycin (three studies; RR 0.37; 95% CI 0.19 to 0.74) and clarithromycin (one study; RR 0.35; 95% CI 0.21 to 0.58) were more effective than placebo in preventing the development of MAC infection. There was no statistically significant difference between those treated with clofazimine (one study; RR 0.98; 95% CI 0.41 to 2.32), rifabutin (one study RR 0.91; 95% CI 0.78 to 1.05), azithromycin (three studies, pooled RR 0.96; 95% CI 0.69 to 1.32) and placebo in number of reported deaths. One study found that the risk of death was reduced by 22% in patients treated with clarithromycin compared to those treated with placebo (RR 0.78; 95% CI 0.64 to 0.96). Monotherapy vs. monotherapy: Patients treated with clarithromycin (RR 0.60; 95% CI 0.41 to 0.89) and azithromycin (RR 0.60; 95% CI 0.40 to 0.89) were 40% less likely to develop MAC infection than those treated with rifabutin. There was no statistically significant difference between those treated with clarithromycin (RR 0.98; 95% CI 0.83 to 1.15), azithromycin (RR 0.98; 95% CI 0.77 to 1.24) and rifabutin in the number of reported deaths. Combination therapy versus monotherapy: There was no statistically significant difference between patients treated with a combination of rifabutin and clarithromycin and those treated with clarithromycin alone (RR 0.74; 95% CI 0.46 to 1.20); and those treated with combination of rifabutin and azithromycin and those treated with azithromycin alone (RR 0.59; 95% CI 1.03). Patients treated with a combination of rifabutin plus clarithromycin were 56% less likely to develop MAC infection than those treated with rifabutin alone (RR 0.44; 95% CI 0.29 to 0.69). Patients treated with a combination of rifabutin plus azithromycin were 65% less likely to develop MAC infection than those treated with rifabutin alone (RR 0.35; 95% CI 0.21 to 0.59). There was no statistically significant difference in the number of reported deaths in all the four different comparisons of prophylactic agents.
Authors' Conclusions:
Based on limited data, azithromycin or clarithromycin appeared to be a prophylactic agent of choice for MAC infection. Further studies are needed, especially direct comparison of clarithromycin and azithromycin. In additions, studies that will compare different doses and regimens are needed.
Insights
Azithromycin and clarithromycin are effective in preventing Mycobacterium avium complex (MAC) infection in individuals with HIV. Further research is needed to compare these macrolide antibiotics directly and explore optimal dosing strategies.
Area of Science:
- Infectious Diseases
- HIV/AIDS Research
- Clinical Pharmacology
Background:
- Mycobacterium avium complex (MAC) infection is a significant complication in advanced acquired immunodeficiency syndrome (AIDS).
- MAC infection independently predicts mortality and reduced survival in individuals with HIV.
- Preventing MAC infection is crucial for improving outcomes in HIV-infected populations.
Purpose of the Study:
- To evaluate the efficacy and safety of various interventions for preventing MAC infection in HIV-infected adults and children.
- To synthesize evidence from randomized controlled trials on MAC infection prophylaxis.
Main Methods:
- Systematic literature search of MEDLINE, EMBASE, and The Cochrane Library up to December 2012.
- Inclusion of randomized controlled trials comparing MAC infection prevention strategies in HIV-infected individuals.
- Data extraction and analysis using risk ratios (RR) and 95% confidence intervals (CI), with GRADE methodology for evidence quality assessment.
Main Results:
- Azithromycin and clarithromycin demonstrated effectiveness in preventing MAC infection compared to placebo.
- Rifabutin was also effective in preventing MAC infection compared to placebo.
- Combination therapy with rifabutin plus clarithromycin or azithromycin showed increased efficacy in preventing MAC infection compared to rifabutin monotherapy.
Conclusions:
- Azithromycin and clarithromycin are recommended as prophylactic agents of choice for MAC infection based on current evidence.
- Further research is warranted, particularly direct comparative studies between azithromycin and clarithromycin.
- Additional studies investigating optimal dosages and regimens for MAC infection prophylaxis are needed.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:10
Retrovirus Life Cycles
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.