Role responsibilities in mechanical ventilation and weaning in pediatric intensive care units: a national survey
Related Experiment Video
Updated: May 11, 2026
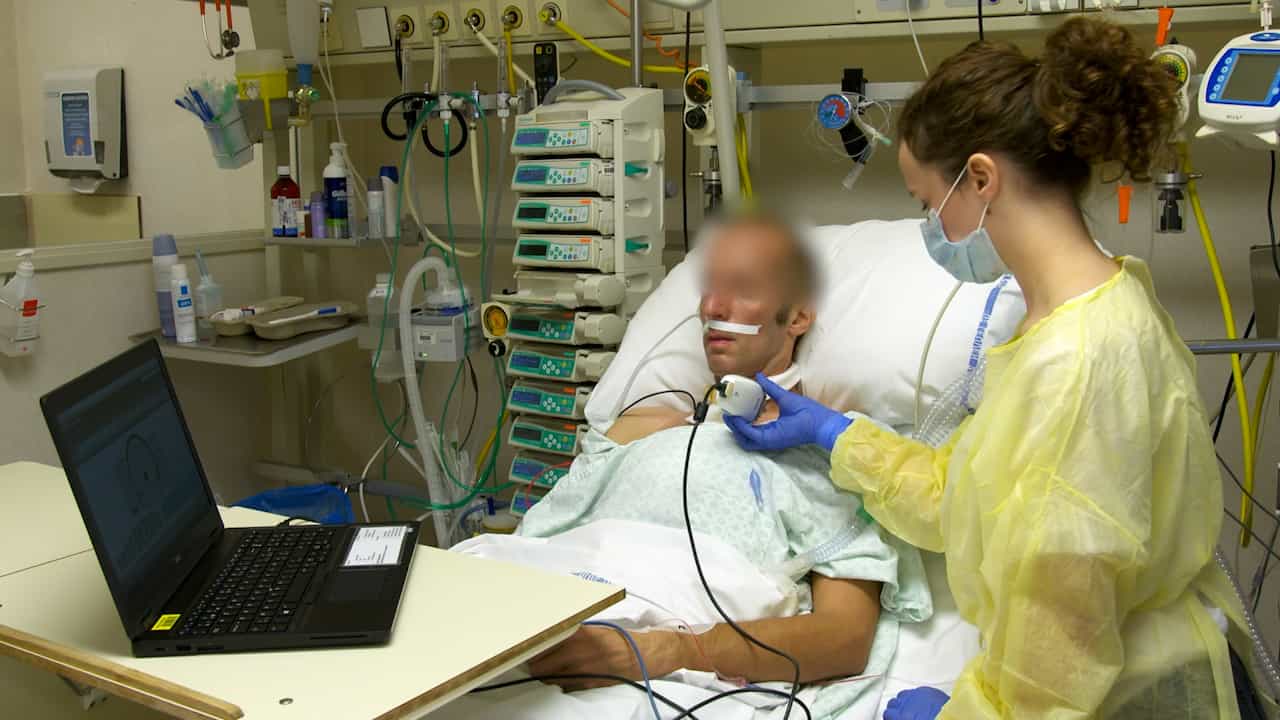
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Bronagh Blackwood1, Carol Junk, Jeremy David Morrell Lyons
1School of Medicine, Dentistry and Biomedical Sciences, Queen's University, Belfast, United Kingdom. b.blackwood@qub.ac.uk

Insights
Physician and nurse collaboration is key for mechanical ventilation and weaning decisions. However, nurses
Area of Science:
- Critical Care Medicine
- Respiratory Therapy
- Nursing Management
Background:
- Organizational processes significantly impact mechanical ventilation duration in ICUs.
- Limited understanding exists regarding role responsibilities and contextual factors influencing timely ventilator liberation.
- Investigating these factors is crucial for optimizing patient outcomes.
Purpose of the Study:
- To identify clinicians responsible for mechanical ventilation and weaning decisions.
- To assess the utilization of ventilation protocols and automated systems.
- To determine the provision of mechanical ventilation education.
Main Methods:
- A mailed survey was distributed to nurse managers in UK pediatric intensive care units.
- The survey focused on decision-making roles, protocol use, and training related to mechanical ventilation.
- A 61% response rate was achieved.
Main Results:
- Most decisions regarding ventilator settings, weaning, and extubation were collaborative between physicians and nurses.
- Ventilation protocols were present in 35% of units, with 18% specifically for weaning.
- Automated closed-loop systems were used in 18% of units, and only 35% of units required competency training for nurses adjusting ventilator settings.
Conclusions:
- While decisions are collaborative, nurses' independent adjustment of ventilator settings is limited.
- Lack of standardized competency programs and infrequent use of non-physician-led weaning protocols contribute to this limitation.
- Improvements in these areas could expedite ventilator weaning processes.
Background:
Organizational processes affect the duration of mechanical ventilation in adult and pediatric intensive care units, but surprisingly little is known about role responsibilities for mechanical ventilation and weaning and related contextual factors that may influence timely liberation from mechanical ventilation.
Objective:
To determine the professional group and seniority of clinicians responsible for key decisions regarding ventilation and weaning; use of ventilation protocols and automated closed loop systems; and provision of education on mechanical ventilation.
Methods:
Mailed survey to nurse managers of pediatric intensive care units in the United Kingdom.
Results:
Response rate was 61%. In most units, nurse managers reported that physicians and nurses usually collaborated in making decisions about initializing (63%) and adjusting (94%) ventilator settings and for determining weaning readiness (88%), weaning method (59%), extubation readiness (82%), and weaning failure (100%). Protocols for mechanical ventilation were available in 35% of units, some specific to weaning (18%) and others for noninvasive ventilation (35%). Automated closed loop systems were used in 18% of units. Competency training was required before nurses could adjust ventilator settings in 35% of responding units; in the remaining units, settings were adjusted by nurses who had no specific competency training.
Conclusions:
Key decisions were mainly collaborative, but nurses were limited in their ability to adjust ventilator settings independently. This limitation may be due to a lack of standardized competency programs and the infrequent use of non-physician-led weaning protocols and automated systems. These findings indicate some ways of improving processes to avoid delays in ventilator weaning.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...