Related Experiment Video
Updated: May 11, 2026


Voltage-Dependent Potassium Current Recording on H9c2 Cardiomyocytes via the Whole-Cell Patch-Clamp Technique
Published on: November 11, 2022
Propafenone blocks human cardiac Kir2.x channels by decreasing the negative electrostatic charge in the cytoplasmic
Irene Amorós1, Pablo Dolz-Gaitón, Ricardo Gómez
1Department of Pharmacology, School of Medicine, Universidad Complutense, 28040 Madrid, Spain.

Abstract:
Human cardiac inward rectifier current (IK1) is generated by Kir2.x channels. Inhibition of IK1 could offer a useful antiarrhythmic strategy against fibrillatory arrhythmias. Therefore, elucidation of Kir2.x channels pharmacology, which still remains elusive, is mandatory. We characterized the electrophysiological and molecular basis of the inhibition produced by the antiarrhythmic propafenone of the current generated by Kir2.x channels (IKir2.x) and the IK1 recorded in human atrial myocytes. Wild type and mutated human Kir2.x channels were transiently transfected in CHO and HEK-293 cells. Macroscopic and single-channel currents were recorded using the patch-clamp technique. At concentrations >1μM propafenone inhibited IKir2.x the order of potency being Kir2.3∼IK1>Kir2.2>Kir2.1 channels. Blockade was irrespective of the extracellular K(+) concentration whereas markedly increased when the intracellular K(+) concentration was decreased. Propafenone decreased inward rectification since at potentials positive to the K(+) equilibrium potential propafenone-induced block decreased in a voltage-dependent manner. Importantly, propafenone favored the occurrence of subconductance levels in Kir2.x channels and decreased phosphatidylinositol 4,5-bisphosphate (PIP2)-channel affinity. Blind docking and site-directed mutagenesis experiments demonstrated that propafenone bound Kir2.x channels at the cytoplasmic domain, close to, but not in the pore itself, the binding site involving two conserved Arg residues (residues 228 and 260 in Kir2.1). Our results suggested that propafenone incorporated into the cytoplasmic domain of the channel in such a way that it decreased the net negative charge sensed by K(+) ions and polyamines which, in turn, promotes the appearance of subconductance levels and the decrease of PIP2 affinity of the channels.
Insights
The antiarrhythmic drug propafenone inhibits human cardiac inward rectifier current (IK1) by binding to Kir2.x channels. This action, particularly on Kir2.3 and IK1, offers potential for treating arrhythmias.
Area of Science:
- Cardiovascular Physiology
- Molecular Pharmacology
- Ion Channel Biophysics
Background:
- Human cardiac inward rectifier current (IK1) is crucial for cardiac electrical stability.
- Kir2.x channels generate IK1, and their pharmacology is not fully understood.
- Inhibiting IK1 is a potential antiarrhythmic strategy for fibrillatory arrhythmias.
Purpose of the Study:
- To characterize the electrophysiological and molecular mechanisms of propafenone's inhibition of Kir2.x channels and IK1.
- To determine the potency and specificity of propafenone against different Kir2.x subtypes.
- To elucidate the binding site and mode of action of propafenone on Kir2.x channels.
Main Methods:
- Transient transfection of wild-type and mutated human Kir2.x channels in CHO and HEK-293 cells.
- Macroscopic and single-channel current recordings using the patch-clamp technique.
- Blind docking and site-directed mutagenesis to identify propafenone's binding site.
Main Results:
- Propafenone inhibited IKir2.x and IK1 at concentrations >1μM, with potency order Kir2.3∼IK1>Kir2.2>Kir2.1.
- Blockade was independent of extracellular K+ but increased with decreased intracellular K+.
- Propafenone decreased inward rectification, favored subconductance levels, and reduced PIP2-channel affinity.
- Propafenone binds to the cytoplasmic domain of Kir2.x channels, involving Arg228 and Arg260 (Kir2.1).
Conclusions:
- Propafenone acts as a potent inhibitor of human cardiac IK1 via Kir2.x channels.
- The drug binds to the cytoplasmic domain, modulating channel gating and PIP2 interaction.
- These findings provide a molecular basis for propafenone's antiarrhythmic potential against specific arrhythmias.
Related Concept Videos
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:21
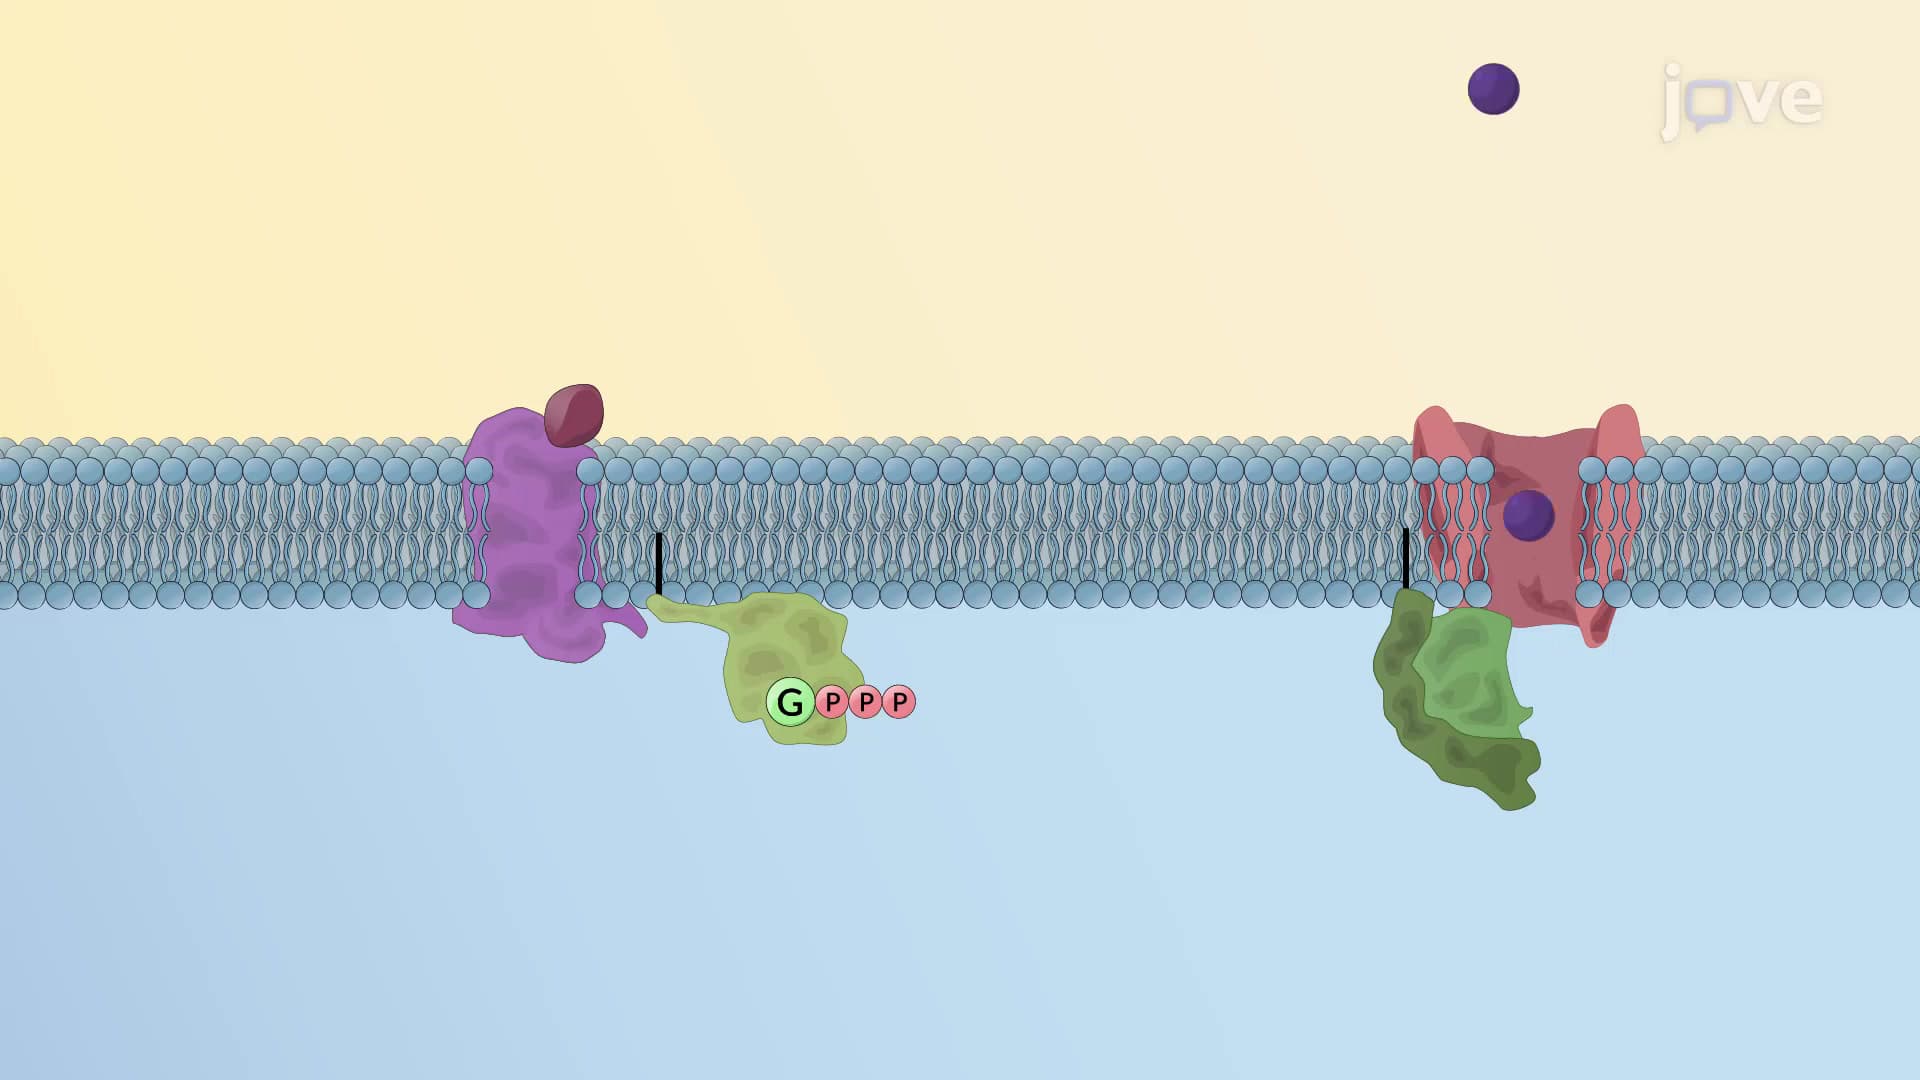
G-Protein Gated Ion Channels
Sensory organs,...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:28
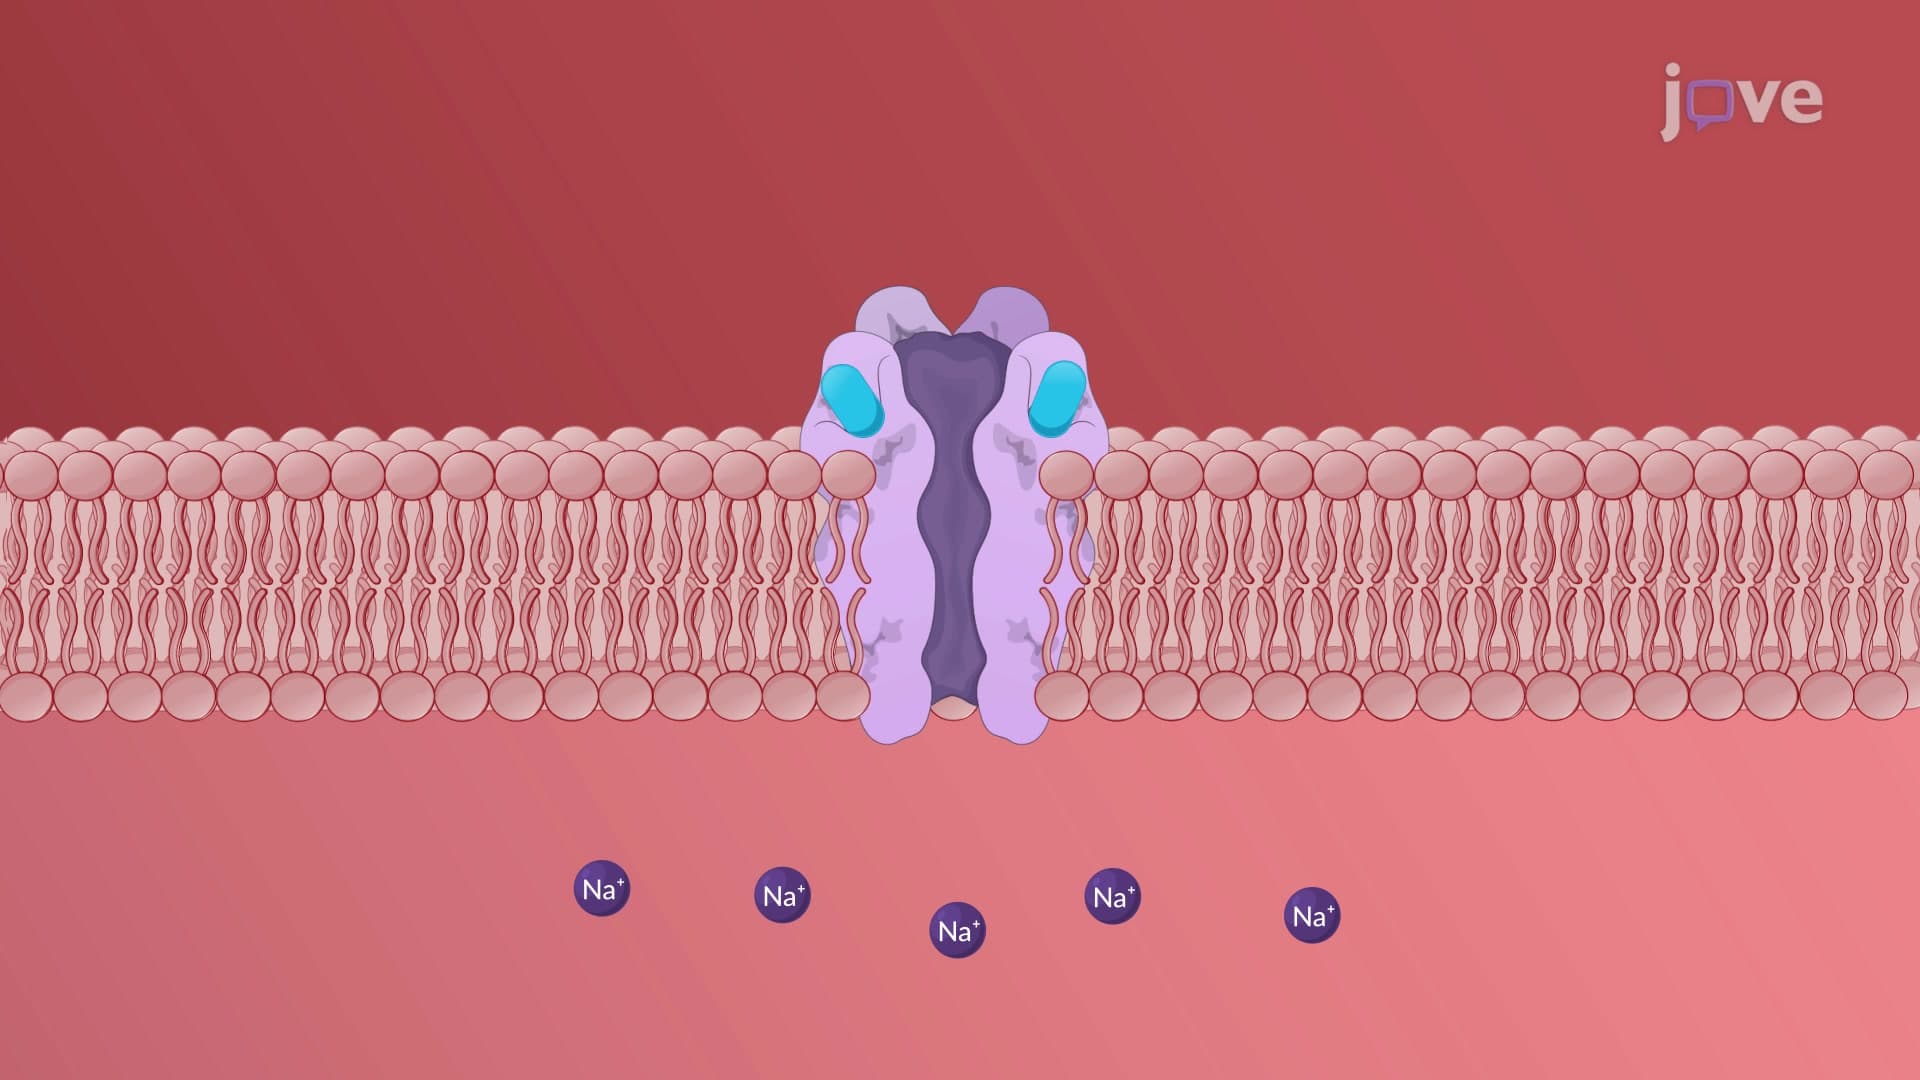
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...