Related Experiment Video
Updated: May 11, 2026


Iterative Development of an Innovative Smartphone-Based Dietary Assessment Tool: Traqq
Published on: March 19, 2021
Adapting the SLIM diabetes prevention intervention to a Dutch real-life setting: joint decision making by science and
Sophia C Jansen1, Annemien Haveman-Nies, Geerke Duijzer
1Community Health Service GGD Gelre-IJssel; Academic Collaborative Centre AGORA, GGD Gelre-IJssel, PO Box 51, 7300, AB, Apeldoorn, The Netherlands. s.jansen@ggdgelre-ijssel.nl

Background:
Although many evidence-based diabetes prevention interventions exist, they are not easily applicable in real-life settings. Moreover, there is a lack of examples which describe the adaptation process of these interventions to practice. In this paper we present an example of such an adaptation. We adapted the SLIM (Study on Lifestyle intervention and Impaired glucose tolerance Maastricht) diabetes prevention intervention to a Dutch real-life setting, in a joint decision making process of intervention developers and local health care professionals.
Methods:
We used 3 adaptation steps in accordance with current adaptation frameworks. In the first step, the elements of the SLIM intervention were identified. In the second step, these elements were judged for their applicability in a real-life setting. In the third step, adaptations were proposed and discussed for those elements which were deemed not applicable. Participants invited for this process included intervention developers and local health care professionals (n=19).
Results:
In the first adaptation step, a total of 22 intervention elements were identified. In the second step, 12 of these 22 intervention elements were judged as inapplicable. In the third step, a consensus was achieved for the adaptations of all 12 elements. The adapted elements were in the following categories: target population, techniques, intensity, delivery mode, materials, organisational structure, and political and financial conditions. The adaptations either lay in changing the SLIM protocol (6 elements) or the real-life working procedures (1 element), or a combination of both (4 elements).
Conclusions:
The positive result of this study is that a consensus was achieved within a relatively short time period (nine months) between the developers of the SLIM intervention and local health care professionals on the adaptations needed to make SLIM applicable in a Dutch real-life setting. Our example shows that it is possible to combine the perspectives of scientists and practitioners, and to find a balance between evidence-base and applicability concerns.
Related Concept Videos
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:18
Models of Health Promotion and Illness Prevention II
The agent-host-environment model states that disease results from...
 01:25
Models of Health Promotion and Illness Prevention I
The health belief model (HBM) attempts to predict health-related behavior in specific belief patterns. According to the HBM, a person's...
 01:30
Stress Prevention and Stress Management Techniques VI
Motivation and Self-Determination
Motivation, the driving force behind behavior, plays a pivotal role at every stage of the change process. The research...
 01:26
Type II Diabetes I: Introduction
 01:09
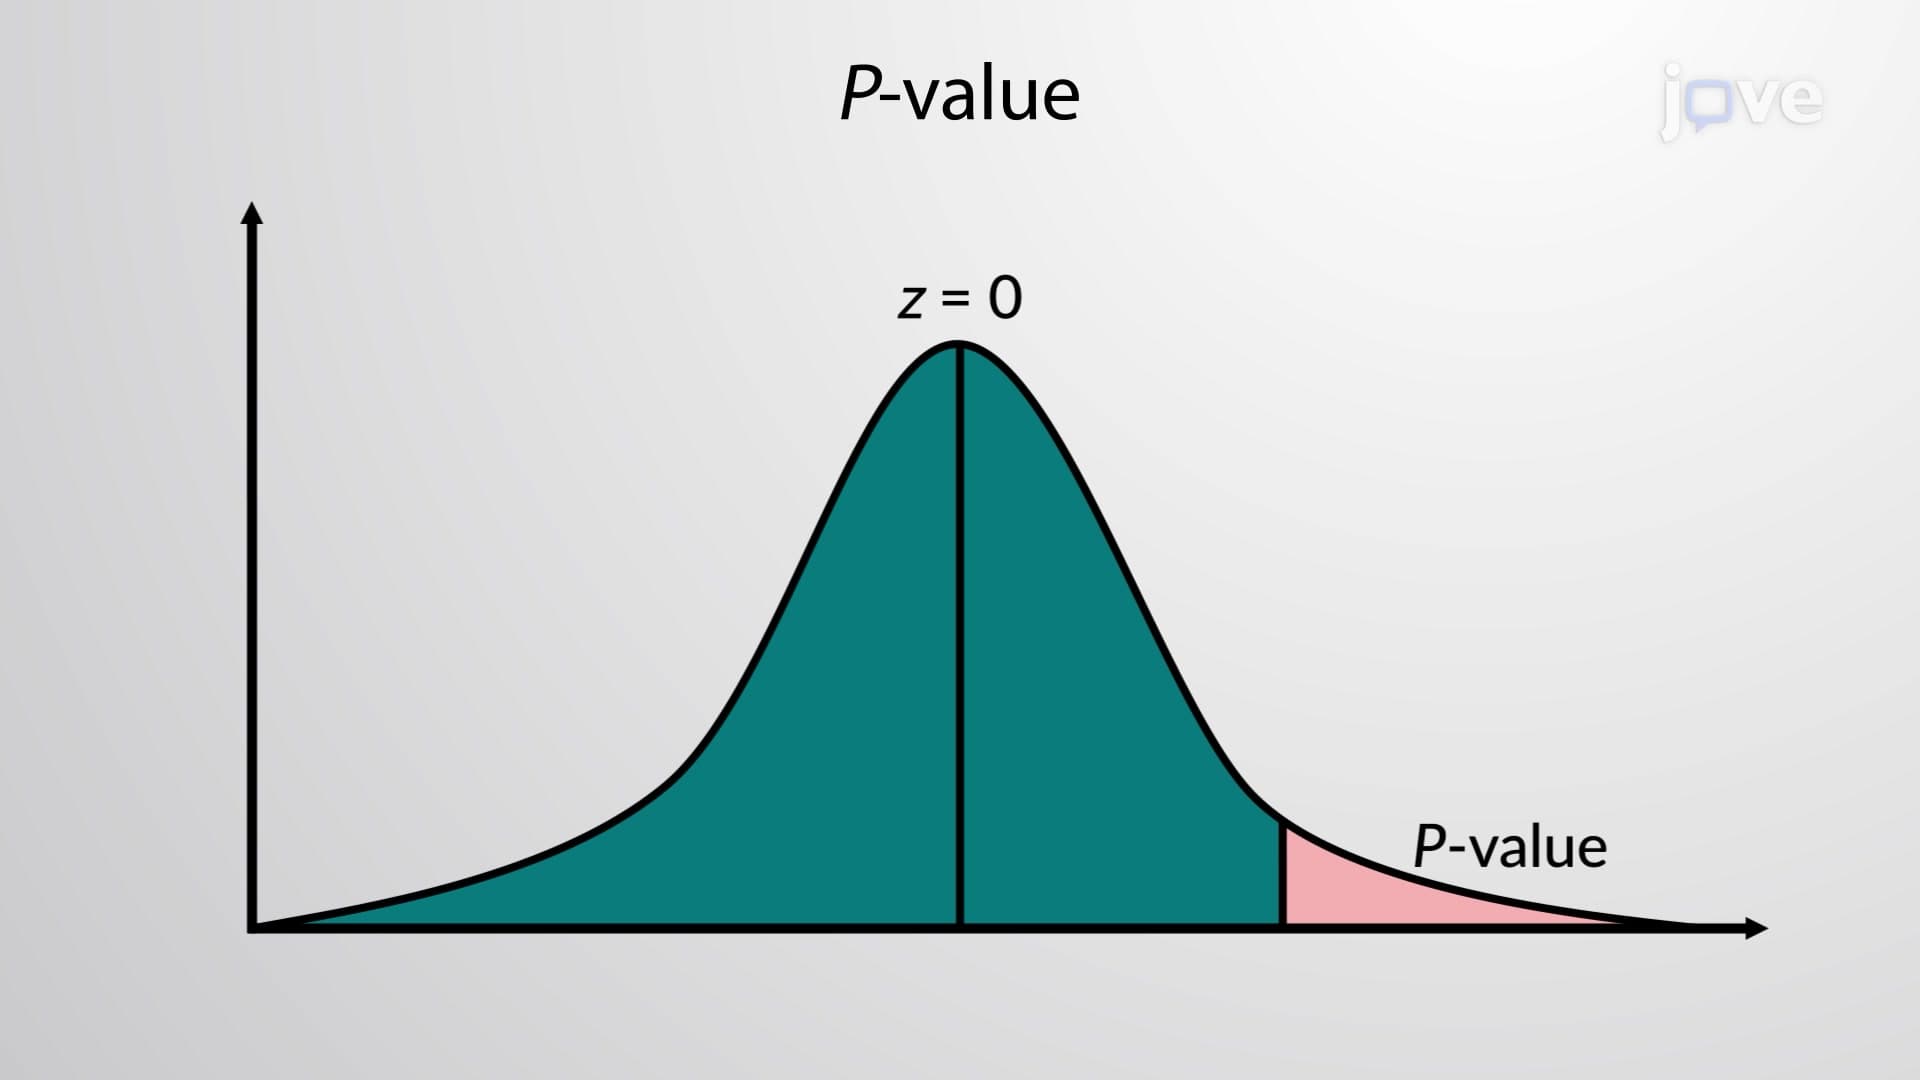
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can have a...