Related Experiment Video
Updated: May 11, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
In lung cancer patients where a malignant pleural effusion is found at operation could resection ever still be
Alfonso Fiorelli1, Mario Santini
1Thoracic Surgery Unit, Second University of Naples, Naples, Italy.

Abstract:
A best evidence topic in thoracic surgery was written according to a structured protocol. The question addressed was whether surgery could ever be justified in non-small cell lung cancer patients with an unexpected malignant pleural effusion at surgery. Eight papers were chosen to answer the question. The authors, journal, date and country of publication, patient group studied, study type, relevant outcomes and results of these papers were tabulated. Study limitations included a lack of retrospective studies, the heterogeneous patient population and various treatments applied. Three papers found that surgery--compared to exploratory thoracotomy--was associated with a survival advantage in cases of minimal pleural disease. One paper showed that the median survival time of 58.8 months in patients with pleural effusion was better than that of patients with more extensive pleural dissemination as pleural nodule (10 months; P=0.0001) or pleural nodule with effusion (19.3 months; P=0.019). Another study showed that pleural effusion patients with N0-1 status had a median survival time more than 5 years longer than patients with similar or more extensive pleural dissemination but with N2-N3 status. A further study showed a better 5-year survival time in patients with pleural effusion, than in patients with pleural nodule (22.9% vs 8.9%, respectively; P=0.45). In two papers, surgery vs exploratory thoracotomy had better survival in cases of N0 status and of complete tumour resection independently of pleural dissemination. Different strategies were employed to obtain freedom from macroscopic residual tumour, including pneumonectomy, lobar resection or, to a lesser extent, pleurectomy in patients having pleural dissemination. Only one paper reported a worse median survival time after pneumonectomy than for more limited resections (12.8 vs 24.1 months, respectively; P=0.0018). In the remaining papers, no comparison between the different resections was made. In all studies except one, surgery was a component of multimodal treatment. Intrapleural chemotherapy was largely applied with systemic adjuvant chemotherapy and/or radiotherapy. The study period and/or year of publication of most papers was 10 years or more, this may explain the different chemotherapy regimens used in the various studies. No current guidelines support surgery over conservative therapy and the identified studies in this review are not strong enough to change this recommendation.
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:27
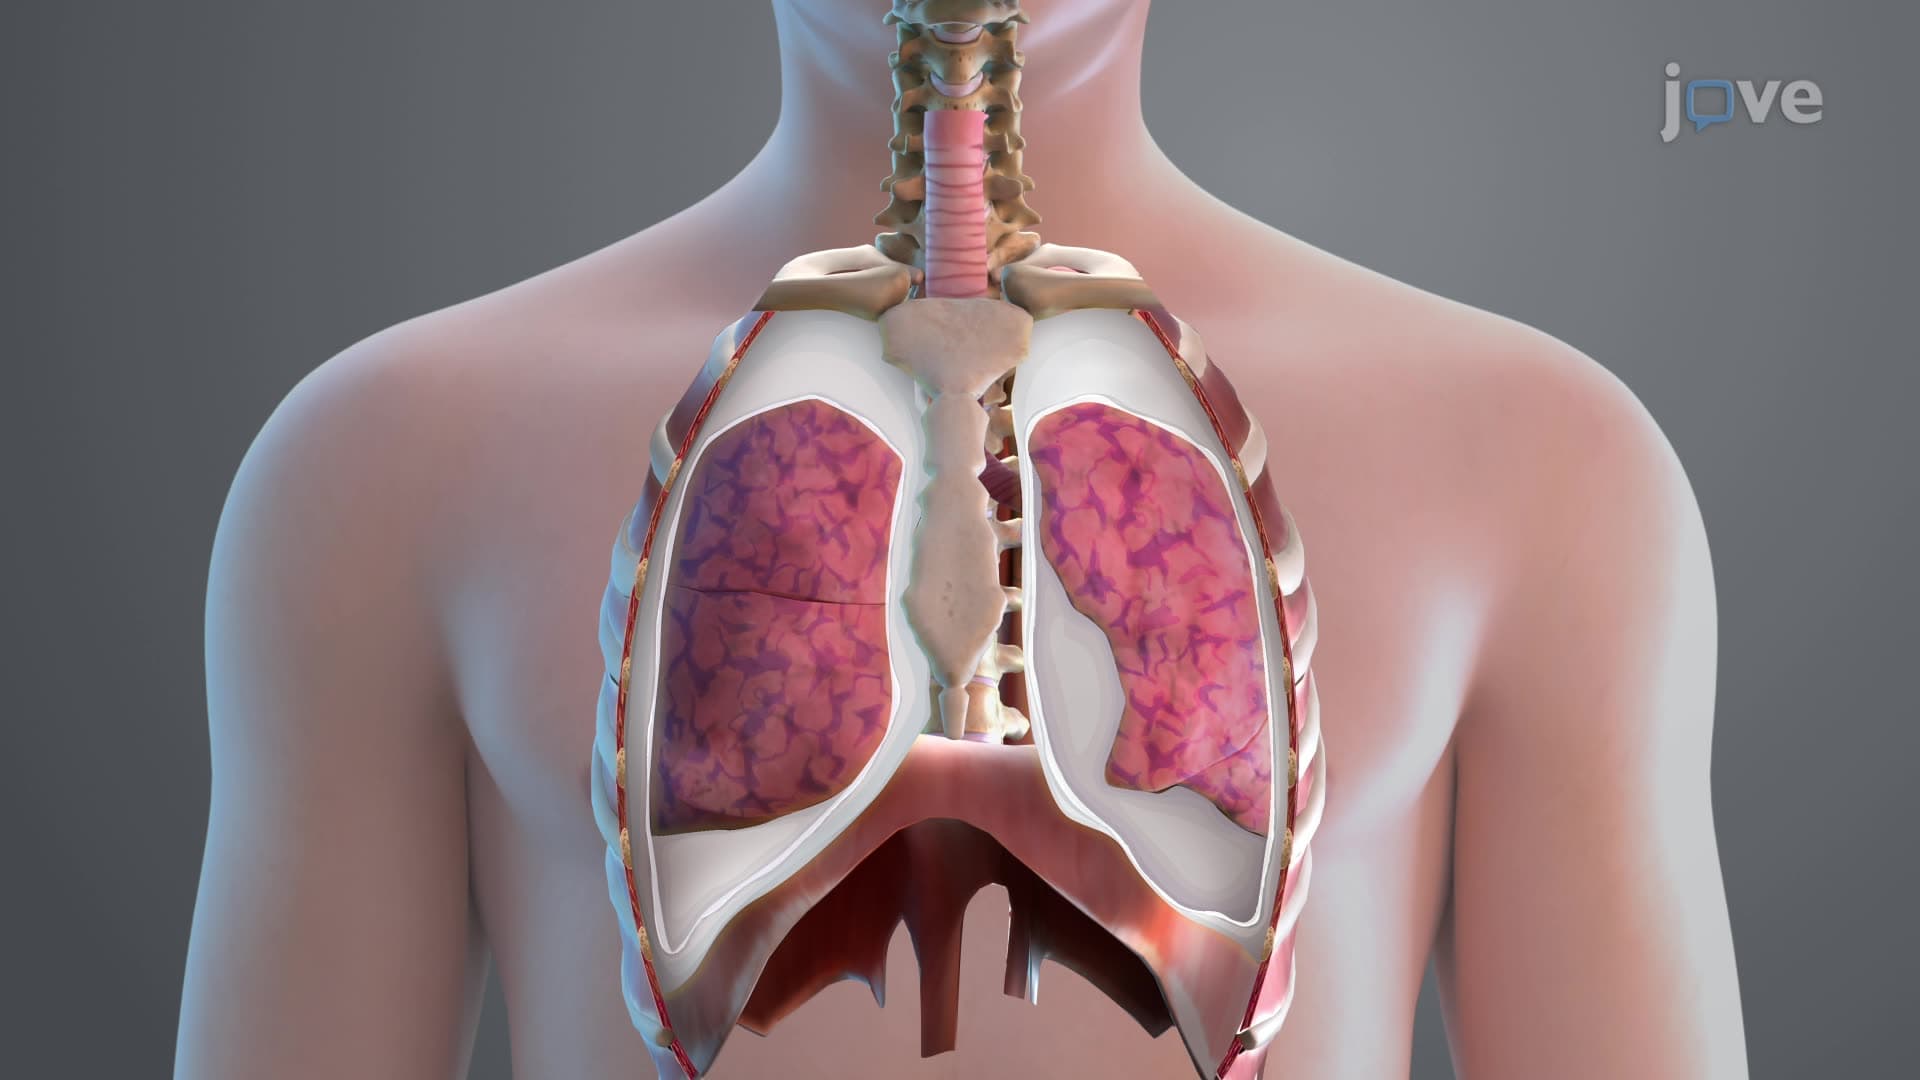
Pneumothorax-II
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...