Related Experiment Video
Updated: May 11, 2026
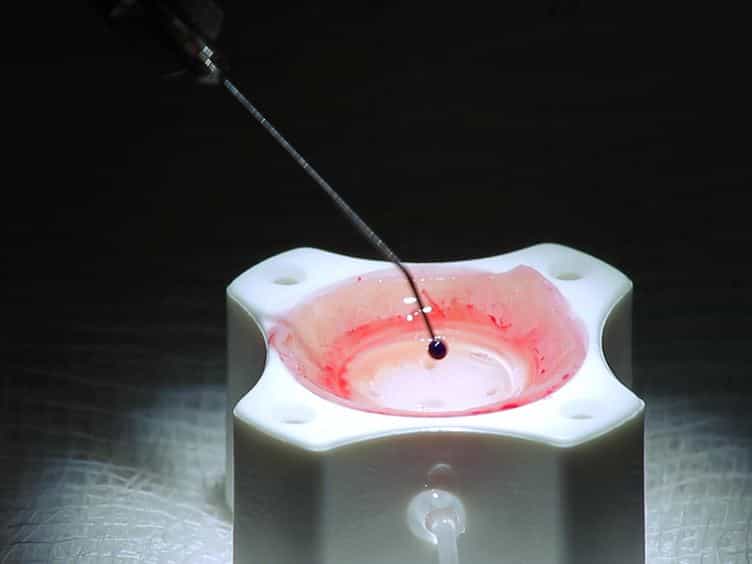

Corneal Donor Tissue Preparation for Descemet's Membrane Endothelial Keratoplasty
Published on: September 17, 2014
Descemet's membrane endothelial keratoplasty surgery: update on the evidence and hurdles to acceptance
Marianne O Price1, Francis W Price
1Cornea Research Foundation of America, Indianapolis, IN 46260, USA. mprice@cornea.org

Purpose Of Review:
Descemet's stripping endothelial keratoplasty (DSEK) is the most popular treatment for endothelial dysfunction, but Descemet's membrane endothelial keratoplasty (DMEK) now provides better vision with lower risk of immunologic rejection. Although DMEK is more challenging, advances in instrumentation and techniques are reducing the learning curve.
Recent Findings:
In contrast to DSEK, which includes posterior donor stroma, DMEK consists merely of donor endothelium and Descemet's membrane, so DMEK does not create a stromal interface and induces significantly less posterior surface aberrations, resulting in better vision. Furthermore, multiple centers report remarkably low (<1%) cumulative probability of immunologic graft rejection episodes through 2 years after DMEK. Initially, the biggest challenges were tissue loss in preparation and ensuring attachment. Subsequent improvements have reduced complication rates to levels experienced with DSEK. DMEK/DSEK hybrids and 'thin' DSEK also can provide better vision than standard DSEK; randomized controlled comparisons with DMEK are needed.
Summary:
DMEK provides an anatomically exact replacement of dysfunctional host endothelium and has set new benchmarks for rejection risk and visual outcomes following endothelial replacement. DMEK is providing new insights into how different corneal layers contribute to immunogenicity and immune tolerance and into the key factors that limit vision after endothelial keratoplasty.

