Related Experiment Video
Updated: May 11, 2026

Substernal Thyroid Biopsy Using Endobronchial Ultrasound-guided Transbronchial Needle Aspiration
Published on: November 10, 2014
Relationship between bronchial anthracofibrosis and endobronchial tuberculosis
Hyun Ji Kim1, Sang Dong Kim, Dong Woo Shin
1Department of Internal Medicine, Daegu Fatima Hospital, Daegu, Korea.

Background/Aims:
Various pulmonary diseases may be associated with bronchial anthracofibrosis (BAF). Our aim was to identify a relationship between BAF and endobronchial tuberculosis (EBTB).
Methods:
In total, 156 patients, diagnosed with EBTB using bronchoscopy, between June 1999 and May 2008, were included. Clinical and bronchoscopic findings between patients with BAF (n = 72, BAF group) and without BAF (n = 84, non-BAF) were analyzed retrospectively.
Results:
The crude odds ratio (OR) of BAF for EBTB was 8.88 (95% confidence interval, 6.37 to 12.37). On multivariate analysis, adjusting for age, history of biomass smoke exposure, and comorbidities, the most significant independent factor for EBTB was a history of biomass smoke exposure (adjusted OR, 17.471; adjusted p < 0.001). EBTB was more frequent in the right lung, particularly the right middle lobar bronchus, in the BAF group. Actively caseating, edematous-hyperemic, and ulcerative were the major types, with 77 (49%), 33 (21%), and 31 cases (20%), respectively. The BAF group had more ulcerative type, while the non-BAF group had more actively caseating type. The duration of EBTB treatment was similar between the groups. No significant difference was observed in the development of complications during treatment and posttreatment bronchostenosis between the groups.
Conclusions:
These findings suggest that BAF may be a risk factor for EBTB and affect the location and morphological type at the time of EBTB development.

Related Concept Videos
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:23
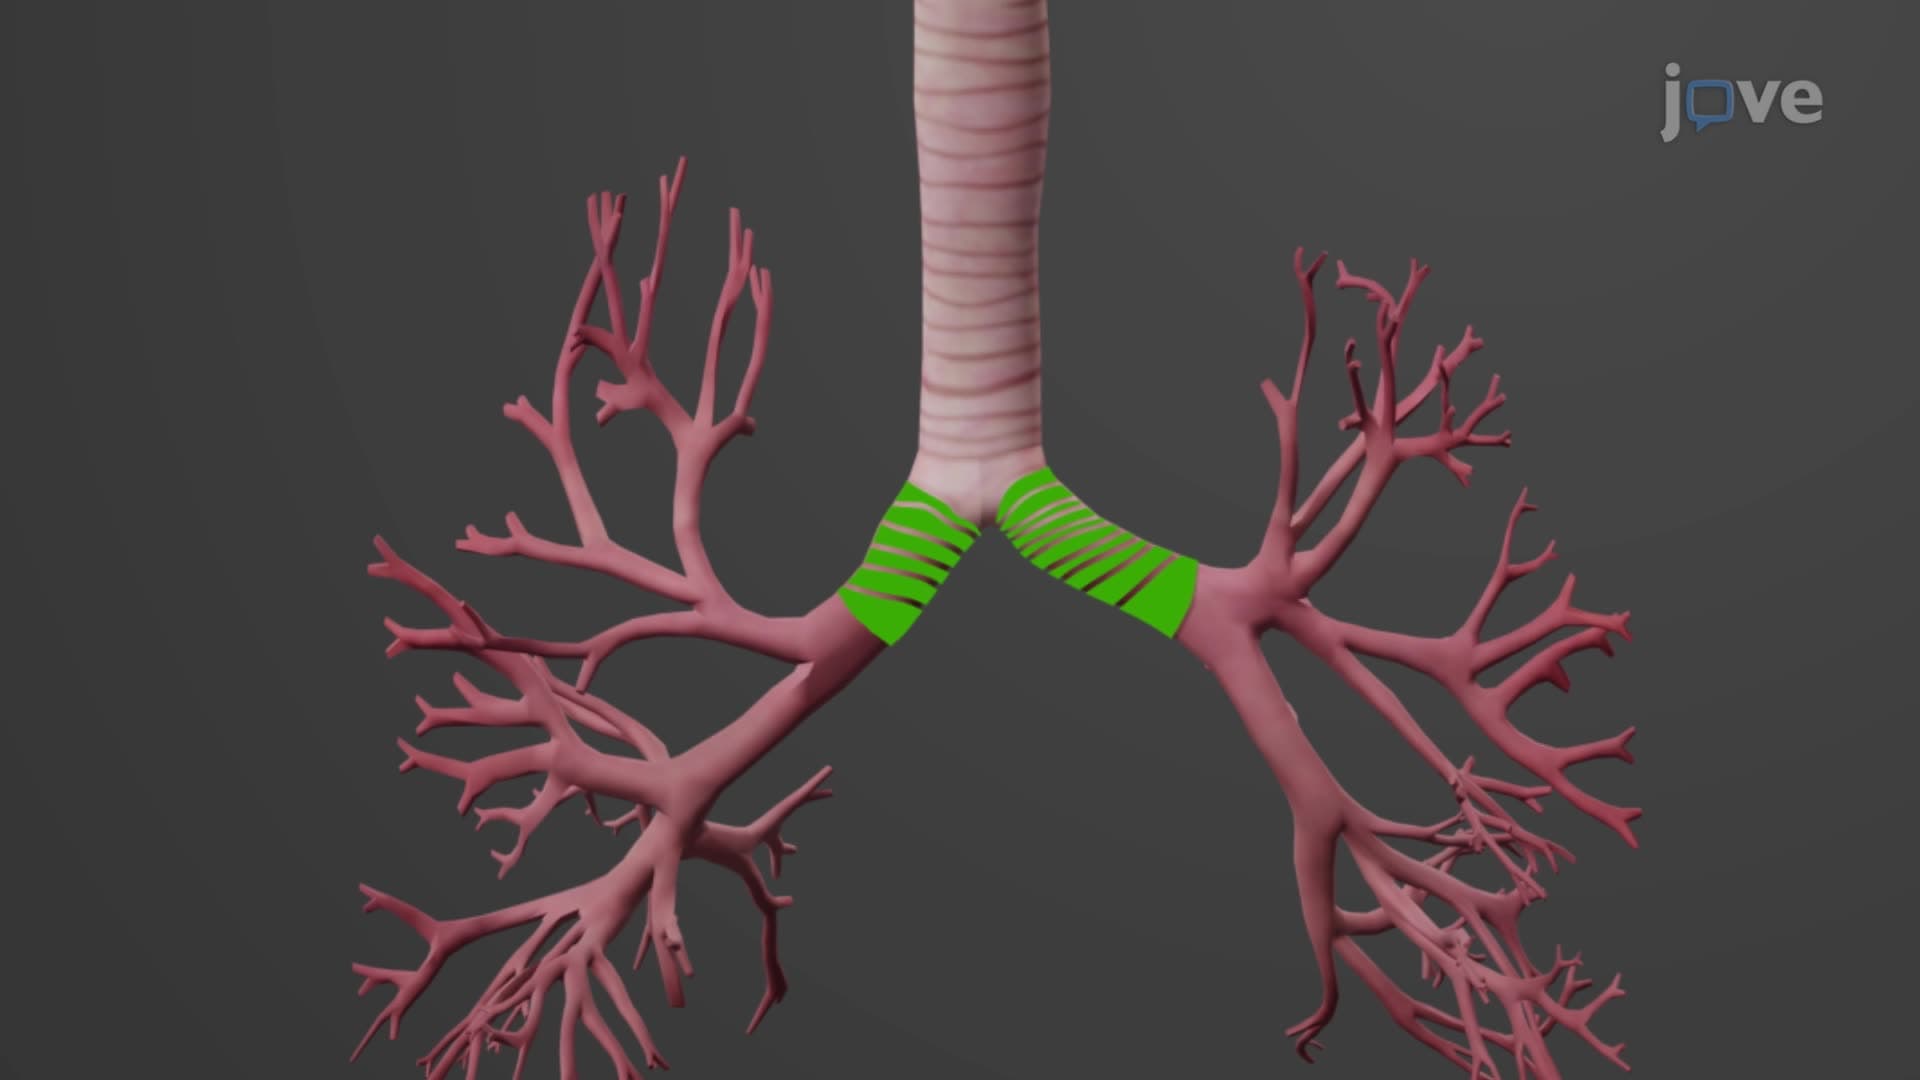
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...