Related Experiment Video
Updated: May 11, 2026
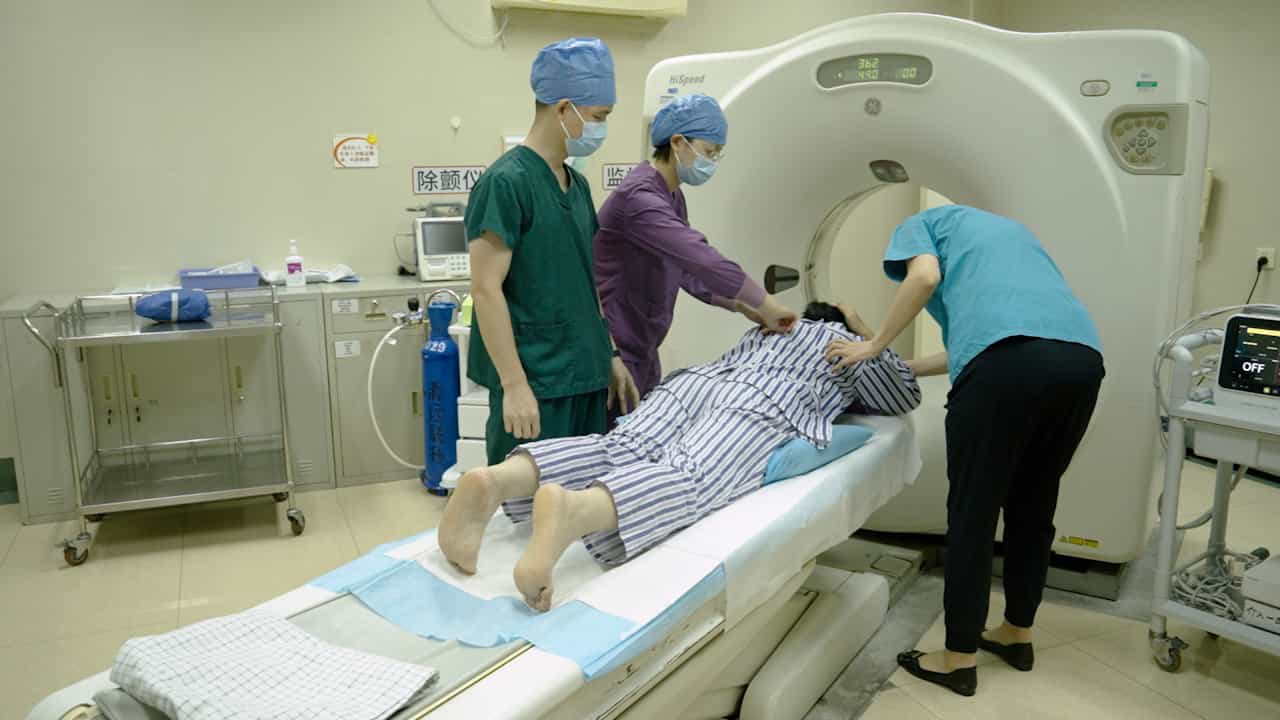
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Differences between office and 24-hour blood pressure control in hypertensive patients with CKD: A 5,693-patient
Manuel Gorostidi1, Pantelis A Sarafidis, Alejandro de la Sierra
1Department of Nephrology, Hospital Universitario Central de Asturias, Oviedo, Spain. manuel.gorostidi@sespa.princast.es

Background:
Previous studies have examined control rates of office blood pressure (BP) in chronic kidney disease (CKD). However, recent evidence suggests major discrepancies between office and 24-hour BP values in hypertensive populations. This study examined concordance/discordance between office- and ambulatory-based BP control in a large cohort of patients with CKD.
Study Design:
Cross-sectional.
Setting & Participants:
5,693 hypertensive individuals with CKD stages 1-5 from the Spanish ABPM (ambulatory BP monitoring) Registry.
Predictors:
Thresholds of 140/90 and 130/80 mm Hg for office BP and 24-hour ambulatory BP, respectively. Age, sex, body mass index, waist circumference, hypertension duration, kidney measures, diabetes, dyslipidemia, target-organ damage, and cardiovascular comorbid conditions.
Outcomes:
Misclassification of BP control as "white-coat" hypertension (office BP ≥140/90 mm Hg, 24-hour BP <130/80 mm Hg) or masked hypertension (office BP <140/90 mm Hg, 24-hour BP ≥130/80 mm Hg).
Measurements:
Standardized office-based BP and 24-hour ABPM.
Results:
Mean age was 61.0 ± 13.9 (SD) years and 52.6% were men. The proportion with white-coat hypertension was 28.8% (36.8% of patients with office BP ≥140/90 mm Hg) and that of masked hypertension was 7.0% (but 32.1% of patients with office BP <140/90 mm Hg). Female sex, aging, obesity, and target-organ damage were associated with white-coat hypertension; aging and obesity were associated with masked hypertension. Only 21.7% and 8.1% of the CKD population had office BP <140/90 and <130/80 mm Hg, respectively. In contrast, 43.5% of individuals had average 24-hour BP <130/80 mm Hg.
Limitations:
Cross-sectional design, longitudinal associations cannot be established.
Conclusions:
Misclassification of BP control at the office was observed in 1 of 3 hypertensive patients with CKD. Ambulatory-based control rates were far better than office-based rates. Nevertheless, the burden of uncontrolled ambulatory BP and misclassification of BP control at the office constitutes a call for wider use of ABPM to evaluate the success of hypertension treatment in patients with CKD.
Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:30
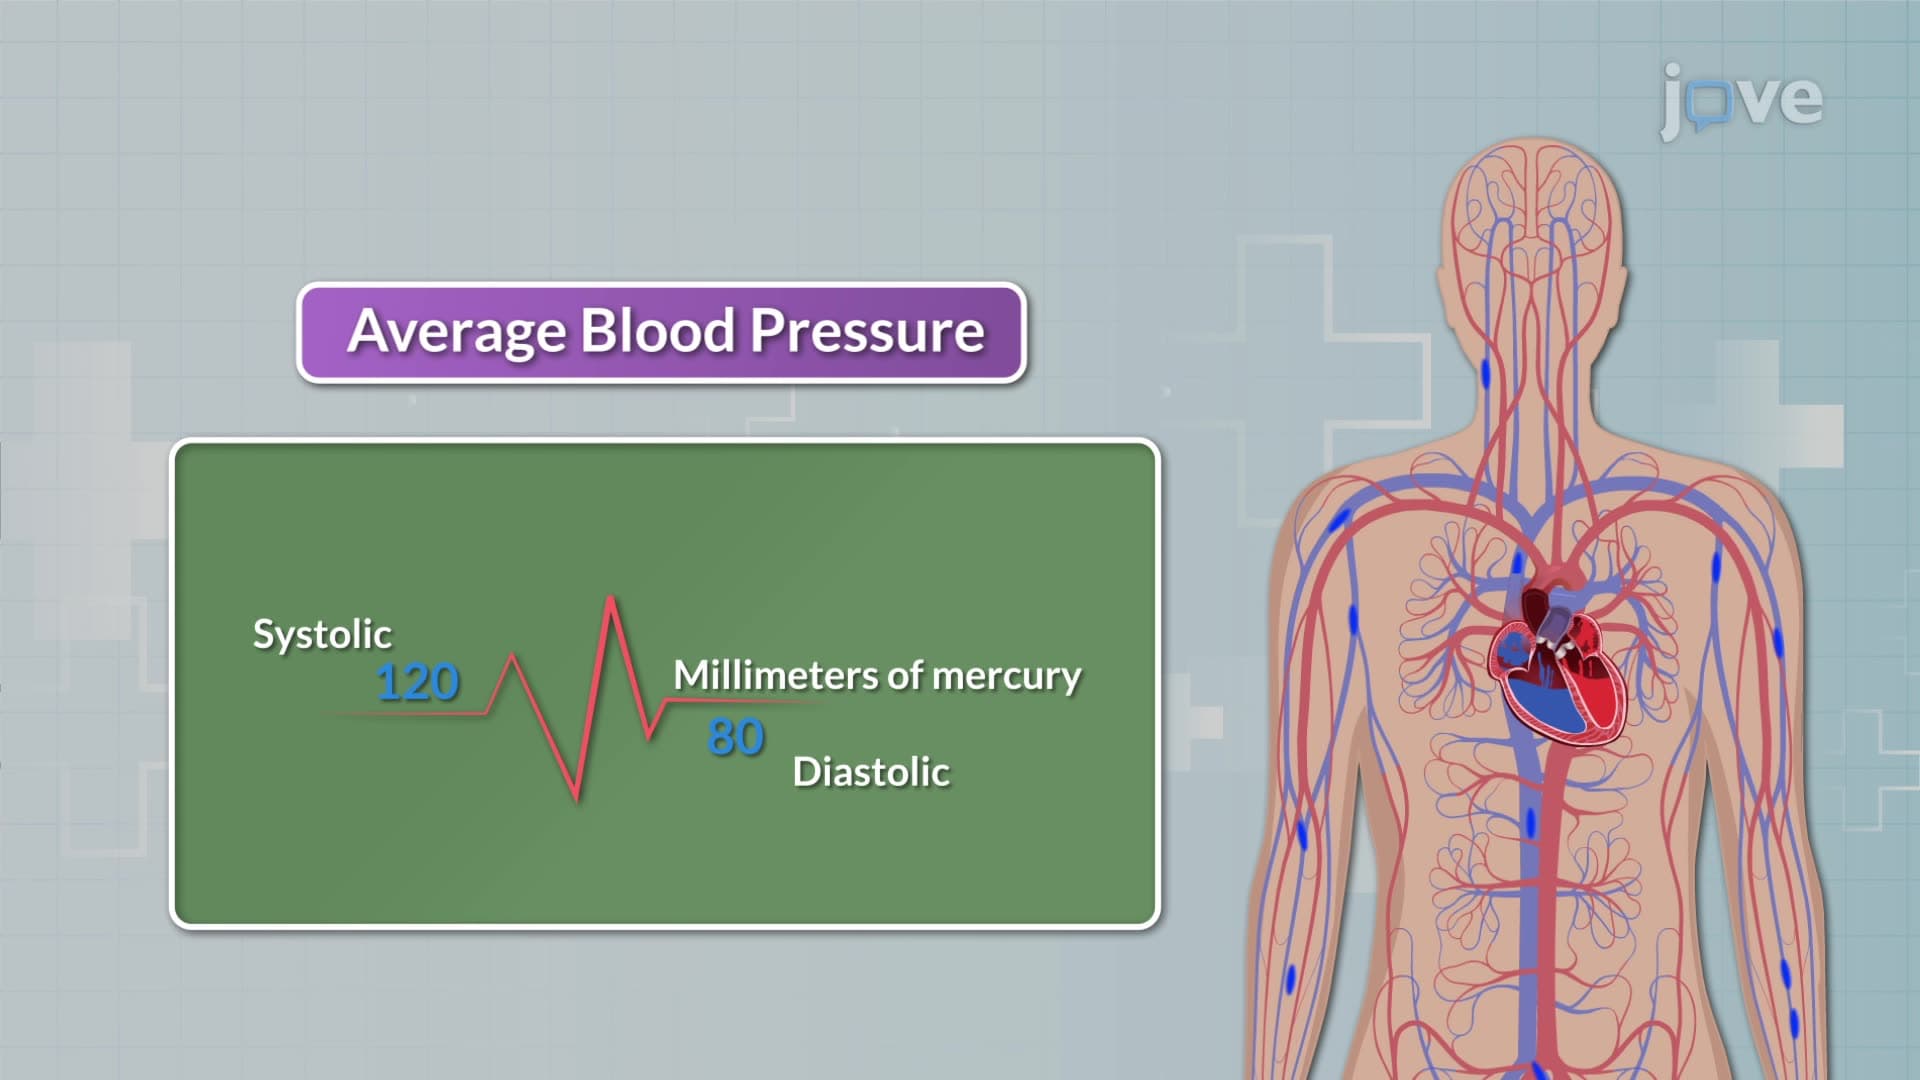
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...