Related Experiment Video
Updated: May 11, 2026
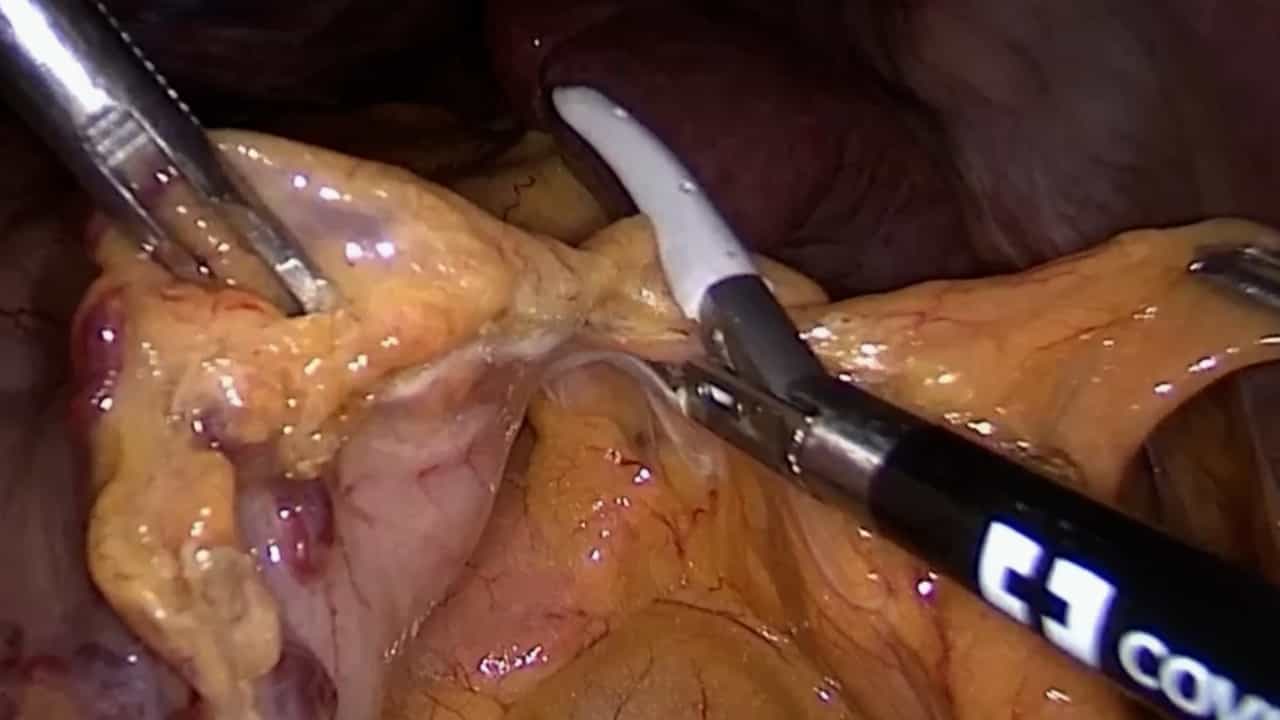
Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Consensus strategies for the nonoperative management of patients with blunt splenic injury: a Delphi study
Dominique C Olthof1, Cornelis H van der Vlies, Cornelius H van der Vlies
1Trauma Unit, Academic Medical Center, Amsterdam, The Netherlands.

Background:
Nonoperative management is the standard of care in hemodynamically stable patients with blunt splenic injury. However, a number of issues regarding the management of these patients are still unresolved. The aim of this study was to reach consensus among experts concerning optimal treatment and follow-up strategies.
Methods:
The Delphi method was used to reach consensus among 30 expert trauma surgeons and interventional radiologists from around the world. An online survey was used in the two study rounds. Consensus was defined as an agreement of 80% or greater.
Results:
Response rates of the first and second rounds were 90% and 80%, respectively. Consensus was reached for 43% of the (sub)questions. The American Association for the Surgery of Trauma organ injury scale for grading splenic injury is used by 93% of the experts. In hemodynamically stable patients, observation or splenic artery embolization (SAE) can be applied in the presence of a small or no hemoperitoneum combined with an intraparenchymal contrast extravasation or no contrast extravasation, regardless of the presence of an arteriovenous (AV) fistula/pseudoaneurysm. Hemodynamic instability is an indication for operative management, irrespective of computed tomographic characteristics and grade of splenic injury (≥82% of the experts). Operative management is also indicated in the presence of associated intra-abdominal injuries and/or the need for five or more packed red blood cell transfusions (22 of 27 experts, 82%). Recommended time span to start SAE in a stable patient with an intraparenchymal contrast extravasation is 60 minutes (19 of 24 experts). Patients should be admitted 1 to 3 days to a monitored setting (27 of 27 experts, 100%). Serial hemoglobin checks are performed by all experts, every 4 to 6 hours in the first 24 hours and once or twice a day after that (21 of 24 experts, 88%), in nonoperative management as well as after SAE. Routine postdischarge imaging is not indicated (21 of 24 experts, 88%).
Conclusion:
Although treatment should always be adjusted to the specific patient, the results of this study may serve as general guidelines.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...