Lateral meningocele syndrome: additional report and further evidence supporting a connective tissue basis

Daniela Alves1, Mafalda Sampaio, Rita Figueiredo

  • 1Department of Pediatrics, Centro Hospitalar de S. João, Porto, Portugal. desafiart@gmail.com

Related Concept Videos

Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology
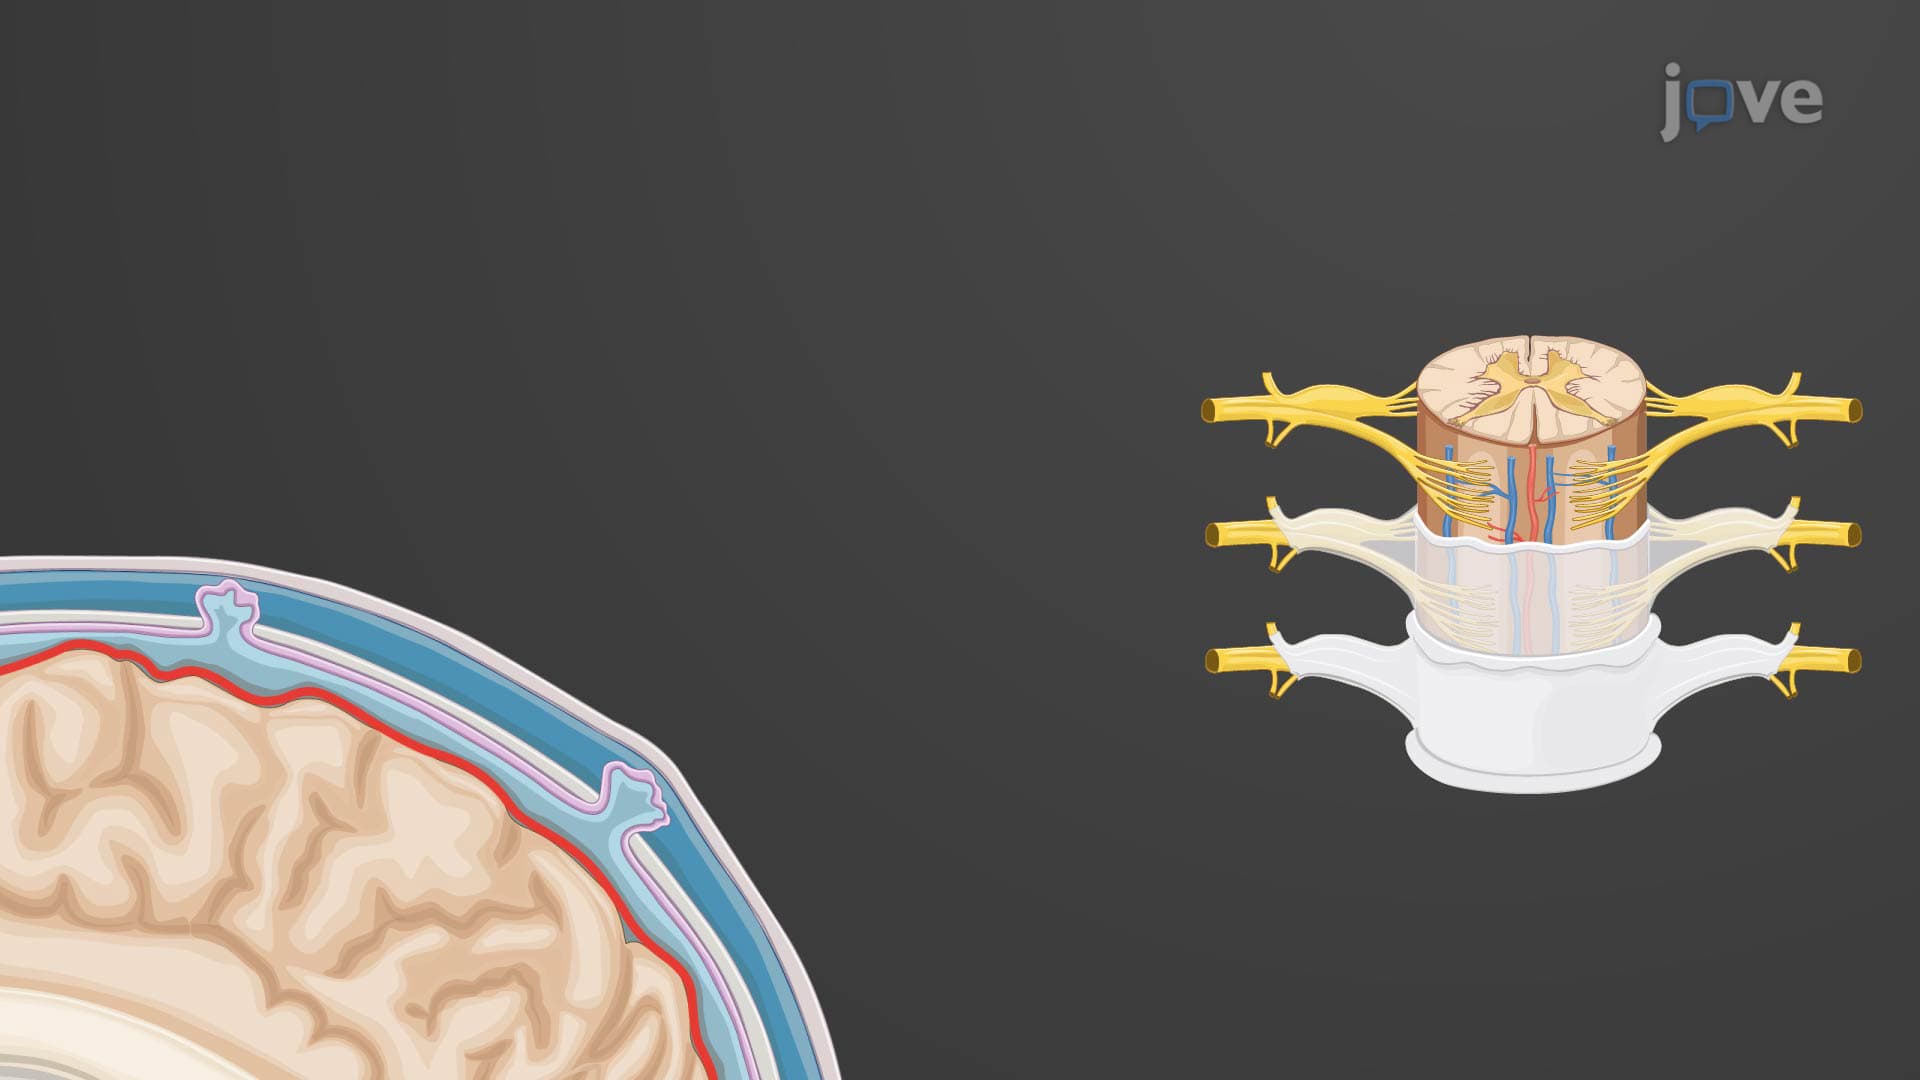
Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...
Cranial and Spinal Meninges01:19

Cranial and Spinal Meninges

The cranial and spinal meninges are complex protective structures surrounding the central nervous system (CNS), consisting of the brain and spinal cord. These meninges consist of the dura mater, the arachnoid mater, and the pia mater. They protect the CNS, provide structural support, and aid in circulating cerebrospinal fluid (CSF).
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...

Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Bacterial Meningitis II: Pathophysiology01:26

Bacterial Meningitis II: Pathophysiology

Bacterial meningitis typically begins when pathogens such as Neisseria meningitidis and Streptococcus pneumoniae colonize the nasopharynx and invade the bloodstream. This process is facilitated by bacterial virulence factors, such as polysaccharide capsules, which resist phagocytosis and complement-mediated killing. Less commonly, bacteria reach the central nervous system via contiguous spread from infections like otitis media or sinusitis, through congenital or acquired dural defects, or...
Aneurysm II: Clinical Manifestations and Diagnostic Studies01:21

Aneurysm II: Clinical Manifestations and Diagnostic Studies
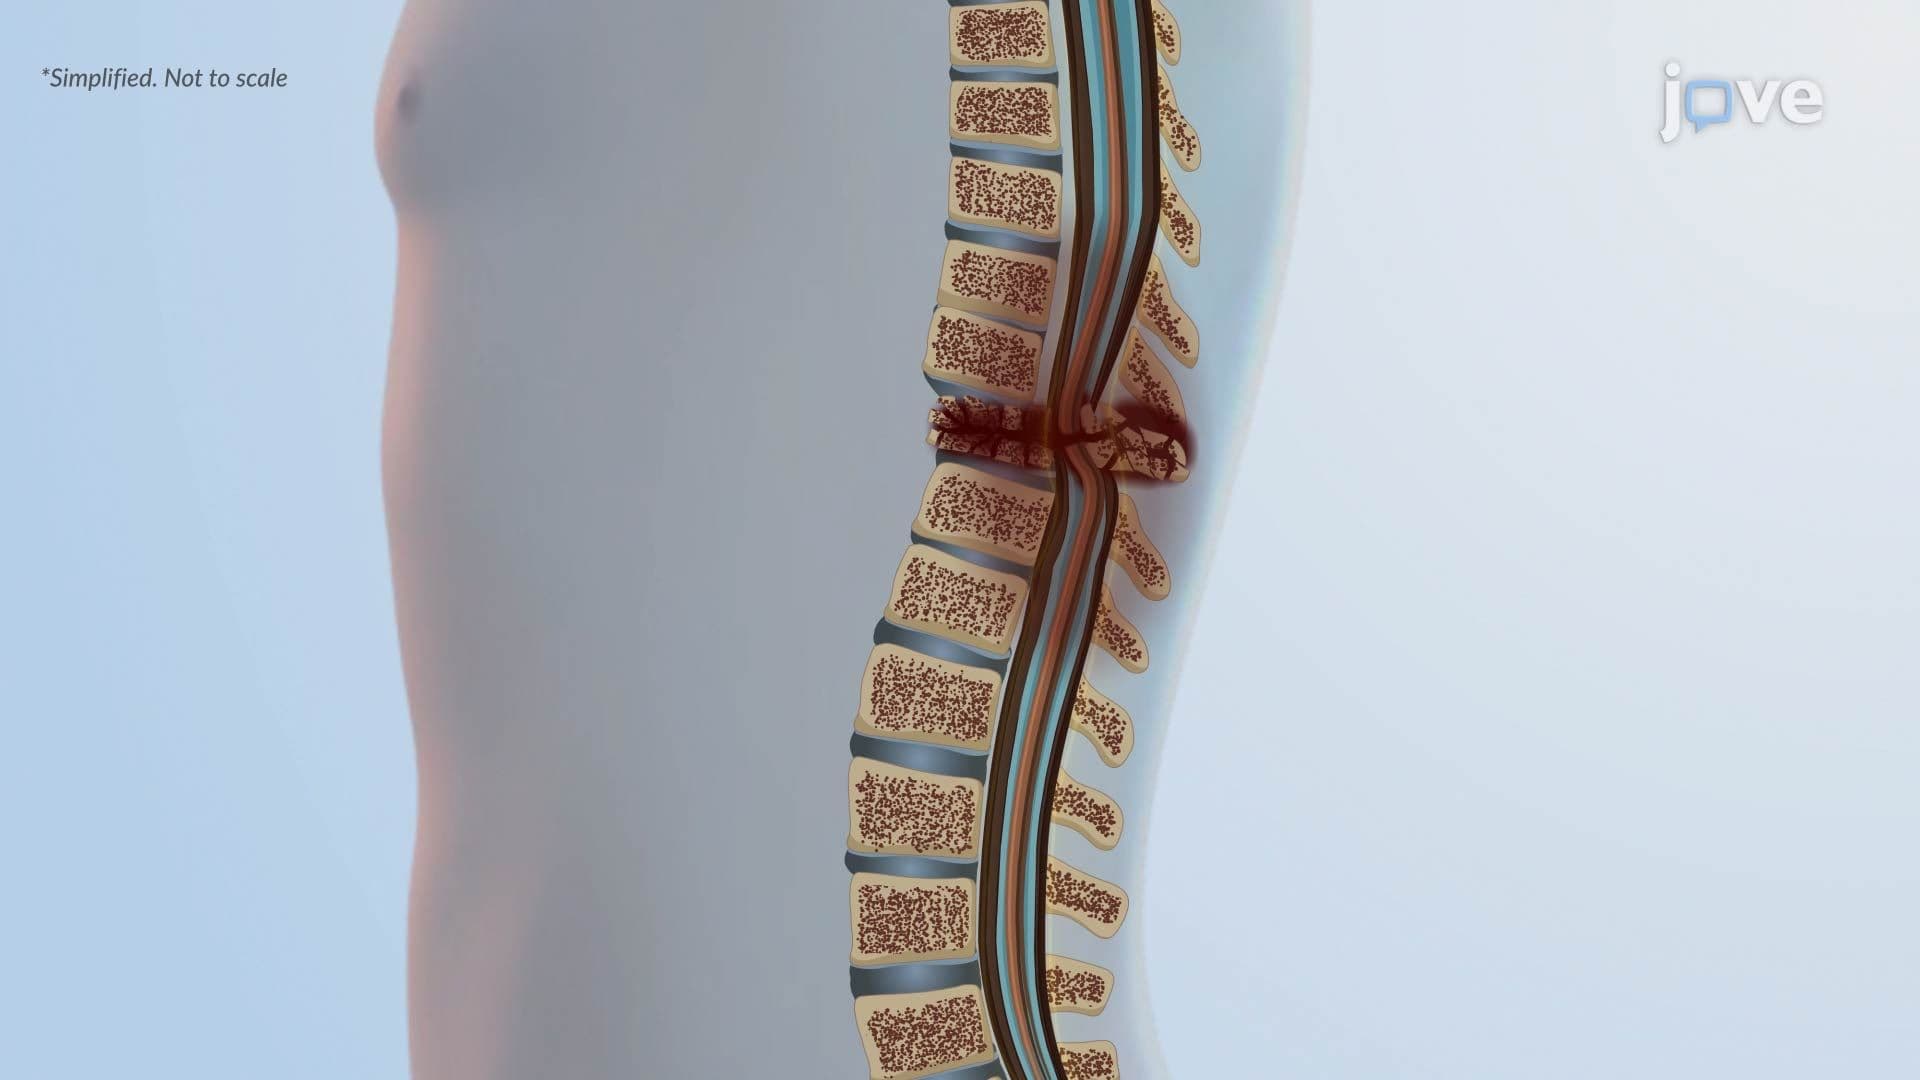
Thoracic, aortic arch and abdominal aneurysms are significant vascular conditions that can present with various clinical manifestations and lead to serious complications. Understanding these manifestations and the appropriate diagnostic studies is essential for effective management and treatment.Thoracic Aortic AneurysmsThoracic aortic aneurysms often remain asymptomatic until they reach a size that impinges on adjacent structures. They typically cause deep, diffuse chest pain that radiates to...
Spinal Cord Injury ll: Pathophysiology01:14

Spinal Cord Injury ll: Pathophysiology

Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...



