Related Experiment Video
Updated: May 11, 2026

10:05

Testing the Efficacy of Pharmacological Agents in a Pericardial Target Delivery Model in the Swine
Published on: July 7, 2016
Transient localized sweating in a horse after administration of procaine penicillin
Valerie Moorman1, Allison J Stewart, Ram C Purohit
1Colrado State University, USA.
Compendium (Yardley, PA)
|May 28, 2013

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:30
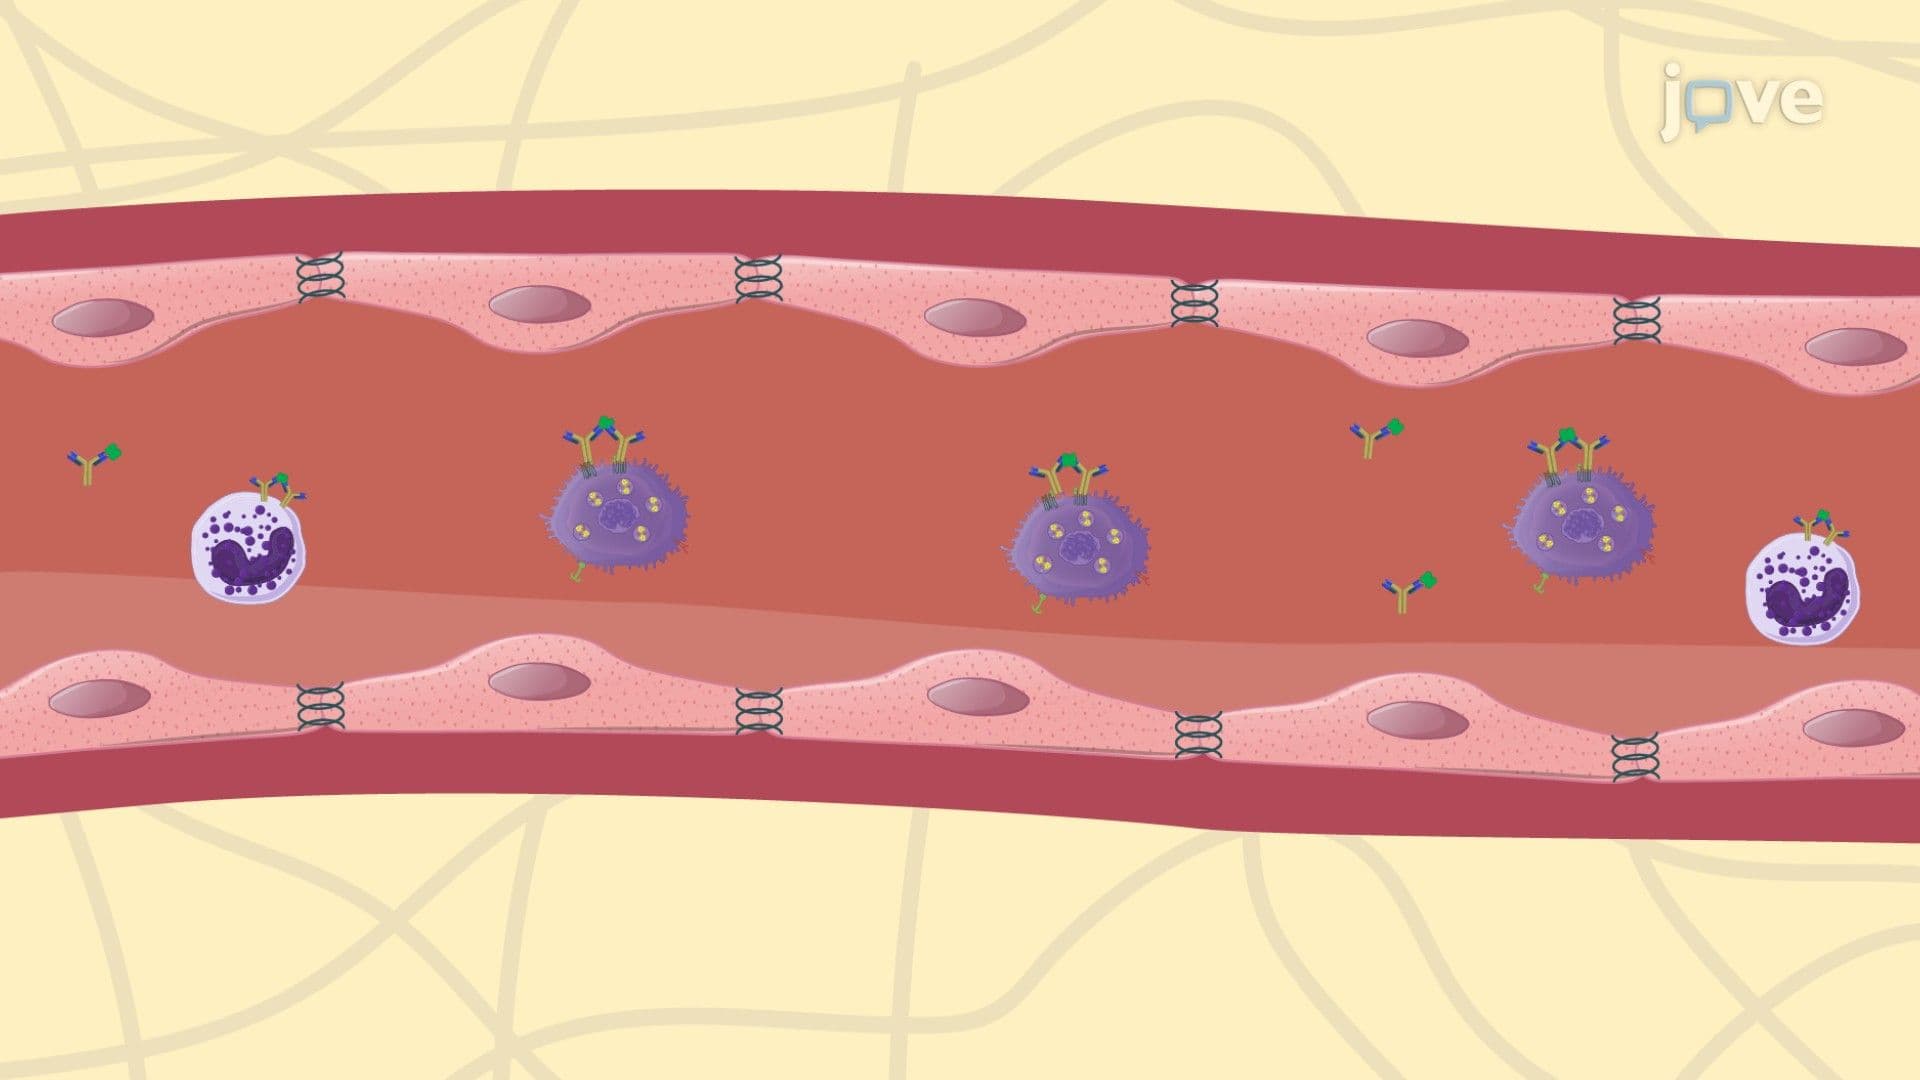
Drug Toxicity: Allergic Reactions
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
 01:19
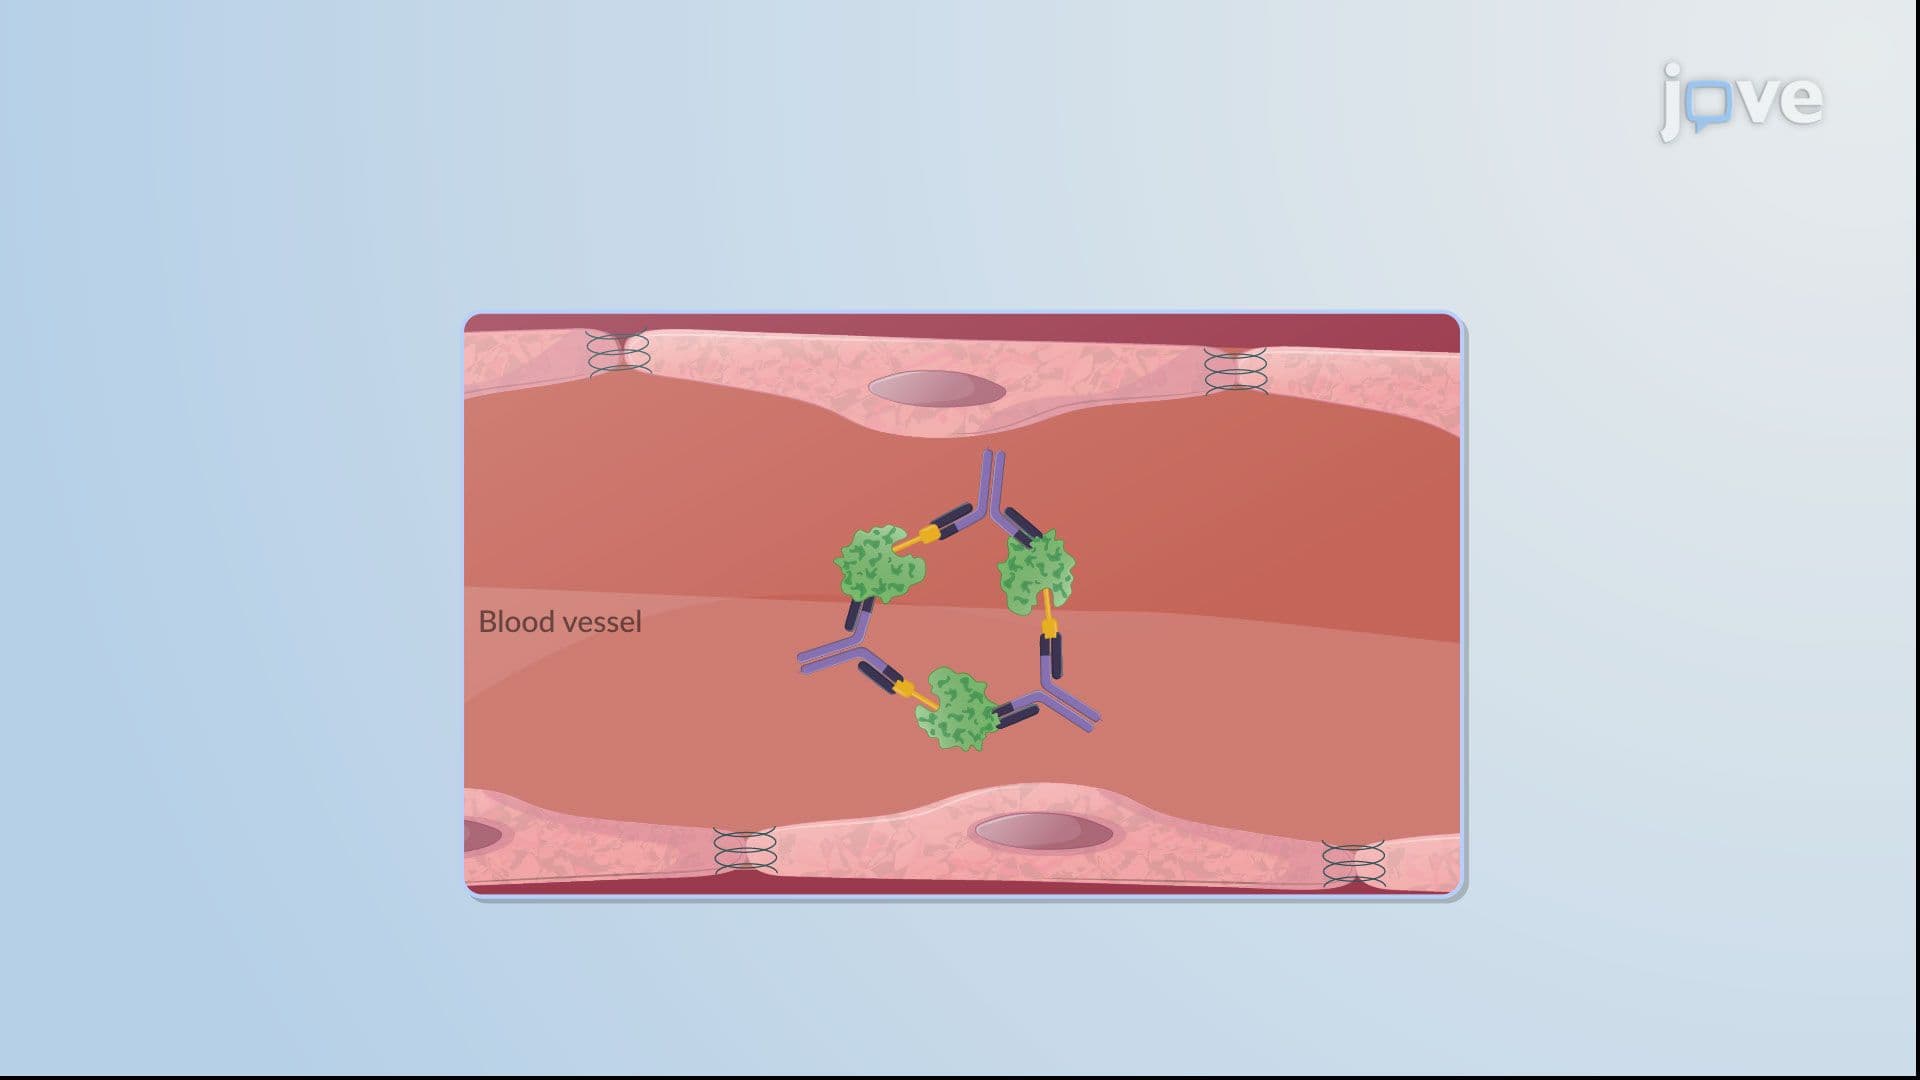
Hypersensitivity Reactions: Immune-Complex Reactions
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...
 01:12
Local Anesthetics: Adverse Effects
While local anesthetics are generally safe and well-tolerated, they can occasionally cause adverse effects that vary in severity. Local anesthetics can induce toxicity at two distinct levels. They can either produce local effects through direct contact with the neural elements or be absorbed into the bloodstream from the injection site, leading to systemic effects.
Once absorbed into the systemic circulation, local anesthetics can affect the organs that depend on the functioning of sodium...
Once absorbed into the systemic circulation, local anesthetics can affect the organs that depend on the functioning of sodium...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
Intravenous regional anesthesia or the Bier block technique is used to anesthetize a specific limb or extremity. It uses exsanguinated or blood-drained vessels to transport local anesthetics or LAs to the peripheral nerve trunks. Lidocaine without vasoconstrictors like epinephrine is most commonly used for this technique. Other drugs used are prilocaine, ropivacaine, and chloroprocaine. Bupivacaine is not recommended for this technique due to its high cardiac toxicity.
One of the advantages of...
One of the advantages of...
 01:19
Depolarizing Blockers: Pharmocokinetics
Depolarizing blockers are administered through intravenous injection. Succinylcholine is the most common choice of depolarizing blockers in emergency clinical practices. Although they have a rapid onset, they readily diffuse away from the motor end plate into the extracellular fluid. They are metabolized by enzymes such as liver butyrylcholinesterase and plasma pseudocholinesterases. This produces a short duration of action, typically 5-10 minutes long, unlike nondepolarizing blockers, which...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Nondepolarizing neuromuscular blockers prevent the membrane depolarization of muscle cells and inhibit muscle contraction. These are usually administered with anesthetics to achieve complete muscle relaxation. Upon administration, these drugs first block the small, rapidly contracting muscles of the face and hands, followed by the larger muscles of the trunk and the intercostal muscles. The diaphragm is the last muscle to be affected.
Although all competitive neuromuscular blockers are designed...
Although all competitive neuromuscular blockers are designed...