The ventilator discontinuation process: an expanding evidence base
Related Experiment Video
Updated: May 11, 2026

A Structured Approach to Extubation in Mechanically Ventilated Rats
Published on: July 18, 2025
1Division of Pulmonary and Critical Care Medicine, Duke University Hospital, Durham, North Carolina 27710, USA. neil.macintyre@duke.edu

Abstract:
The ventilator discontinuation process is an essential component of overall ventilator management. Undue delay leads to excess stay, iatrogenic lung injury, unnecessary sedation, and even higher mortality. On the other hand, premature withdrawal can lead to muscle fatigue, dangerous gas exchange impairment, loss of airway protection, and also a higher mortality. Continued ventilator dependence can be a result of persistent illness or can be a result of poor management. It is obviously important for the clinician to be able to assess both of these issues. An evidence-based task force has recommended regular assessments focusing on the causes of ventilator dependence, regular assessments for evidence of disease stability/reversal, use of regular spontaneous breathing trials (SBTs) as the primary assessment tool for ventilator discontinuation potential, use of separate assessments to evaluate the need for an artificial airway in patients tolerating the SBT, and the use of comfortable, interactive ventilator modes (that do not need to be "weaned") in between regular SBTs. More recent developments have focused on the importance of linking sedation reduction protocols to ventilator discontinuation protocols. Patients with repeated SBT failures are often considered to require prolonged mechanical ventilation (PMV). These patients often receive tracheostomies and are probably better managed with more gradual reductions in support and gradually lengthened spontaneous breathing periods. PMV patients have a high 1-year mortality, and many may ultimately require lifelong support. This evidence base is growing, but the earlier guidelines are standing the test of time. Indeed, practice patterns are evolving in accordance with them. Nevertheless, there is still room for improvement, and further clinical studies, especially in the patient requiring PMV, are needed.
Related Concept Videos
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:24
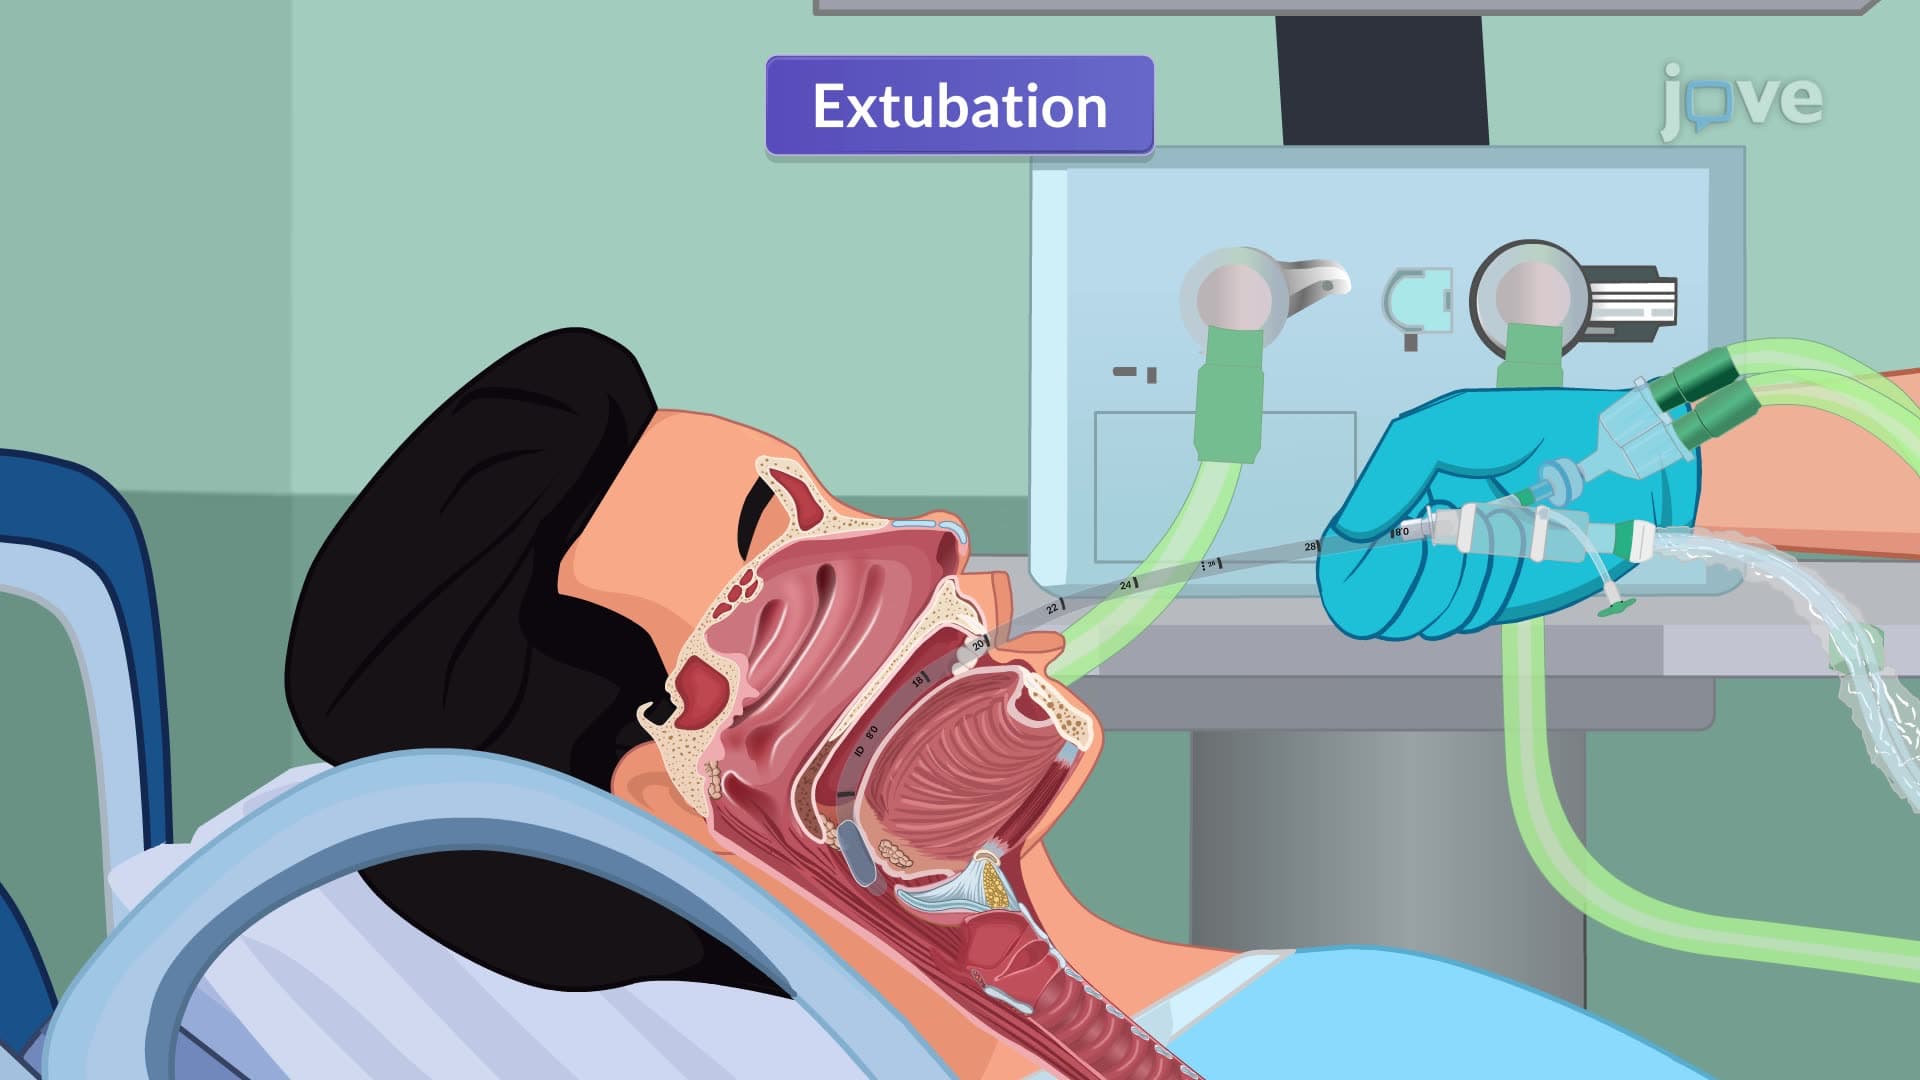
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
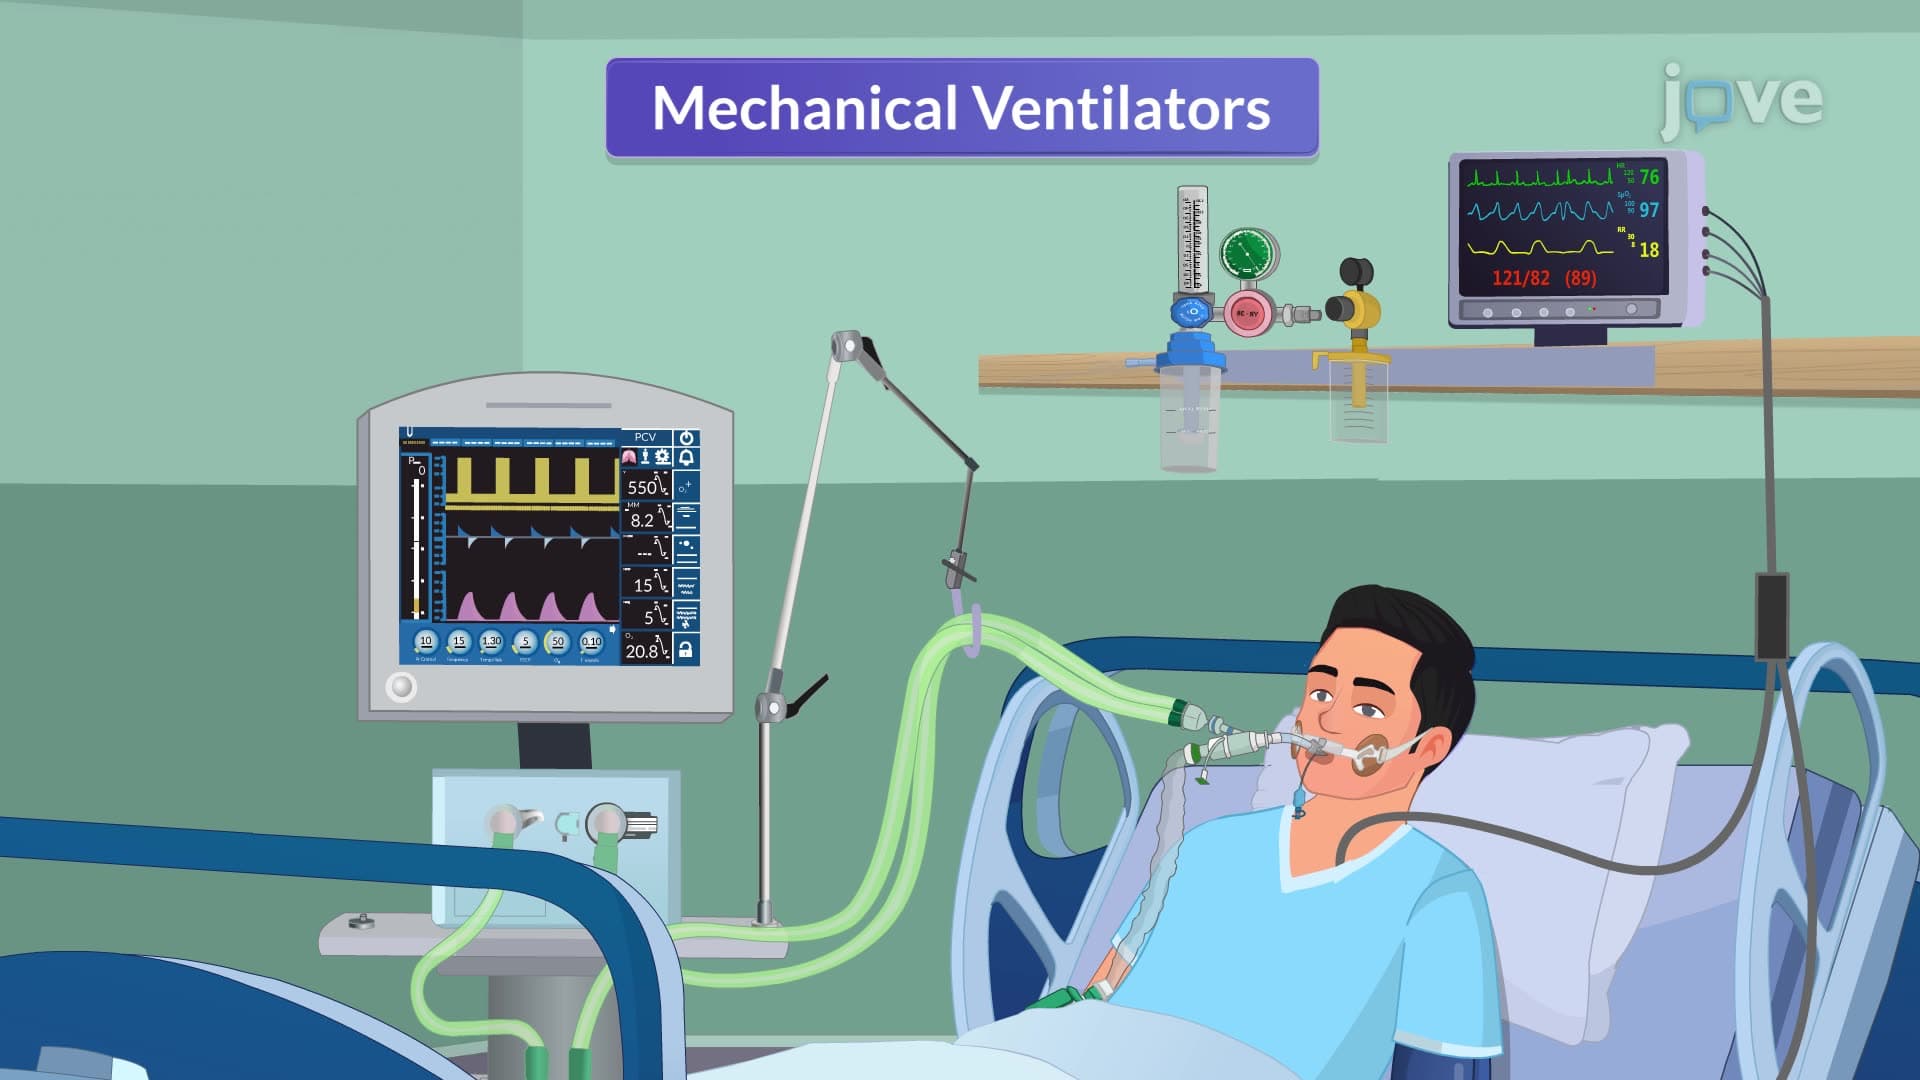
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...