Related Experiment Video
Updated: May 11, 2026

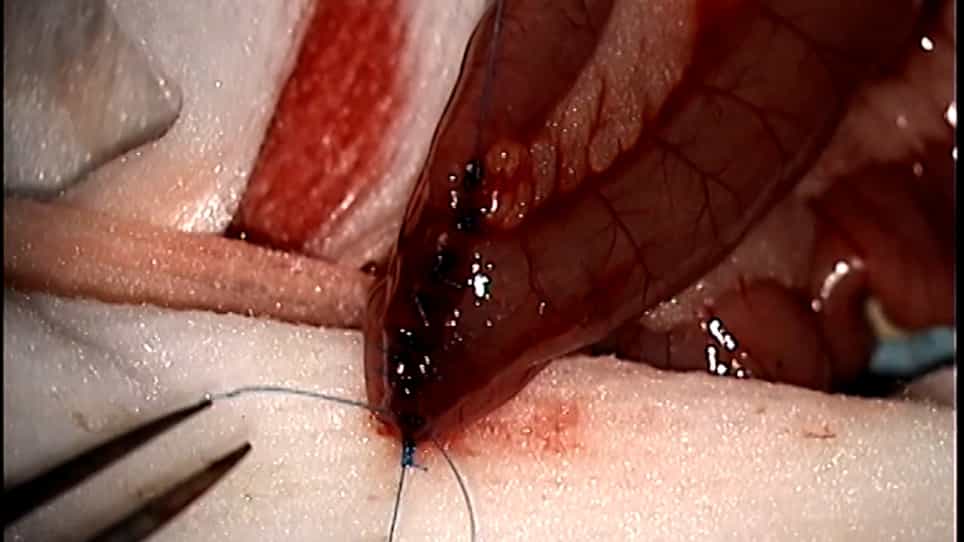
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Gastric bypass does not normalize obesity-related changes in ghrelin profile and leads to higher acylated ghrelin
Rocco Barazzoni1, Michela Zanetti, Carlo Nagliati
1Department of Medical, Surgical and Health Sciences, Internal Medicine Clinics, University of Trieste, Trieste, Italy. barazzon@units.it

Objective:
Gastric bypass (GBP) lowers food intake, body weight, and insulin resistance in severe obesity (SO). Ghrelin is a gastric orexigenic and adipogenic hormone contributing to modulate energy balance and insulin action. Total plasma ghrelin (T-Ghr) level is low and inversely related to body weight and insulin resistance in moderately obese patients, but these observations may not extend to the orexigenic acylated form (A-Ghr) whose plasma concentration increase in moderate obesity.
Design And Methods:
We investigated the impact of GBP on plasma T-, A-, and A/T-Ghr in SO patients (n = 28, 20 women), with measurements at baseline and 1, 3, 6, and 12 months after surgery. Additional cross-sectional comparison was performed between nonobese, moderately obese, and SO individuals before GBP and at the end of the follow-up period.
Results:
Before GBP, SO had lowest T-Ghr and highest A/T-Ghr profile compared with both nonobese and moderately obese individuals. Lack of early (0-3 months from GBP) T-Ghr changes masked a sharp increase in A-Ghr and A/T-Ghr profile (P < 0.05) that remained elevated following later increments (6-12 months) of both T- and A-Ghr (P < 0.05). Levels of A-Ghr and A/T-Ghr at 12 months of follow-up remained higher than in matched moderately obese individuals not treated with surgery (P < 0.05).
Conclusions:
The data show that following GBP, early T-Ghr stability masks elevation of A/T-Ghr, that is stabilized after later increments of both T- and A-hormones. GBP does not normalize the obesity-associated elevated A/T-Ghr ratio, instead resulting in enhanced A-Ghr excess. Excess A-Ghr is unlikely to contribute to, and might limit, the common GBP-induced declines of appetite, body weight, and insulin resistance.

Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:11
Pyloric Obstruction
 01:30
Regulation of Food Intake
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:26
Gastritis II: Pathophysiology
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...