Related Experiment Video
Updated: May 11, 2026
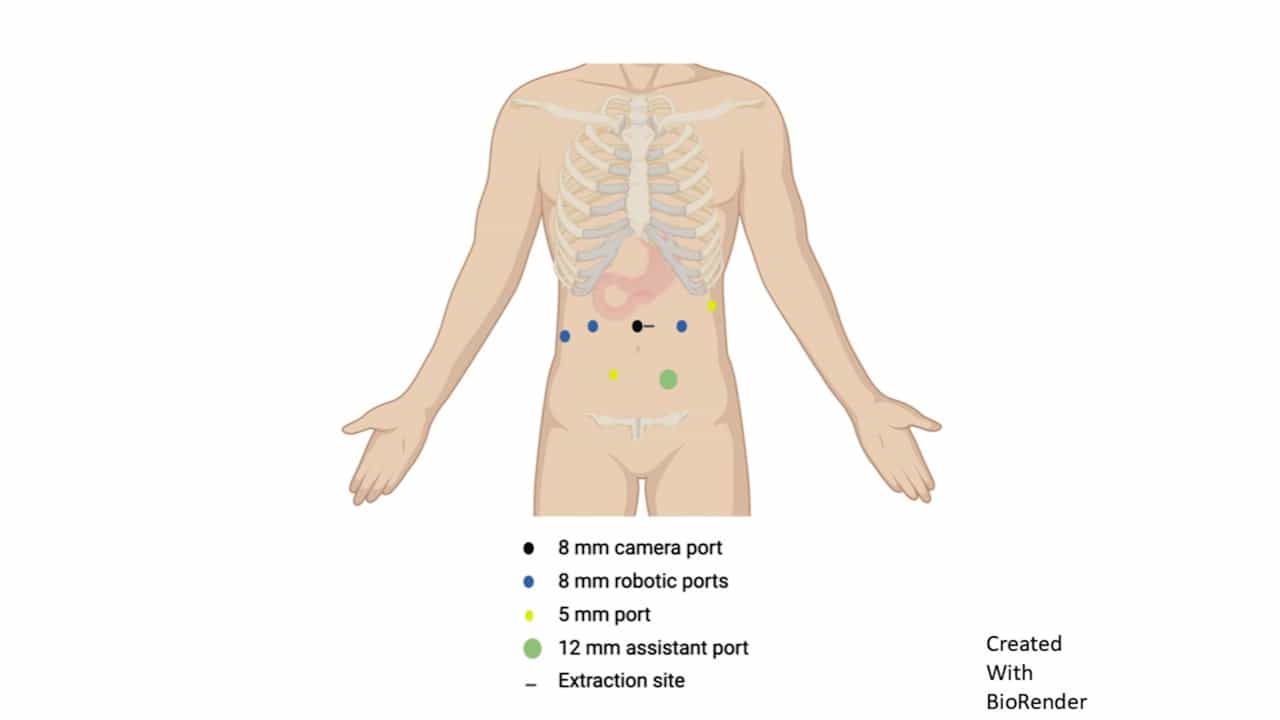
Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Approach to the older patient with stage II/III colorectal cancer: who should get curative-intent therapy?
Erika Ramsdale1, Hanna Sanoff, Hyman Muss
1From the University of Chicago Medical Center, Department of Medicine, Section of Hematology/Oncology, Chicago, IL; Lineberger Comprehensive Cancer Center, University of North Carolina, Chapel Hill, Chapel Hill, NC.

Abstract:
The majority of new colorectal cancer diagnoses occur in adults 65 and older a rapidly growing segment of the U.S. population. Older adults are a markedly heterogeneous group, and although recent clinical trials in locally advanced colorectal cancer have incorporated limited numbers of older patients, the data can not be generalized to most older patients. In particular, patients who are not "fit"-those with poor functional reserve, major comorbidities, or who otherwise meet criteria for frailty or "prefrailty"-are poorly represented in published trials. Population-based data demonstrate that older adults are much less likely to be treated in the adjuvant or neoadjuvant settings for stage II/III colorectal cancer, but it is unclear what the basis should be for withholding potentially curative therapy. Age and Eastern Cooperative Oncology Group (ECOG) performance status (PS) are frequently used to determine eligibility for treatment, but data increasingly suggest these are inadequate; the emerging definition of a spectrum of "fit" to "frail" older patients may provide additional guidance. Available data suggest that fit older patients may benefit as much from curative-intent therapy as younger patients. For frail or vulnerable (prefrail) patients, on the other hand, the benefit must be carefully weighed against the risk of toxicity and competing risks from their comorbidities. Life expectancy and patient preferences should always be elucidated. Geriatrician comanagement may be helpful in determining priorities, providing a comprehensive assessment, and modifying competing risk factors. Even many vulnerable or frail patients can successfully complete (and derive benefit from) carefully considered treatment regimens.
More Related Videos
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
 03:43
Structured Approach to Colonoscopy Technique Optimization: A Single-Center Experience with Novice Endoscopists
Published on: July 11, 2025
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:25
Endoscopic Procedures II: Colonoscopy
 02:56
Treatment Resistant Cancers
 01:27
Tumor Immunotherapy
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...