Related Experiment Video
Updated: May 11, 2026


Quantifiable and Inexpensive Cell-Free Fluorescent Method to Confirm the Ability of Novel Compounds to Chelate Iron
Published on: February 23, 2024
Effect of deferasirox chelation on liver iron and total body iron concentration
Javed Ahmed1, Noor Ahmad, Bhavin Jankharia
1Department of Pediatrics, Dr. Balabhai Nanavati Hospital, Mumbai, India.

Objective:
To determine efficacy of Deferasirox (DFX) on total body iron and liver iron concentration (LIC) as estimated by serum ferritin (SF) and liver MRI T2.
Methods:
Thirty patients had baseline MRI T2 of the liver performed to determine LIC before starting DFX therapy and classified as normal >6.3 milliseconds (ms), mild 6.3-2.7 ms, moderate 2.7-1.4 ms and severe iron overload <1.4 ms. DFX was given 25-35 mg/kg/d. The serum ferritin (SF) level was estimated every 3 monthly. Liver iron is expressed as liver R2 = 1,000/T2. The primary end point of the study was to determine change in SF and liver MRI R2 values after 18 mo of therapy.
Results:
All 30 patients had some degree of liver iron overload; 11 (36.6 %) had severe, 15 (50 %) had moderate while 4 (13.3 %) had mild overload. The pre-DFX therapy median SF of all was 3604.5 ng/mL (IQR 2357.0-5056.0) and median liver R2 was 574.71 Hz (IQR 411.3-770.8). After 18 mo, SF dropped significantly to a median of 2036.5 ng/mL (IQR 1700.0-3162.0) (p = 0.0011), while median liver R2 decreased from 574.71 to 568.18 Hz (IQR 393.4-803.2) which was not significant (p = 0.986).
Conclusions:
DFX monotherapy at the doses used decreases total body iron, but does not significantly decrease liver iron. It is well tolerated by Indian thalassemia patients, with observed side effects including rash, diarrhea, and transient albuminuria. MRI T2 (and derived R2) can serve as useful method in non invasive monitoring of LIC in thalassemia patient management.
Insights
Deferasirox (DFX) therapy effectively reduces total body iron in Indian thalassemia patients, as indicated by lower serum ferritin levels. However, it did not significantly decrease liver iron concentration after 18 months. DFX was well-tolerated.
Area of Science:
- Hematology
- Pharmacology
- Medical Imaging
Background:
- Iron overload is a common complication in patients with thalassemia, necessitating effective chelation therapy.
- Monitoring liver iron concentration (LIC) is crucial for managing iron overload and preventing organ damage.
Purpose of the Study:
- To evaluate the efficacy of Deferasirox (DFX) in reducing total body iron and liver iron concentration (LIC).
- To assess changes in serum ferritin (SF) and liver iron as measured by MRI T2 (R2) after 18 months of DFX therapy.
Main Methods:
- Thirty Indian thalassemia patients with liver iron overload underwent baseline liver MRI T2 to quantify LIC.
- Patients received DFX at 25-35 mg/kg/d for 18 months, with regular SF monitoring.
- Liver R2 values (1,000/T2) were used to assess changes in LIC.
Main Results:
- All patients exhibited some degree of liver iron overload at baseline.
- After 18 months, serum ferritin levels significantly decreased (p=0.0011).
- Liver R2 values showed a non-significant decrease, indicating no significant reduction in LIC (p=0.986).
Conclusions:
- DFX monotherapy effectively reduces total body iron but does not significantly decrease liver iron concentration in this cohort.
- DFX was well-tolerated by Indian thalassemia patients, with mild side effects observed.
- MRI T2 (R2) is a valuable non-invasive tool for monitoring LIC in thalassemia patient management.


Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:09
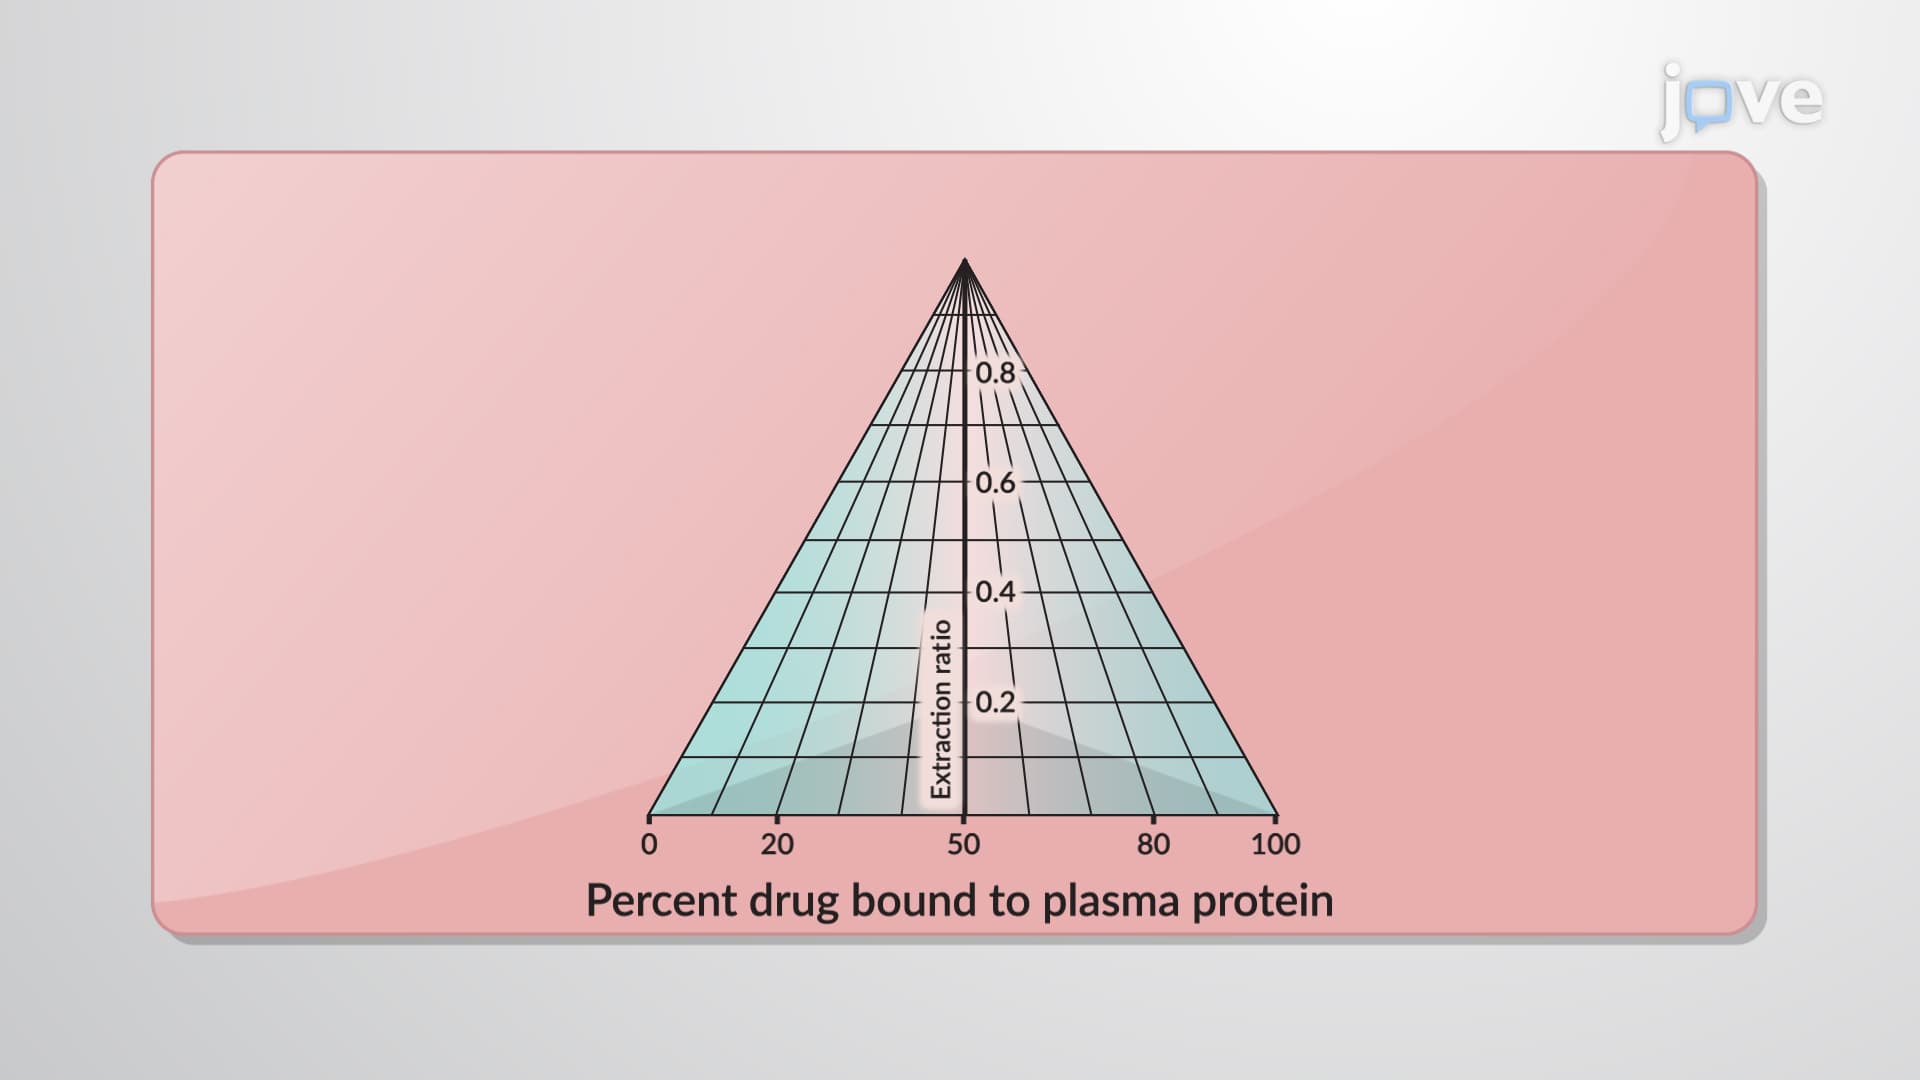
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 00:56
Extraction: Advanced Methods