Related Experiment Video
Updated: May 10, 2026
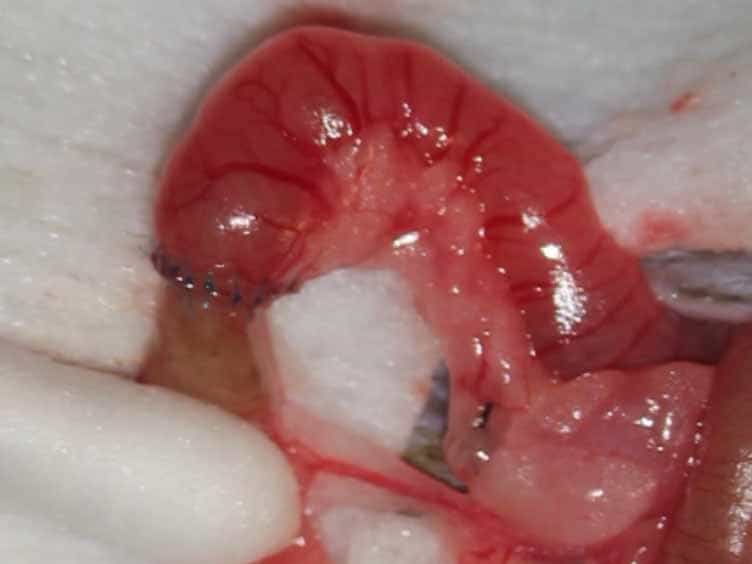
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Submucosal plexitis as a predictor of postoperative surgical recurrence in Crohn's disease
Aude Bressenot1, Jean-Baptiste Chevaux, Nicolas Williet
1Inserm U954, Genetic Nutrition and Exposure to Environmental Risks (NGERE), Henri Poincaré University, Vandoeuvre-lès-Nancy, France.

Background:
The presence of submucosal or myenteric plexitis was associated with clinical and endoscopic Crohn's disease (CD) recurrence after ileocolonic resection. We assessed the value of both submucosal and myenteric plexitis for predicting postoperative surgical recurrence in CD.
Methods:
We performed a retrospective study using the database of the Department of Pathology of Nancy University Hospital. All patients who underwent CD-related resection between 1996 and 2008 were analyzed. The proximal resection margin was analyzed blindly by 2 expert pathologists. Plexitis was evaluated by counting each cell type (mast cell, plasmocyte, lymphocyte, eosinophil, and neutrophil) in both submucosal and myenteric plexuses. The optimal cut-off value for each cell type was determined by using receiver operating characteristic analysis. Cox proportional hazards regression analysis was used to identify independent predictors of the second CD-related surgery.
Results:
Sixty-seven patients were included in the study. Median duration of follow-up was 46 months. Using Kaplan-Meier survival analysis, the proportion of patients without second surgery was 68% at 5 years. In multivariate analysis, using Cox proportional hazards regression analysis, early surgical revision after the first ileocecal resection (hazard ratio = 9.56; 95% confidence interval, 2.02-45.19; P = 0.0046), the presence of at least one eosinophil in the submucosal plexus (hazard ratio = 8.02; 95% confidence interval, 1.87-34.47; P = 0.0054), and the presence of more than 6 lymphocytes in the submucosal plexus (hazard ratio = 5.84; 95% confidence interval, 1.23-27.65; P = 0.0269) were independently associated with risk of surgical recurrence.
Conclusions:
Early surgical revision and submucosal plexitis in proximal margins of ileocolonic resection specimens are independently associated with CD surgical recurrence.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...