Related Experiment Video
Updated: May 10, 2026
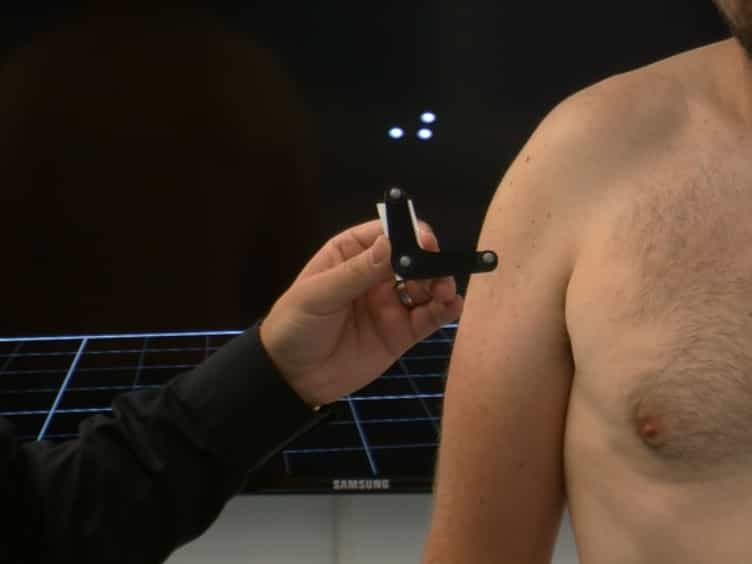

Measurement of Dynamic Scapular Kinematics Using an Acromion Marker Cluster to Minimize Skin Movement Artifact
Published on: February 10, 2015
Shoulder motion, strength, and functional outcomes in children with established malunion of the clavicle
Donald S Bae1, Apurva S Shah, Leslie A Kalish
1Department of Orthopaedic Surgery, Boston Children's Hospital, Boston, MA 02115, USA. donald.bae@childrens.harvard.edu

Insights
Pediatric clavicle malunions rarely cause significant loss of shoulder motion or strength. Most children treated nonoperatively for displaced clavicle fractures achieve good outcomes, with surgery not always necessary.
Area of Science:
- Orthopedic surgery
- Pediatric orthopedics
- Traumatology
Background:
- Displaced clavicle fractures in adults are linked to poor outcomes with nonoperative treatment.
- Limited data exists on the effects of clavicle malunion in pediatric populations.
Purpose of the Study:
- To evaluate pain, function, range of motion, and strength in children with displaced clavicle fractures treated nonoperatively.
Main Methods:
- 16 pediatric patients with displaced mid-diaphyseal clavicle fractures treated nonoperatively were assessed.
- Outcomes measured included Visual Analog Scale (VAS) for pain and aesthetics, Disabilities of the Arm, Shoulder, and Hand (DASH) and Pediatric Outcomes Data Collection Instrument (PODCI) questionnaires, and bilateral shoulder range of motion and strength testing.
Main Results:
- All fractures achieved union; minor reductions in shoulder flexion and abduction were observed.
- No significant differences in shoulder strength were detected between injured and uninjured sides.
- Most patients reported low pain and high satisfaction with function and treatment, with only one requiring corrective surgery.
Conclusions:
- Skeletally immature patients with clavicle malunions generally do not experience clinically significant loss of shoulder motion or strength.
- Surgical fixation for displaced clavicle fractures in children may not be routinely indicated based solely on motion and strength concerns.
- Further research is needed to identify risk factors for symptomatic malunions in the pediatric population.
Background:
Recent investigations of displaced clavicle fractures in adults have demonstrated a higher prevalence of nonunion, symptomatic malunion, diminished functional outcome, and decreased strength with nonoperative treatment. Although these data have led to increased surgical management of displaced fractures, little published information is available regarding the consequences of malunion in the pediatric population. The purpose of this investigation was to assess pain, functional outcome, range of motion, and strength in children with displaced clavicle fractures treated nonoperatively.
Methods:
Clinical evaluation of 16 patients with mid-diaphyseal clavicle fractures and >2 cm of initial displacement was performed; all had undergone nonoperative treatment and went on to radiographic malunion. The mean age at the time of injury was 12.2±3.3 years. Pain, aesthetic appearance, and satisfaction with treatment were rated by patients on a visual analog scale (VAS) (range 0 to 10 with 10 indicating the worst score). Patient-based outcomes were assessed with the Disabilities of the Arm, Shoulder, and Hand (DASH) questionnaire and the Pediatric Outcomes Data Collection Instrument (PODCI). Bilateral shoulder motion was measured by a physical therapist. Isokinetic strength testing of the bilateral shoulders was performed with a Biodex dynometer. Range of motion and strength were analyzed with a multivariable regression, controlling for hand dominance. The mean follow-up was 27.2 months after injury.
Results:
All displaced fractures treated nonoperatively achieved union. Overall, there was reduced forward flexion and abduction on the injured side compared with the contralateral sides of 7.3 and 6.5 degrees, respectively, adjusted for hand dominance (P<0.05). Biodex testing did not detect any significant difference in abduction or adduction torque or power between affected and unaffected shoulders. The mean VAS score for pain was 1.6, with 4 patients reporting pain ≥to 3. The mean VAS scores for satisfaction with aesthetic appearance was 2.7, with 4 patients reporting scores >5. The mean VAS scores for satisfaction with treatment was 2.0, with only 1 patient scoring >5. The mean DASH score was 4.9±7.5, with 3 patients scoring ≥10. The mean scores on the DASH sports and performing arts module was 1.9±4.2, with only 1 patient scoring ≥10. The mean global PODCI score was 94.5±6.0. The mean PODCI scores for upper extremity function, sports, and pain were 97.9±5.5, 95.4±5.3, and 84.6±20.5, respectively. Only 1 patient was symptomatic enough to require corrective osteotomy.
Conclusions:
Skeletally immature patients with established clavicle fracture malunions do not develop clinically meaningful loss of shoulder motion or abduction/adduction strength. Routine surgical fixation for displaced, nonsegmental clavicle fractures may not be justified based upon concerns regarding shoulder motion and strength alone. Further investigation is required to determine the risk factors and causes of pain and functional compromise in the minority of pediatric patients with symptomatic malunions.
Level Of Evidence:
Level IV.
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...