Related Experiment Video
Updated: May 10, 2026


Auricular Acupuncture as a Traditional Chinese Medicine Therapy for Chronic Obstructive Pulmonary Disease Combined with Sleep Disorders
Published on: August 18, 2023
Common lung conditions: chronic obstructive pulmonary disease
1University of Kansas School of Medicine, 3901 Rainbow Blvd Mailstop 4010, Kansas City, KS 66160, jdelzell@kumc.edu.

Abstract:
The etiology of chronic obstructive pulmonary disease (COPD) is chronic lung inflammation. In the United States, this inflammation most commonly is caused by smoking. COPD is diagnosed when an at-risk patient presents with respiratory symptoms and has irreversible airway obstruction indicated by a forced expiratory volume in 1 second/forced vital capacity ratio of less than 0.7. Management goals for COPD include smoking cessation, symptom reduction, exacerbation reduction, hospitalization avoidance, and improvement of quality of life. Stable patients with COPD who remain symptomatic despite using short-acting bronchodilators should start inhaled maintenance drugs to reduce symptoms and exacerbations, avoid hospitalizations, and improve quality of life. A long-acting anticholinergic or a long-acting beta2-agonist (LABA) can be used for initial therapy; these drugs have fewer adverse effects than inhaled corticosteroids (ICS). If patients remain symptomatic despite monotherapy, dual therapy with a long-acting anticholinergic and a LABA, or a LABA and an ICS, may be beneficial. Triple therapy (ie, a long-acting anticholinergic, a LABA, and an ICS) also is used, but it is unclear if triple therapy is superior to dual therapy. Roflumilast, an oral selective inhibitor of phosphodiesterase 4, is used to manage moderate to severe COPD. Continuous oxygen therapy is indicated for patients with COPD who have severe hypoxemia (ie, PaO2 less than 55 mm Hg or an oxygen saturation less than 88% on room air). Nonpharmacologic strategies also are useful to improve patient outcomes. Pulmonary rehabilitation improves dyspnea and quality of life. Pulmonary rehabilitation after an acute exacerbation reduces hospitalizations and mortality, and improves quality of life and exercise capacity. Smoking cessation is the most effective management strategy for reducing morbidity and mortality in patients with COPD. Lung volume reduction surgery, bullectomy, and lung transplantation are surgical interventions that are appropriate for some patients with COPD.
More Related Videos
 04:53
Acupoint Application Combined with Ear Plaster Therapy for Treating Sleep Disorders with Acute Exacerbation of Chronic Obstructive Pulmonary Disease
Published on: October 18, 2024
 04:03
Alternative Therapy for Acute Exacerbation of Chronic Obstructive Pulmonary Disease: Moving Cupping Along Meridians
Published on: September 27, 2024
Related Concept Videos
 01:23
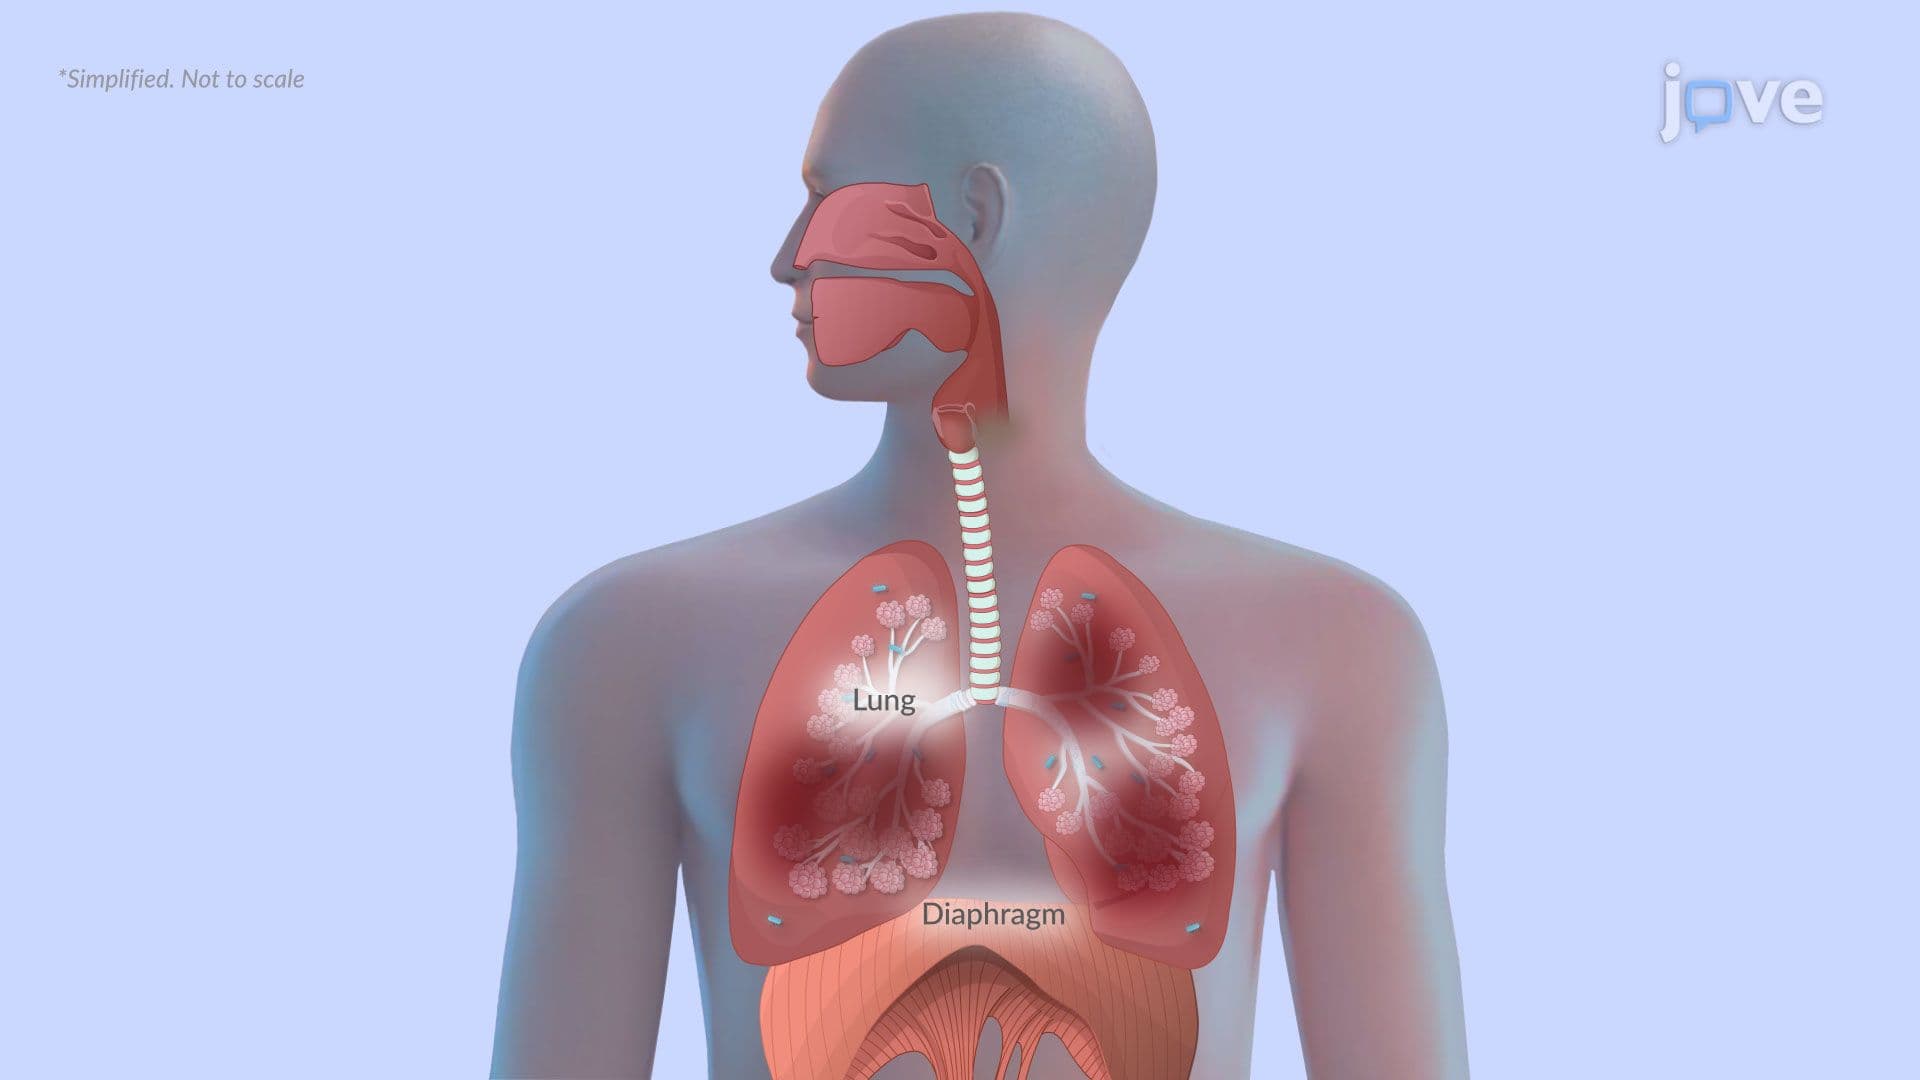
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation