Related Experiment Video
Updated: May 10, 2026

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
A randomized, double-blind study of repeated incobotulinumtoxinA (Xeomin(®)) in cervical dystonia
Virgilio Gerald H Evidente1, Hubert H Fernandez, Mark S LeDoux
1Movement Disorders Center of Arizona, 9590 E. Ironwood Square Drive, #225, Scottsdale, AZ, 85258, USA, vevidente@movementdisorders.us.

Abstract:
IncobotulinumtoxinA (Xeomin(®), NT 201), a preparation without accessory (complexing) proteins, has shown comparable efficacy and safety to onabotulinumtoxinA in treating cervical dystonia (CD). This study evaluated the efficacy and safety of repeated incobotulinumtoxinA injections in subjects with CD. Following a ≤20-week placebo-controlled, randomized, double-blind, single-dose main period, subjects could enter a ≤68-week prospective, randomized, double-blind, repeated-dose, flexible-interval (minimum 6 weeks) extension period with 240 U or 120 U of incobotulinumtoxinA (≤5 injections). Outcome measures included the Toronto Western Spasmodic Torticollis Rating Scale (TWSTRS) and adverse events (AEs). Of 219 subjects completing the main period, 214 were randomized in the extension period to receive incobotulinumtoxinA 240 U (n = 111) or 120 U (n = 103); 169 subjects completed the extension period, with 90 receiving five injection sessions. Both doses of incobotulinumtoxinA provided statistically significant and clinically relevant improvements in mean TWSTRS-Total, -Severity, -Disability, and -Pain scores, from each injection session to respective 4-week follow-up visits. The most frequently reported AE was dysphagia (240 U: 23.4 %; 120 U: 12.6 %), which did not result in any study withdrawals. There was no impact of injection interval on the incidence of AEs (post hoc analysis). A major limitation of this study was the fixed dose design requested by regulatory authorities, which does not reflect clinical practice. However, repeated incobotulinumtoxinA injections (240 or 120 U; flexible intervals) provided sustained efficacy and were well tolerated, with no unexpected safety risks following repeated injections. The incidence of AEs was similar in subjects requiring repeated injections at shorter intervals (≤12 weeks) compared with those treated using longer intervals (>12 weeks).

Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic drugs,...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:17
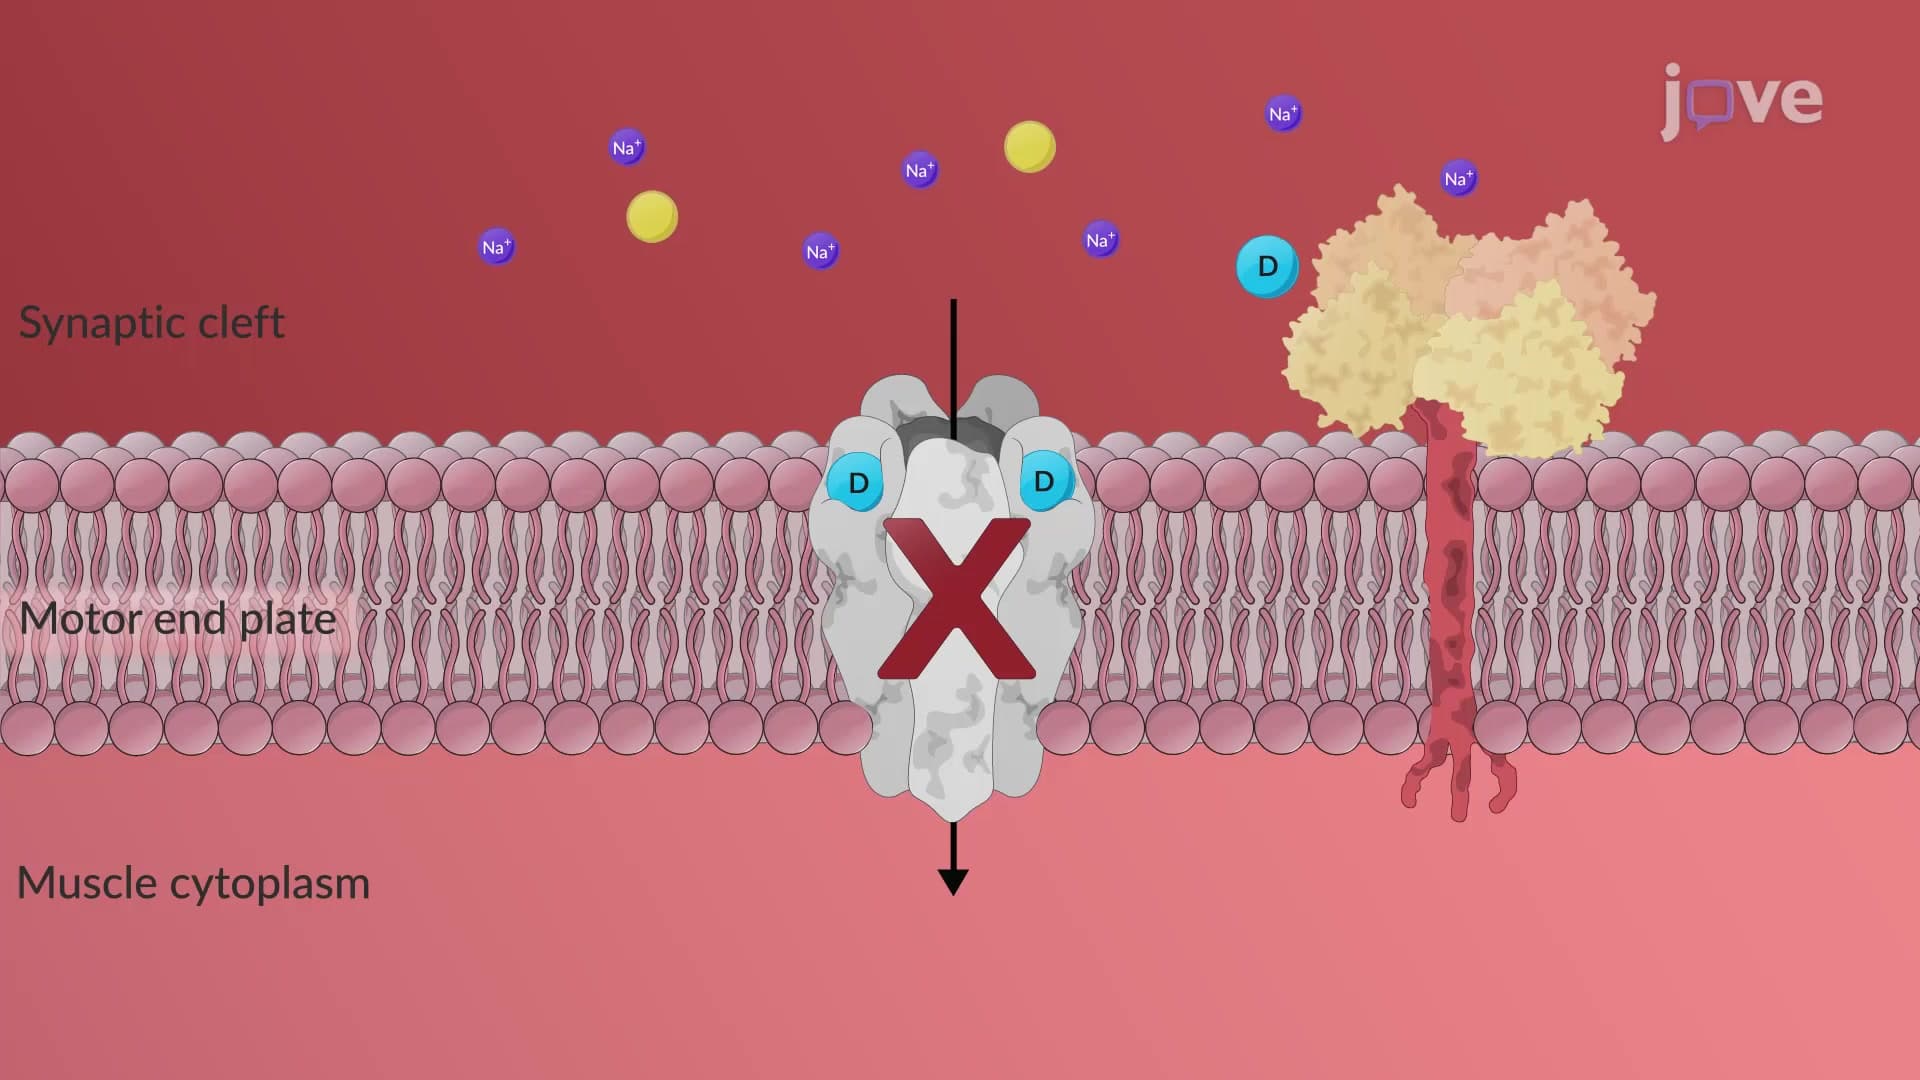
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...