Related Experiment Video
Updated: May 10, 2026

Open Tracheostomy Gastric Acid Aspiration Murine Model of Acute Lung Injury Results in Maximal Acute Nonlethal Lung Injury
Published on: February 26, 2017
GERD related micro-aspiration in chronic mustard-induced pulmonary disorder
Rasoul Aliannejad1, Seyed-Mehdi Hashemi-Bajgani, Asharaf Karbasi
1Respiratory Diseases and TB Research Center of Guilan University of Medical Science, Razi Hospital, Rasht, Iran.

Background And Aim:
Bronchiolitis obliterans (BO) is the main pulmonary involvement resulting from sulfur mustard (SM) gas exposure that was used against Iranian civilians and military forces during the Iran-Iraq war. The present study aimed to investigate the prevalence of gastro-esophageal reflux (GER) and gastric micro-aspiration in SM gas injured patients with chronic pulmonary diseases and recurrent episodes of exacerbations.
Materials And Methods:
This cross-sectional study was done at Baqiyatallah University of Medical Sciences, Tehran, Iran. Gastric micro-aspiration and GER were assessed in the enrolled patients by assessing bile acids, pepsin and trypsin in their bronchoalveolar lavage fluid.
Results:
Our result showed that bile acids were found to be high in 21.4% patients, and low in 53.6% of patients. Only in 16% patients, no bile was detected in the BALF. Trypsin and pepsin were detected in BAL fluid of all patients.
Conclusion:
Most of BO patients after exposure to SM suffer GER, while none the etiologic factors of GER in post lung transplant BO are present. It would be hypothesized that GER per se could be considered as an aggregative factor for exacerbations in patients. Further studies will provide more advances to better understanding of pathophysiological mechanism regarding GER and BO and treatment.
Insights
Sulfur mustard (SM) gas exposure can cause bronchiolitis obliterans (BO). This study found that most BO patients suffer from gastro-esophageal reflux (GER), which may worsen their chronic lung disease exacerbations.
Area of Science:
- Pulmonary Medicine
- Toxicology
- Gastroenterology
Background:
- Bronchiolitis obliterans (BO) is a significant pulmonary complication following sulfur mustard (SM) gas exposure.
- SM gas was used against Iranian civilians and military personnel during the Iran-Iraq war, leading to long-term health issues.
- Chronic pulmonary diseases and recurrent exacerbations are common in SM-exposed individuals.
Purpose of the Study:
- To investigate the prevalence of gastro-esophageal reflux (GER) and gastric micro-aspiration in patients with chronic pulmonary diseases after SM gas injury.
- To assess the potential role of GER in exacerbations of lung disease in SM survivors.
Main Methods:
- A cross-sectional study was conducted at Baqiyatallah University of Medical Sciences, Tehran, Iran.
- Gastric micro-aspiration and GER were evaluated by analyzing bile acids, pepsin, and trypsin in bronchoalveolar lavage (BAL) fluid.
- BAL fluid analysis included detection of bile acids, pepsin, and trypsin.
Main Results:
- Bile acids were detected in the BAL fluid of 75% of patients (21.4% high, 53.6% low).
- No bile was detected in only 16% of patients.
- Pepsin and trypsin were present in the BAL fluid of all evaluated patients.
Conclusions:
- The majority of BO patients exposed to SM exhibit signs of GER.
- Unlike post-lung transplant BO, the typical etiologic factors for GER are absent in these patients.
- GER is hypothesized to be an aggravating factor for exacerbations in SM-induced BO, warranting further investigation into its pathophysiological mechanisms and treatment.

Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:25
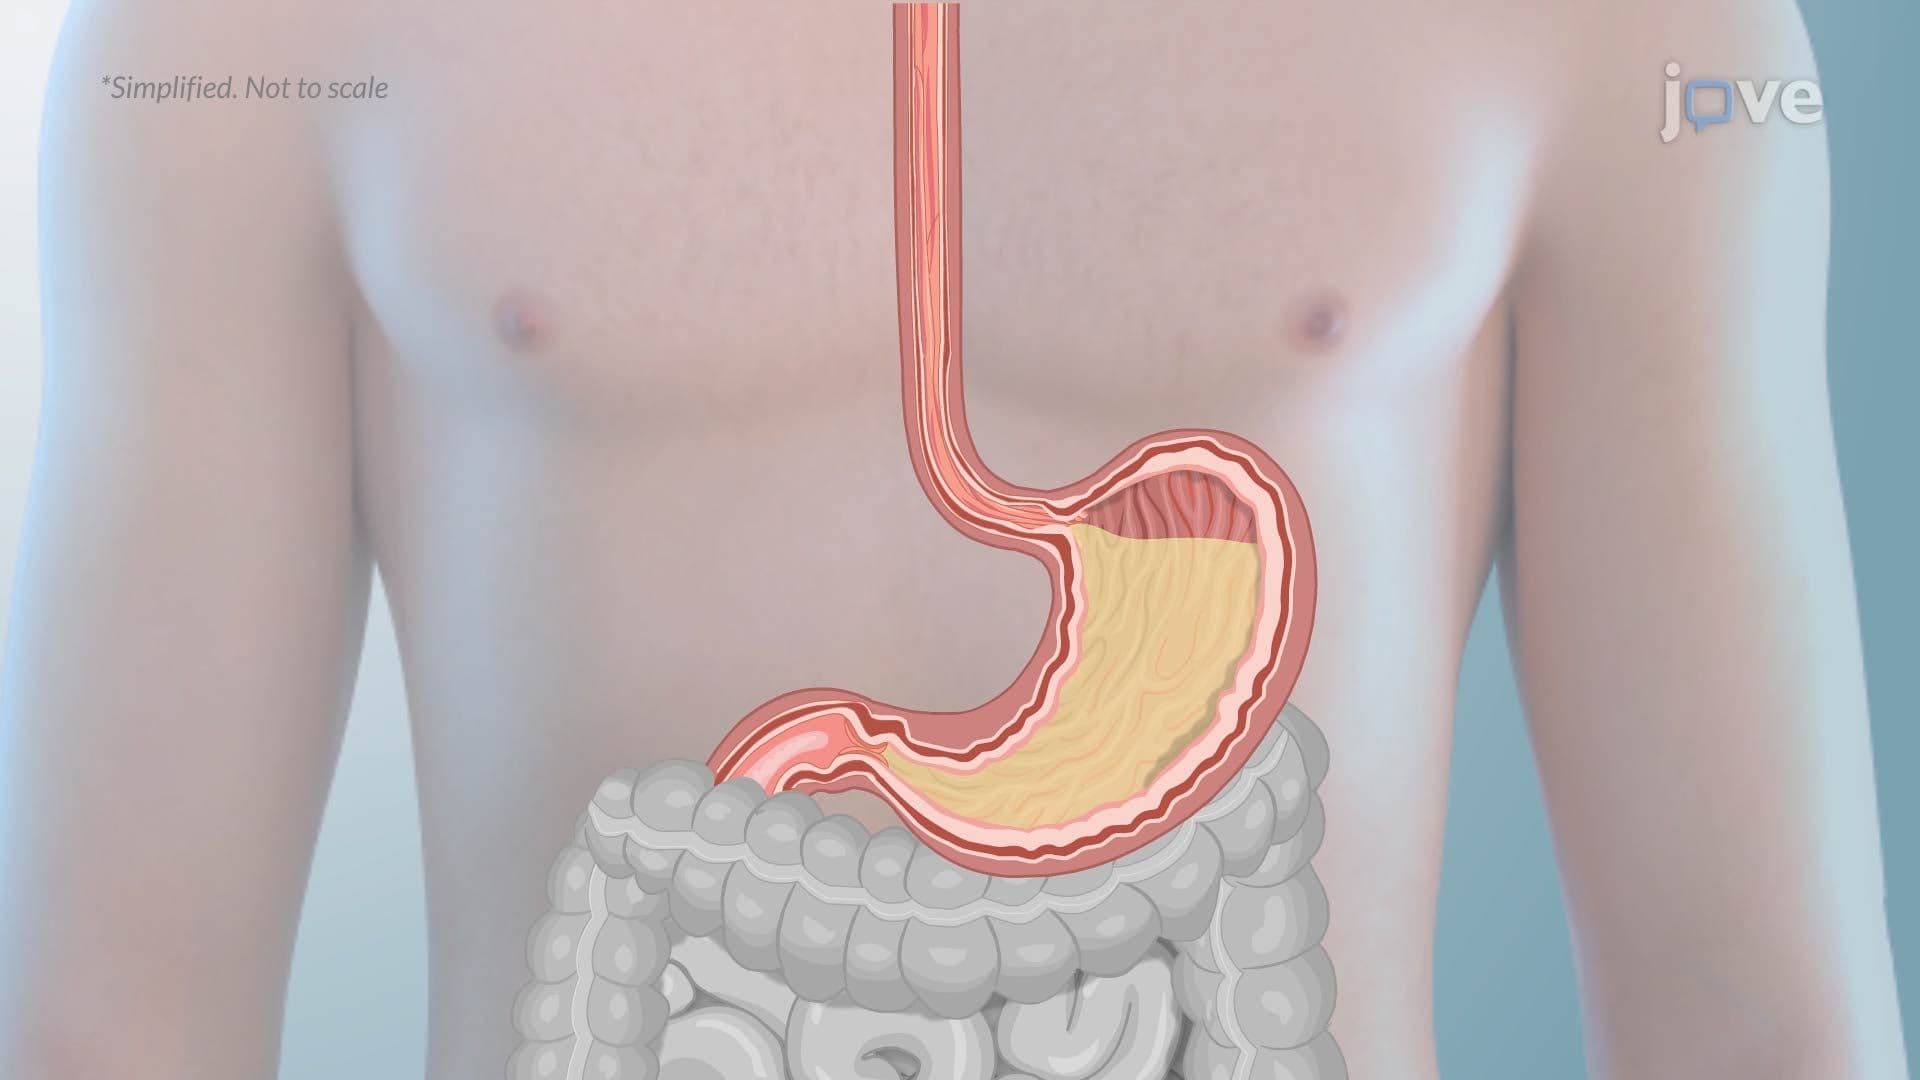
Gastroesophageal Reflux Disease
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation