Related Experiment Video
Updated: May 10, 2026

Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Development of dysphagia and trismus developed after c1-2 posterior fusion in extended position
Haruo Misawa1, Masato Tanaka, Yoshihisa Sugimoto
1Department of Orthopaedic Surgery, Kure Kyosai Hospital, Kure, Hiroshima 737-8505, Japan. misharuo@yahoo.co.jp

Abstract:
Cervical misalignment after upper cervical fusion including the occipital bone may cause trismus or dysphagia, because the occipito-atlanto joint is associated with most of the flex and extended motion of the cervical spine. There are no reports of dysphagia and trismus after C1-2 fusion. The purpose of this paper is to demonstrate the potential risk of dysphagia and trismus even after upper cervical short fusion without the occipital bone. The patient was a 69-year-old man with myelopathy caused by os odontoideum and Klippel-Feil syndrome, who developed dysphagia and trismus immediately after C1-2 fusion and C3-6 laminoplasty. Radiographs and CT revealed that his neck posture was extended, but his symptoms still existed a week after surgery. The fixation angle was hyperextended 12 days after the first surgery. His symptoms disappeared immediately after revision surgery. The fixation in the neck-flexed position is thought to be the main cause of the patient's post-operative dysphagia and trismus. Dysphagia and trismus may occur even after short upper cervical fusion without the occipital bone or cervical fusion in the neck-extended position. The pre-operative cervical alignment and range of motion of each segment should be thoroughly evaluated.
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:27
Esophageal Achalasia
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
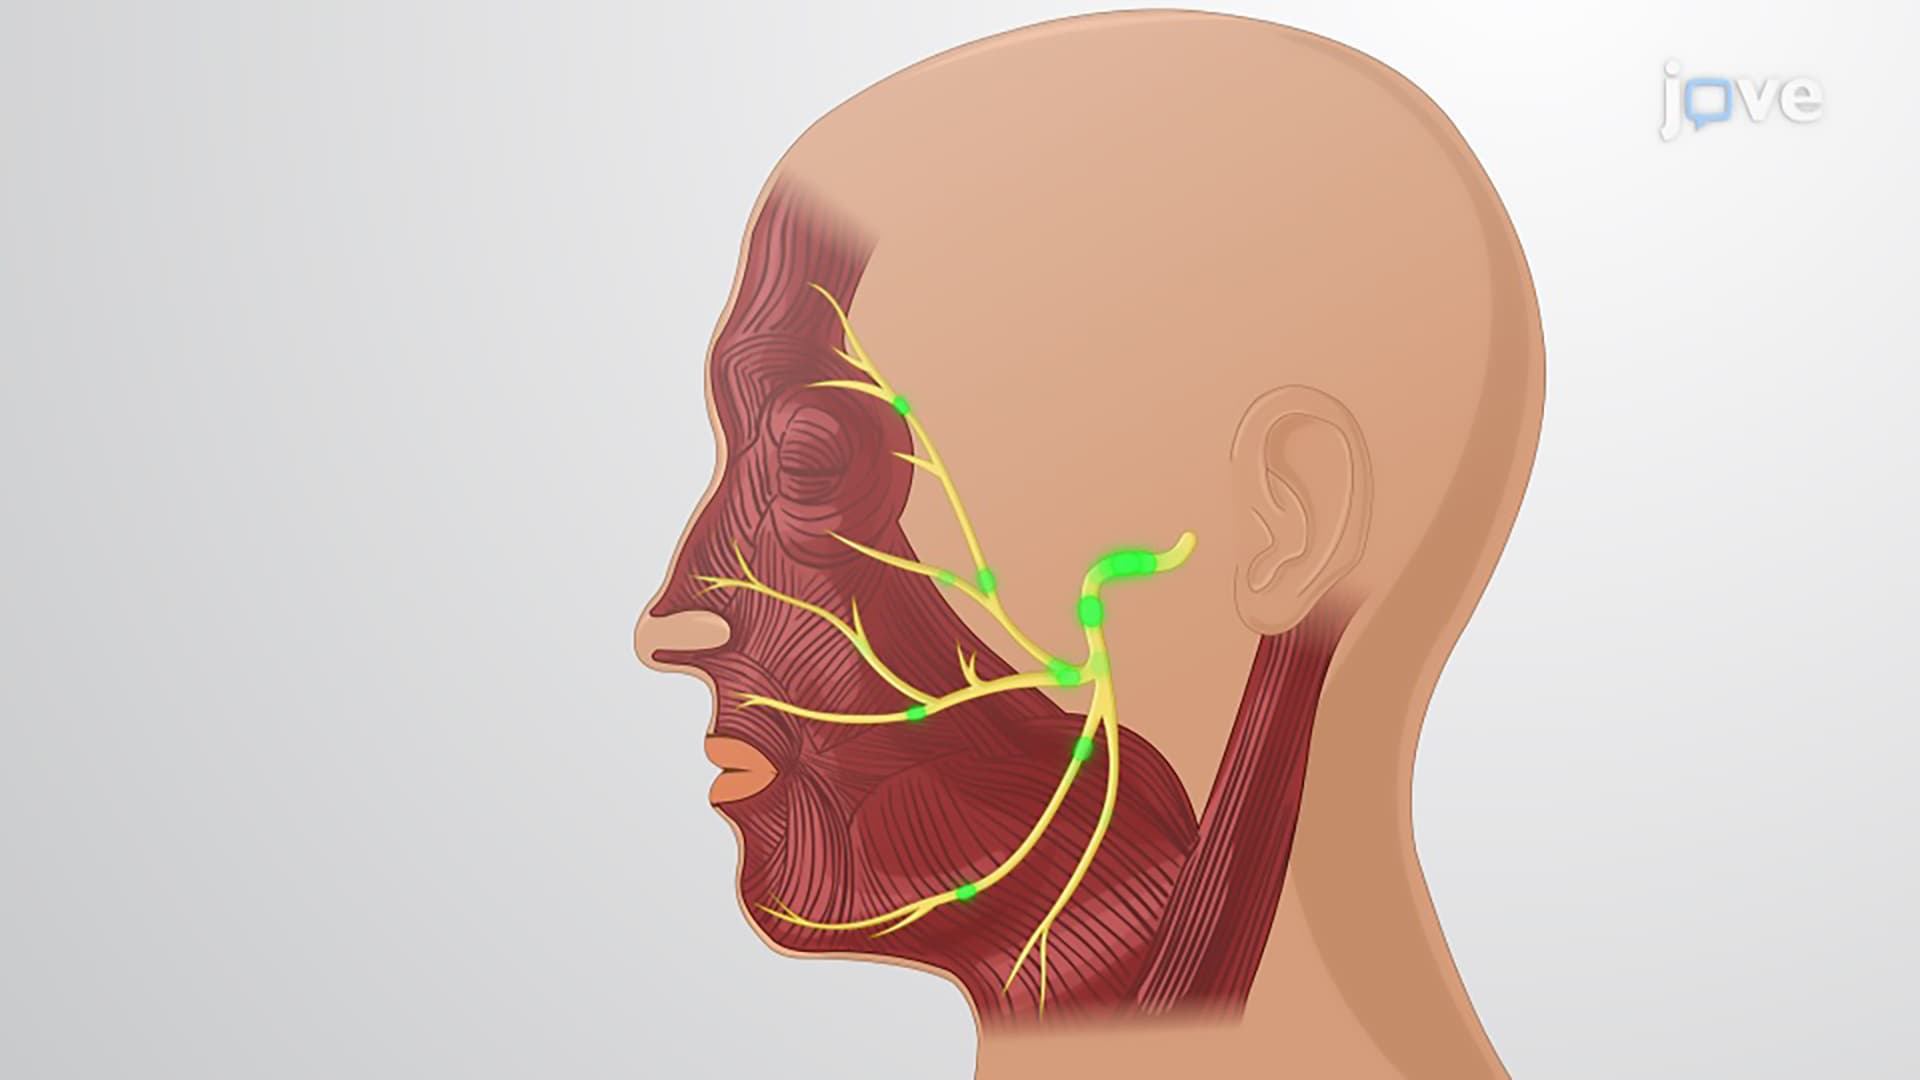 01:22
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:12
The Hyoid Bone