Related Experiment Video
Updated: May 10, 2026


Diagnosis of Neoplasia in Barrett’s Esophagus using Vital-dye Enhanced Fluorescence Imaging
Published on: May 11, 2014
A dominant adenocarcinoma with multifocal ground glass lesions does not behave as advanced disease
Bo Gu1, Bryan M Burt, Robert E Merritt
1Division of Thoracic Surgery, Department of Cardiothoracic Surgery, Stanford University School of Medicine, Stanford, California, USA.

Background:
Invasive lung adenocarcinomas increasingly present with synchronous, multifocal, in situ lesions that appear as ground glass opacities (GGOs). The optimal approach in this circumstance (often nonsmokers) remains unclear. We evaluated a general strategy of anatomic resection of the dominant tumor (DT) and wedge resection of accessible ipsilateral GGOs.
Methods:
This is a retrospective review of 39 patients with suspected multifocal in situ adenocarcinomas and 1 DT in a predominantly Caucasian population. Mean follow-up is 30.7 months.
Results:
Forty-nine percent of patients had no or minimal smoking history; 21% were Asian. The resected DT was pathologically "bronchioloalveolar carcinoma" (26%), minimally invasive adenocarcinoma (5%), adenocarcinoma with bronchioloalveolar features (41%), or moderate well-differentiated adenocarcinoma (28%). The p stage of the DT was IA in 20, IB in 15, and IIA in 4, with mean diameter of 2.6 cm. Thirty-two patients (82%) underwent anatomic resection of the DT; 7 (18%) underwent wedge resection. The mean number of GGOs present initially was 2.7 (range, 1 to 7) with a 5.2-mm mean diameter. An unresected nodule increased in size during follow-up in only 9 patients (23%). The mean diameter growth among these was 3.2 mm, with mean doubling time of 49 months. New GGOs (range, 1 to 8) developed in 16 patients (41%), all of which remained at 7 mm or less. Distant metastasis developed in 2 patients (5.2%); only 1 patient has required intervention for progression of a GGO. The overall survival is 100%.
Conclusions:
Patients with limited, multifocal, in situ adenocarcinomas and a clinical N0 DT enjoy prolonged survival with generally anatomic resection of the DT and wedge resection of accessible GGOs. These patients should not be considered to harbor T4 or M1a disease.

Related Concept Videos
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 02:30
Metastasis
Epithelial-to-Mesenchymal Transition
The epithelial-to-mesenchymal transition or EMT is a developmental process commonly observed in wound healing, embryogenesis, and cancer metastasis. EMT is induced by transforming growth factor-beta (TGF-β) or receptor tyrosine kinase (RTK) ligands, which further...
 01:24
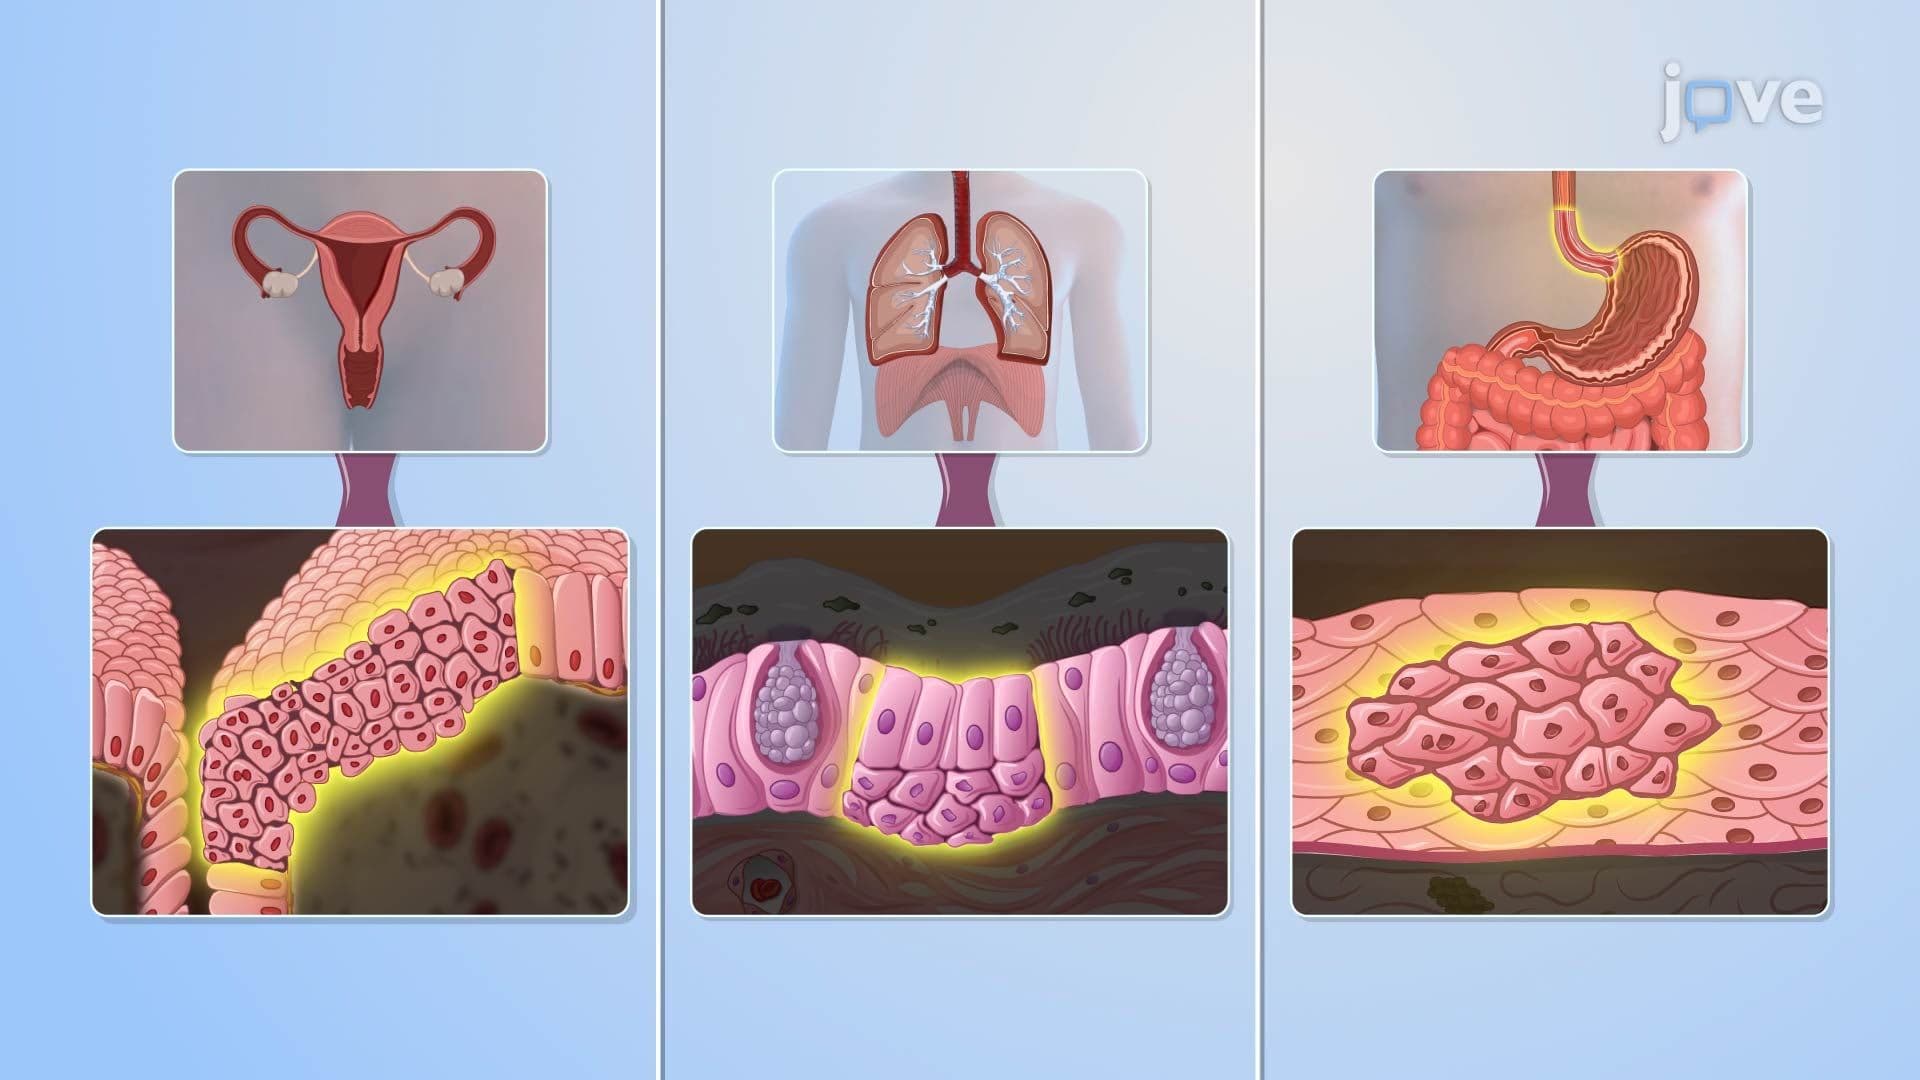
Cellular Adaptation IV: Dysplasia and Metaplasia