Related Experiment Video
Updated: May 10, 2026
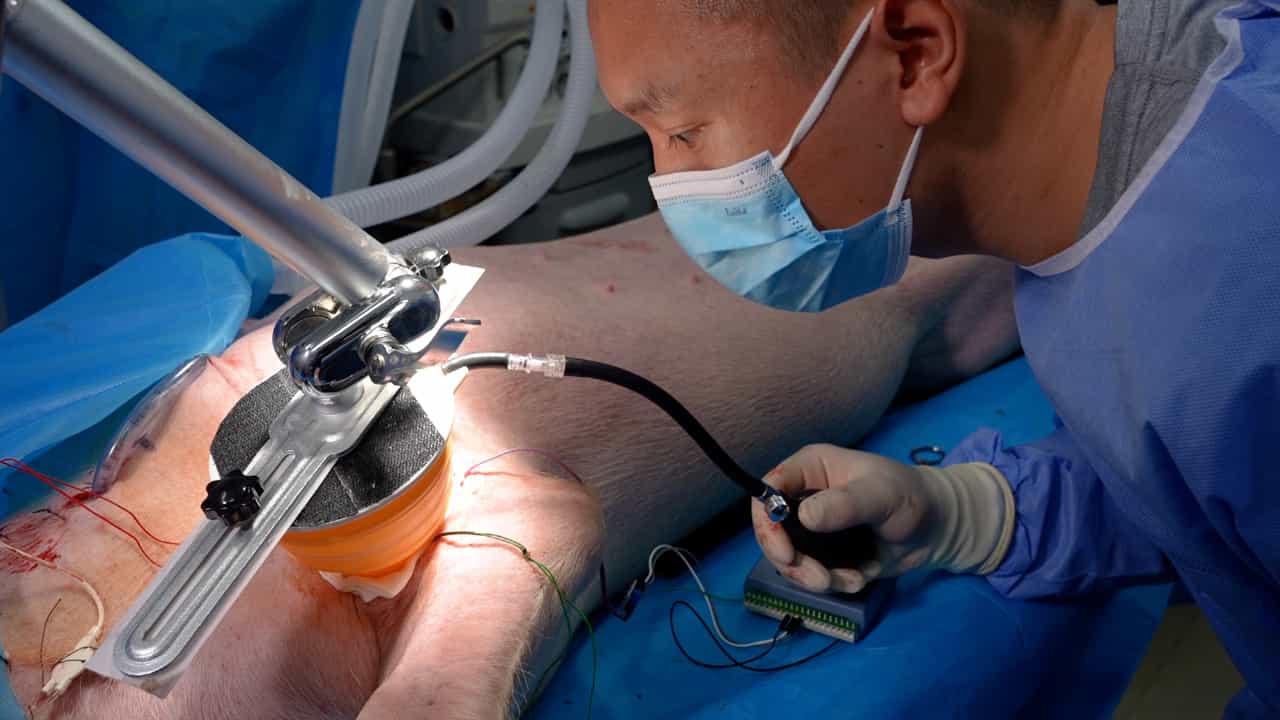
A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
Some hemostatic parameters in women with obstetric hemorrhage in Sokoto, Nigeria
O Erhabor1, Iz Isaac, Am Muhammad
1Department of Haematology and Transfusion Medicine, Usmanu Danfodio University, Sokoto, Bayelsa State, Nigeria.

Obstetric hemorrhage is the leading cause of maternal mortality and morbidity worldwide. This study was carried out to investigate the effect of obstetric hemorrhage on the prothrombin time (PT), activated partial thromboplastin time (APTT), and platelet count (PLC). Women with obstetric hemorrhage were divided into two categories, women with antepartum hemorrhage (APH) and those with postpartum hemorrhage (PPH). Pregnant women without hemorrhage were included as controls. Eighty-six pregnant women aged 18-45 years (mean age 36.25 ± 10.50 years) were presented to the Obstetrics and Gynaecology Department of Maryam Abacha Women and Children Hospital in Sokoto Metropolis, Sokoto State, Nigeria with history of obstetric hemorrhage. Forty-three age-matched nonhemorrhaging parturient women were included as controls. The determination of PT and APTT was done by manual methods using commercially prepared Diagen reagent kits, whereas PLC was done by manual methods using a hemocytometer. The results of PT and APTT were significantly higher among women with APH (20.7 ± 4.226 seconds and 46.04 ± 8.689 seconds, respectively) and among women with PPH (23.17 ± 2.708 seconds and 53.78 ± 4.089 seconds, respectively) compared to normal pregnant women (15.85 ± 0.8930 seconds and 36.225 ± 5.010 seconds, respectively) (P = 0.0001). Similarly, the PLC was significantly higher among normal pregnant women compared to those with APH and PPH (291.425 ± 75.980 × 10(9) compared to 154.83 ± 47.019 × 10(9) and 136.43 ± 43.894 × 10(9), respectively) (P = 0.0001). The PT and APTT of women who presented with PPH were significantly higher compared to those who presented with APH (23.17 ± 2.708 seconds and 53.78 ± 4.089 seconds versus 20.7 ± 4.226 seconds and 46.04 ± 8.689 seconds, respectively) (P = 0.02 and P = 0.04, respectively). The PLC was significantly higher among women who presented with APH compared to those who presented with PPH (P = 0.01). The PT and APTT values were higher in the third trimester among women with APH (24.38 ± 2.33 seconds and 52.25 ± 6.71 seconds, respectively), PPH (24.75 ± 2.63 seconds and 58.25 ± 2.53 seconds, respectively), and control women (16.00 ± 0.82 seconds and 34.42 ± 5.59 seconds, respectively) compared to those in first and second trimester. The PLC was significantly lower in the third trimester among APH, PPH, and normal pregnant women (131 ± 23.02 × 10(9), 99 ± 21.46 × 10(9), and 192.86 ± 25.44 × 10(9), respectively). PT and APTT values correlated positively and significantly with trimester (r = 0.52 and 0.65, respectively; P = 0.01). The PLC of women with APH, PPH, and normal control women correlated negatively with trimester (r = -0.36, -0.54, and -0.28, respectively; P = 0.05). Obstetrics hemorrhage compounded the hemostatic status of pregnant women in Sokoto, Nigeria. There is need for the provision of rapid diagnosis of coagulopathy to guide the provision of best therapeutic management options.
Obstetric hemorrhage is the leading cause of maternal mortality and morbidity worldwide. This study was carried out to investigate the effect of obstetric hemorrhage on the prothrombin time (PT), activated partial thromboplastin time (APTT), and platelet count (PLC). Women with obstetric hemorrhage were divided into two categories, women with antepartum hemorrhage (APH) and those with postpartum hemorrhage (PPH). Pregnant women without hemorrhage were included as controls. Eighty-six pregnant women aged 18-45 years (mean age 36.25 ± 10.50 years) were presented to the Obstetrics and Gynaecology Department of Maryam Abacha Women and Children Hospital in Sokoto Metropolis, Sokoto State, Nigeria with history of obstetric hemorrhage. Forty-three age-matched nonhemorrhaging parturient women were included as controls. The determination of PT and APTT was done by manual methods using commercially prepared Diagen reagent kits, whereas PLC was done by manual methods using a hemocytometer. The results of PT and APTT were significantly higher among women with APH (20.7 ± 4.226 seconds and 46.04 ± 8.689 seconds, respectively) and among women with PPH (23.17 ± 2.708 seconds and 53.78 ± 4.089 seconds, respectively) compared to normal pregnant women (15.85 ± 0.8930 seconds and 36.225 ± 5.010 seconds, respectively) (P = 0.0001). Similarly, the PLC was significantly higher among normal pregnant women compared to those with APH and PPH (291.425 ± 75.980 × 10(9) compared to 154.83 ± 47.019 × 10(9) and 136.43 ± 43.894 × 10(9), respectively) (P = 0.0001). The PT and APTT of women who presented with PPH were significantly higher compared to those who presented with APH (23.17 ± 2.708 seconds and 53.78 ± 4.089 seconds versus 20.7 ± 4.226 seconds and 46.04 ± 8.689 seconds, respectively) (P = 0.02 and P = 0.04, respectively). The PLC was significantly higher among women who presented with APH compared to those who presented with PPH (P = 0.01). The PT and APTT values were higher in the third trimester among women with APH (24.38 ± 2.33 seconds and 52.25 ± 6.71 seconds, respectively), PPH (24.75 ± 2.63 seconds and 58.25 ± 2.53 seconds, respectively), and control women (16.00 ± 0.82 seconds and 34.42 ± 5.59 seconds, respectively) compared to those in first and second trimester. The PLC was significantly lower in the third trimester among APH, PPH, and normal pregnant women (131 ± 23.02 × 10(9), 99 ± 21.46 × 10(9), and 192.86 ± 25.44 × 10(9), respectively). PT and APTT values correlated positively and significantly with trimester (r = 0.52 and 0.65, respectively; P = 0.01). The PLC of women with APH, PPH, and normal control women correlated negatively with trimester (r = -0.36, -0.54, and -0.28, respectively; P = 0.05). Obstetrics hemorrhage compounded the hemostatic status of pregnant women in Sokoto, Nigeria. There is need for the provision of rapid diagnosis of coagulopathy to guide the provision of best therapeutic management options.
Related Concept Videos
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:17
Hemorrhagic Stroke l: Introduction