Related Experiment Video
Updated: Aug 15, 2026

Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Prone positioning in infant gastroesophageal reflux: is elevation of the head worth the trouble?
1Division of Pediatric Gastroenterology, University of Pittsburgh School of Medicine, Pennsylvania.

Insights
Head-elevated prone positioning offers minimal benefit for infant gastroesophageal reflux. Studies show it slightly reduces reflux episode frequency but doesn't significantly improve overall reflux duration or fasting period measures.
Area of Science:
- Pediatrics
- Gastroenterology
Background:
- Gastroesophageal reflux is common in infants.
- Prone positioning is sometimes used to manage reflux.
- The efficacy of head-elevated versus flat prone positioning is debated.
Purpose of the Study:
- To compare head-elevated prone positioning with flat prone positioning for infants experiencing gastroesophageal reflux.
- To evaluate the impact of positioning on esophageal pH probe measurements.
Main Methods:
- A crossover study involving 100 infants under 6 months with suspected reflux.
- Infants underwent intraluminal esophageal pH monitoring in both head-elevated and flat prone positions.
- Measurements included reflux episode frequency, duration, and longest episode during postprandial and fasting periods.
Main Results:
- Head elevation showed a statistically significant reduction in postprandial reflux episode frequency (p<0.05) and episodes longer than 5 minutes (p<0.005).
- No significant differences were observed in total postprandial reflux duration or any fasting period reflux measures.
- Among infants with abnormal reflux, no position demonstrated a significant advantage across 10 pH probe measurements.
Conclusions:
- Head-elevated prone positioning provides limited benefits for infant gastroesophageal reflux.
- The marginal improvements do not appear to justify the additional effort required for maintaining this position.
- Further research may be needed to explore alternative or adjunctive reflux management strategies.
Abstract:
To determine whether head-elevated prone positioning is better than flat prone positioning for infants with gastroesophageal reflux, we studied 100 babies less than 6 months of age who were being examined for reflux with an intraluminal esophageal pH probe while the babies were in each of the two positions, with the use of a crossover design protocol. During both a 2-hour postprandial period and a fasting period, pH probe measurements in each position included (1) minutes with pH less than 4, (2) number of episodes with pH less than 4, (3) mean duration of such episodes, (4) number of such episodes longer than 5 minutes, and (5) the duration of the longest episode. Significant reductions with head elevation were found for only two of these 10 values: the frequency of reflux episodes postprandially (7.5 +/- 0.7 vs 5.9 +/- 0.5 episodes per 2 hours; p less than 0.05) and the frequency of episodes longer than 5 minutes postprandially (1.4 +/- 0.1 vs 1.2 +/- 0.1 episodes per 2 hours; p less than 0.005). There was no significant reduction in the total duration of postprandial reflux nor in any measure of reflux during the fasting period. The 90 infants in whom an abnormal degree of gastroesophageal reflux was documented had no significant differences between flat prone and head-elevated prone position for any of the 10 pH probe measurements. Head-elevated prone positioning is probably not worth the extra effort required to maintain it.


Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:29
Gastroesophageal Reflux Disease I: Meaning and Pathophysiology
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
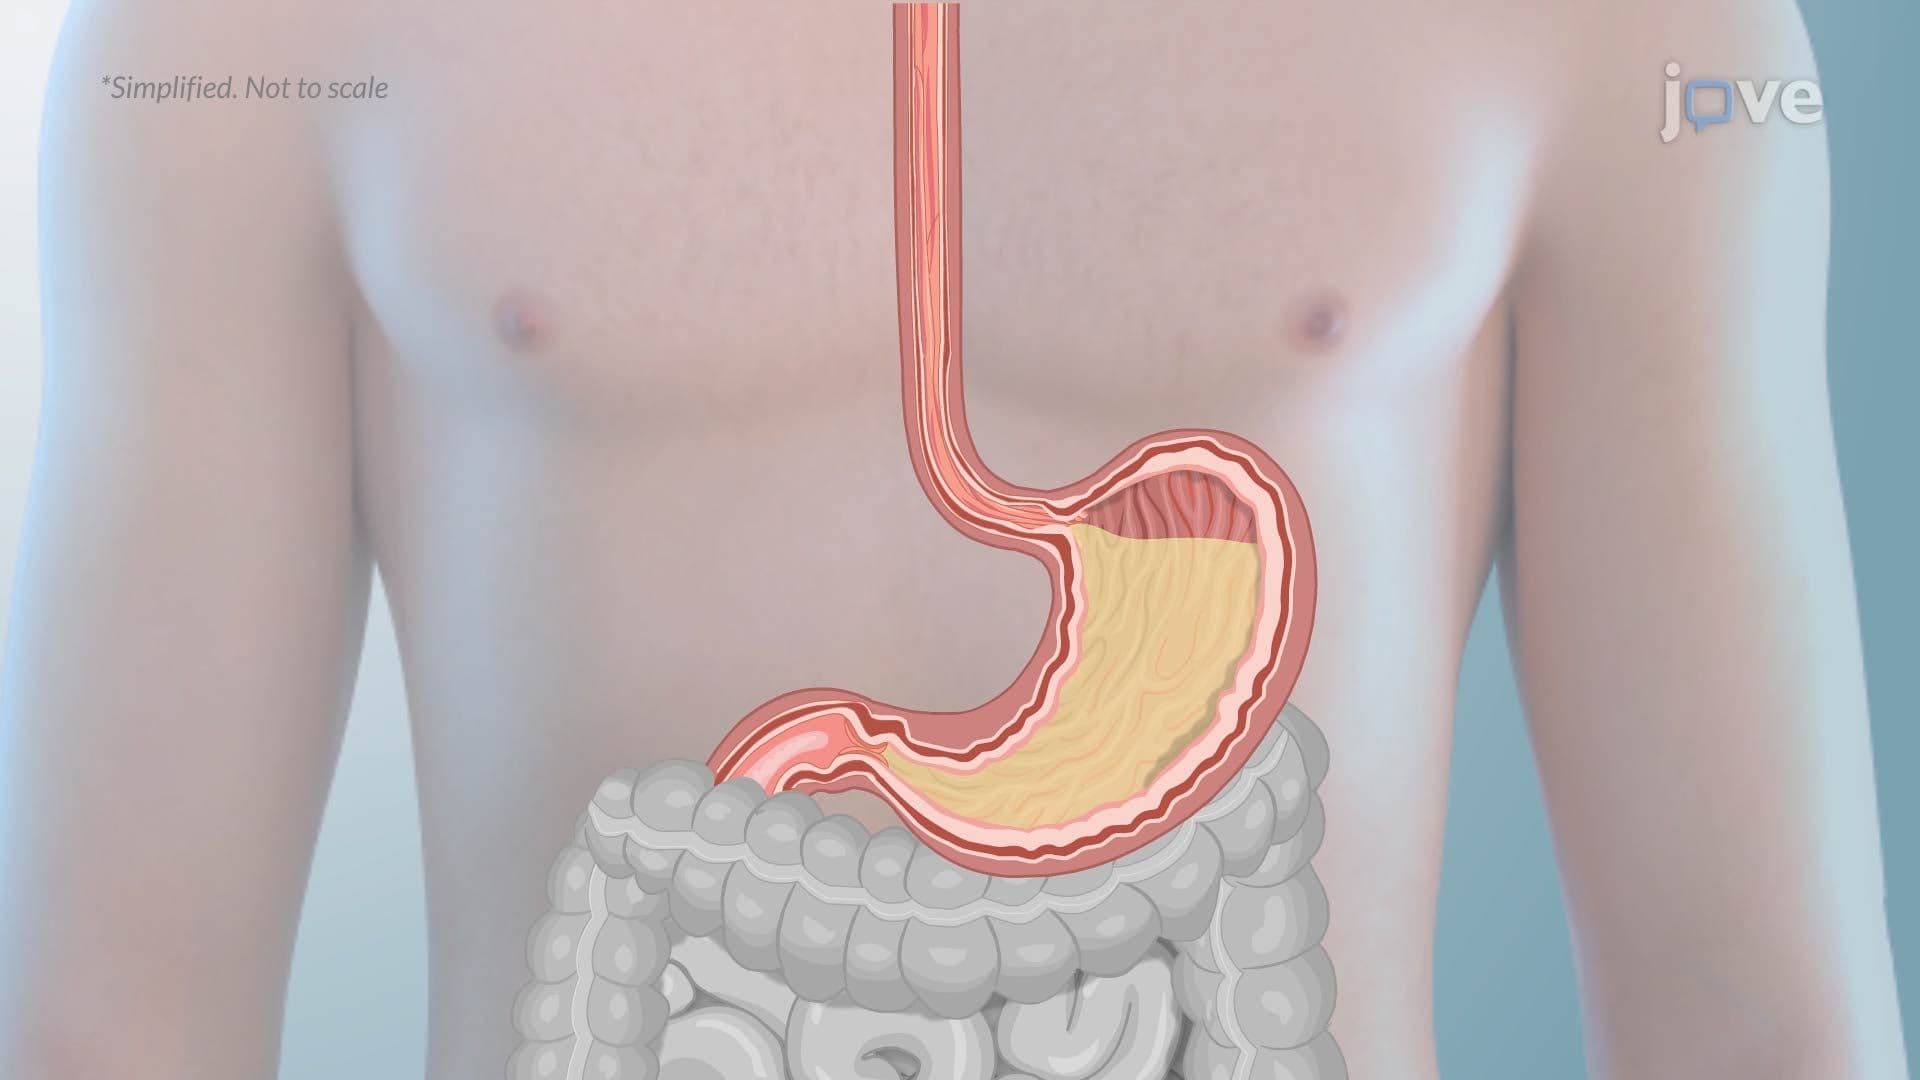
Gastroesophageal Reflux Disease
 01:25
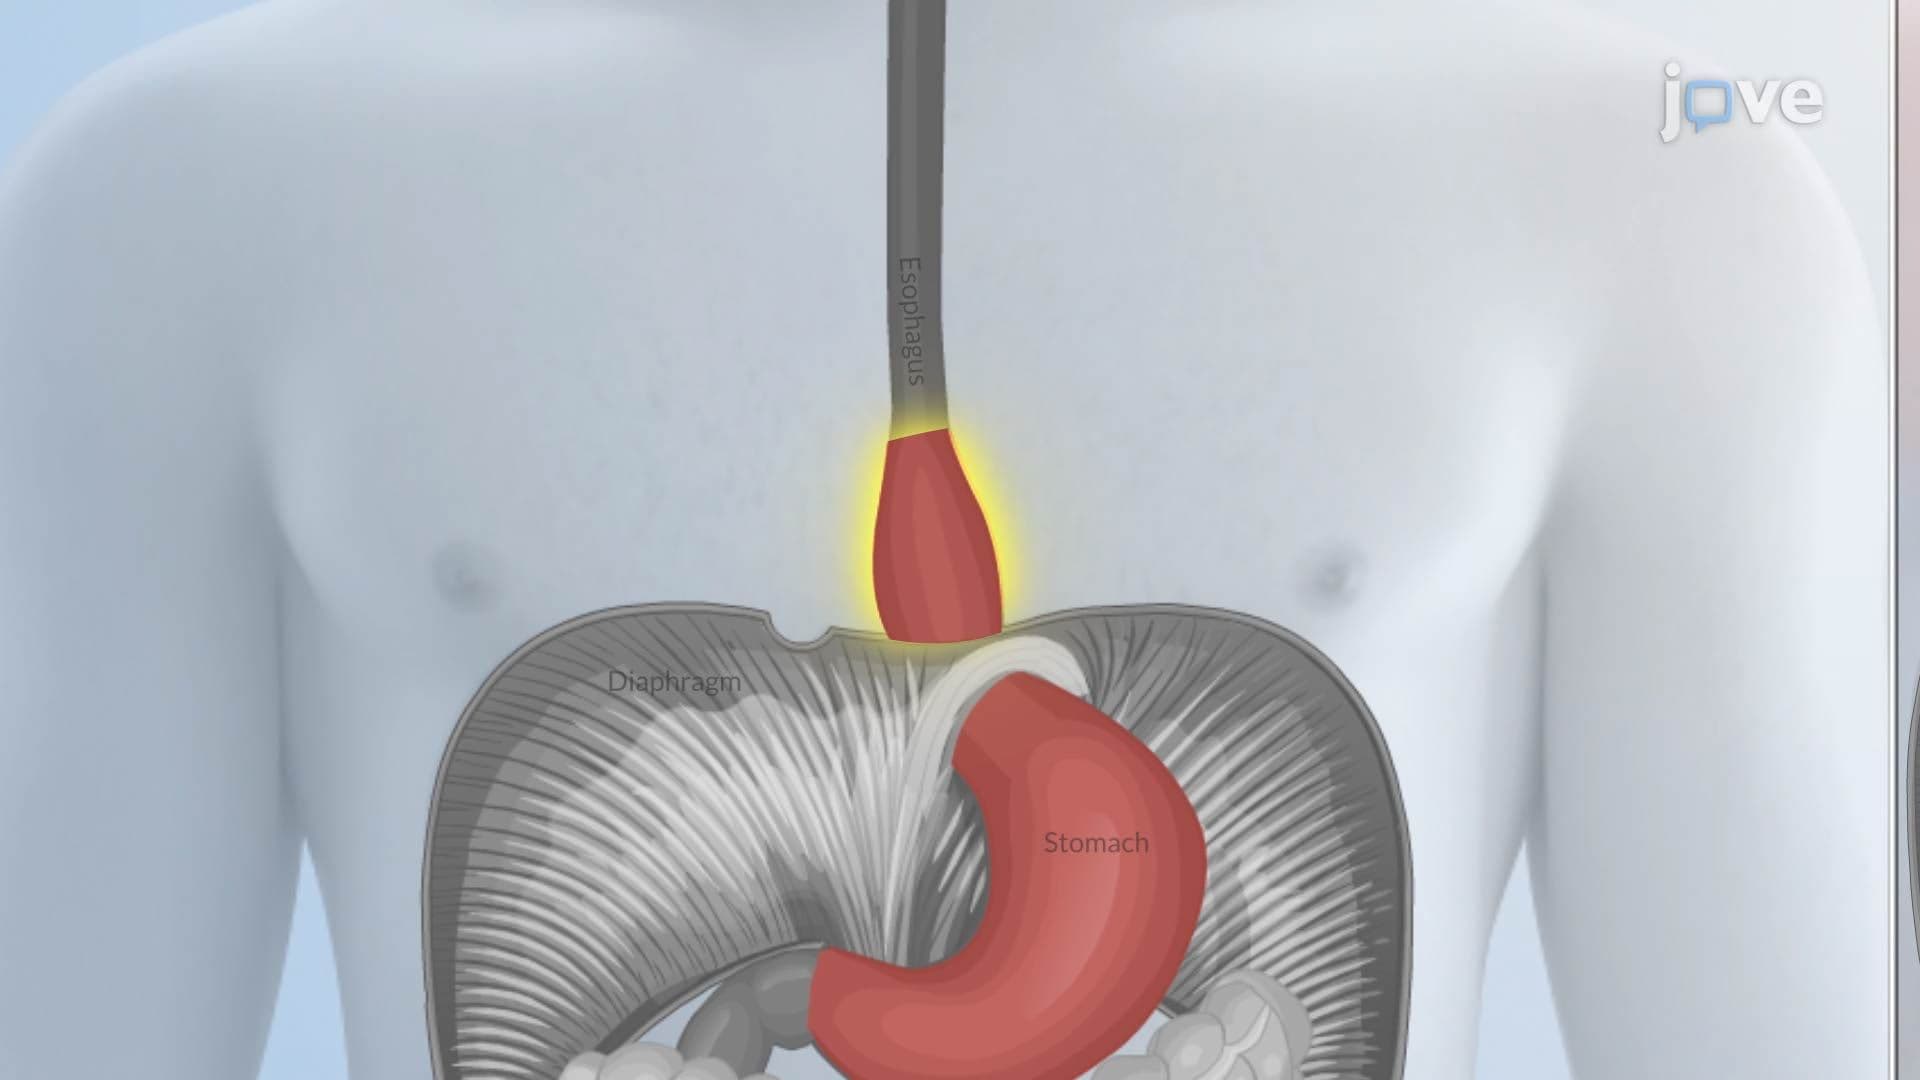
Hiatal Hernia