Related Experiment Video
Updated: May 10, 2026
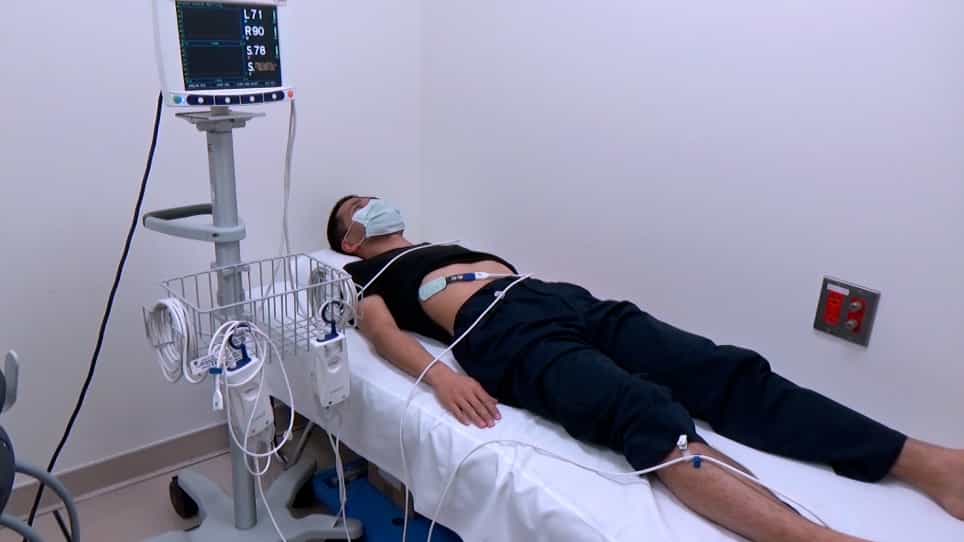
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Patient care staffing levels and facility characteristics in U.S. hemodialysis facilities
Laura A G Yoder1, Wenjun Xin, Keith C Norris
1University of Virginia School of Nursing, Charlottesville, VA.

Background:
Higher numbers of registered nurses (RNs) per patient have been associated with improved patient outcomes in acute-care facilities. Variation in and associations of patient care staffing levels and hemodialysis facility characteristics have not been examined previously.
Study Design:
Cross-sectional study using Poisson regression to examine associations between patient care staffing levels and hemodialysis facility characteristics.
Setting & Participants:
4,800 US hemodialysis facilities in the 2009 Centers for Medicare & Medicaid (CMS) End-Stage Renal Disease Annual Facility Survey (CMS-2744 form).
Predictors:
Facility characteristics, including profit status, freestanding status, chain affiliation, and geographic region, adjusted for facility size, capacity, functional type, and urbanicity.
Outcomes:
Patient care staffing levels, including ratios of RNs, licensed practical nurses (LPNs), patient care technicians (PCTs), composite staff (RN + LPN + PCT), social workers, and dietitians to in-center hemodialysis patients.
Results:
After adjusting for background facility characteristics, ratios of RNs and LPNs to patients were 35% (P < 0.001) and 42% (P < 0.001) lower, respectively, but the PCT to patient ratio was 16% (P < 0.001) higher in for-profit than nonprofit facilities (rate ratios of 0.65 [95% CI, 0.63-0.68], 0.58 [95% CI, 0.51-0.65], and 1.16 [95% CI, 1.12-1.19], respectively). Regionally, compared to the Northeast, the adjusted RN to patient ratio was 14% (P < 0.001) lower in the Midwest, 25% (P < 0.001) lower in the South, and 18% (P < 0.001) lower in the West. Even after additional adjustments, the large for-profit chains had significantly lower RN and LPN to patient ratios than the largest nonprofit chain, but a significantly higher PCT to patient ratio. Overall composite staffing levels also were lower in for-profit and chain-affiliated facilities. The patterns hold when hospital-based units were excluded.
Limitations:
Nursing hours were not available. Two part-time staff were counted as one full-time equivalent, which may not always be accurate.
Conclusions:
The significant variation in patient care staffing levels and its associations with facility characteristics warrants inclusion in future large-scale hemodialysis outcomes studies. End-stage renal disease networks and hemodialysis facilities should attend to quality assurance and performance improvement initiatives that maximize licensed nurse staffing levels in hemodialysis facilities.

Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis I: Introduction
 01:25
Peritoneal Dialysis III: Nursing Management
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis