Related Experiment Video
Updated: May 10, 2026


Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
Published on: January 29, 2014
Abnormalities in the alternative pathway of complement in children with hematopoietic stem cell transplant-associated
Sonata Jodele1, Christoph Licht, Jens Goebel
1Division of Bone Marrow Transplantation and Immune Deficiency, Cincinnati Children's Hospital Medical Center, Cincinnati, OH;

Hematopoietic stem cell transplant (HSCT)-associated thrombotic microangiopathy (TMA) is a complication that occurs in 25% to 35% of HSCT recipients and shares histomorphologic similarities with hemolytic uremic syndrome (HUS) and thrombotic thrombocytopenic purpura (TTP). The hallmark of all thrombotic microangiopathies is vascular endothelial cell injury of various origins, resulting in microangiopathic hemolytic anemia, platelet consumption, fibrin deposition in the microcirculation, and tissue damage. Although significant advances have been made in understanding the pathogenesis of other thrombotic microangiopathies, post-HSCT TMA remains poorly understood. We report an analysis of the complement alternative pathway, which has recently been linked to the pathogenesis of both the Shiga toxin mediated and the atypical forms of HUS, with a focus on genetic variations in the complement Factor H (CFH) gene cluster and CFH autoantibodies in six children with post-HSCT TMA. We identified a high prevalence of deletions in CFH-related genes 3 and 1 (delCFHR3-CFHR1) and CFH autoantibodies in these patients with HSCT-TMA. Conversely, CFH autoantibodies were not detected in 18 children undergoing HSCT who did not develop TMA. Our observations suggest that complement alternative pathway dysregulation may be involved in the pathogenesis of post-HSCT TMA. These findings shed light on a novel mechanism of endothelial injury in transplant-TMA and may therefore guide the development of targeted treatment interventions.
Hematopoietic stem cell transplant (HSCT)-associated thrombotic microangiopathy (TMA) is a complication that occurs in 25% to 35% of HSCT recipients and shares histomorphologic similarities with hemolytic uremic syndrome (HUS) and thrombotic thrombocytopenic purpura (TTP). The hallmark of all thrombotic microangiopathies is vascular endothelial cell injury of various origins, resulting in microangiopathic hemolytic anemia, platelet consumption, fibrin deposition in the microcirculation, and tissue damage. Although significant advances have been made in understanding the pathogenesis of other thrombotic microangiopathies, post-HSCT TMA remains poorly understood. We report an analysis of the complement alternative pathway, which has recently been linked to the pathogenesis of both the Shiga toxin mediated and the atypical forms of HUS, with a focus on genetic variations in the complement Factor H (CFH) gene cluster and CFH autoantibodies in six children with post-HSCT TMA. We identified a high prevalence of deletions in CFH-related genes 3 and 1 (delCFHR3-CFHR1) and CFH autoantibodies in these patients with HSCT-TMA. Conversely, CFH autoantibodies were not detected in 18 children undergoing HSCT who did not develop TMA. Our observations suggest that complement alternative pathway dysregulation may be involved in the pathogenesis of post-HSCT TMA. These findings shed light on a novel mechanism of endothelial injury in transplant-TMA and may therefore guide the development of targeted treatment interventions.

Related Concept Videos
 01:27
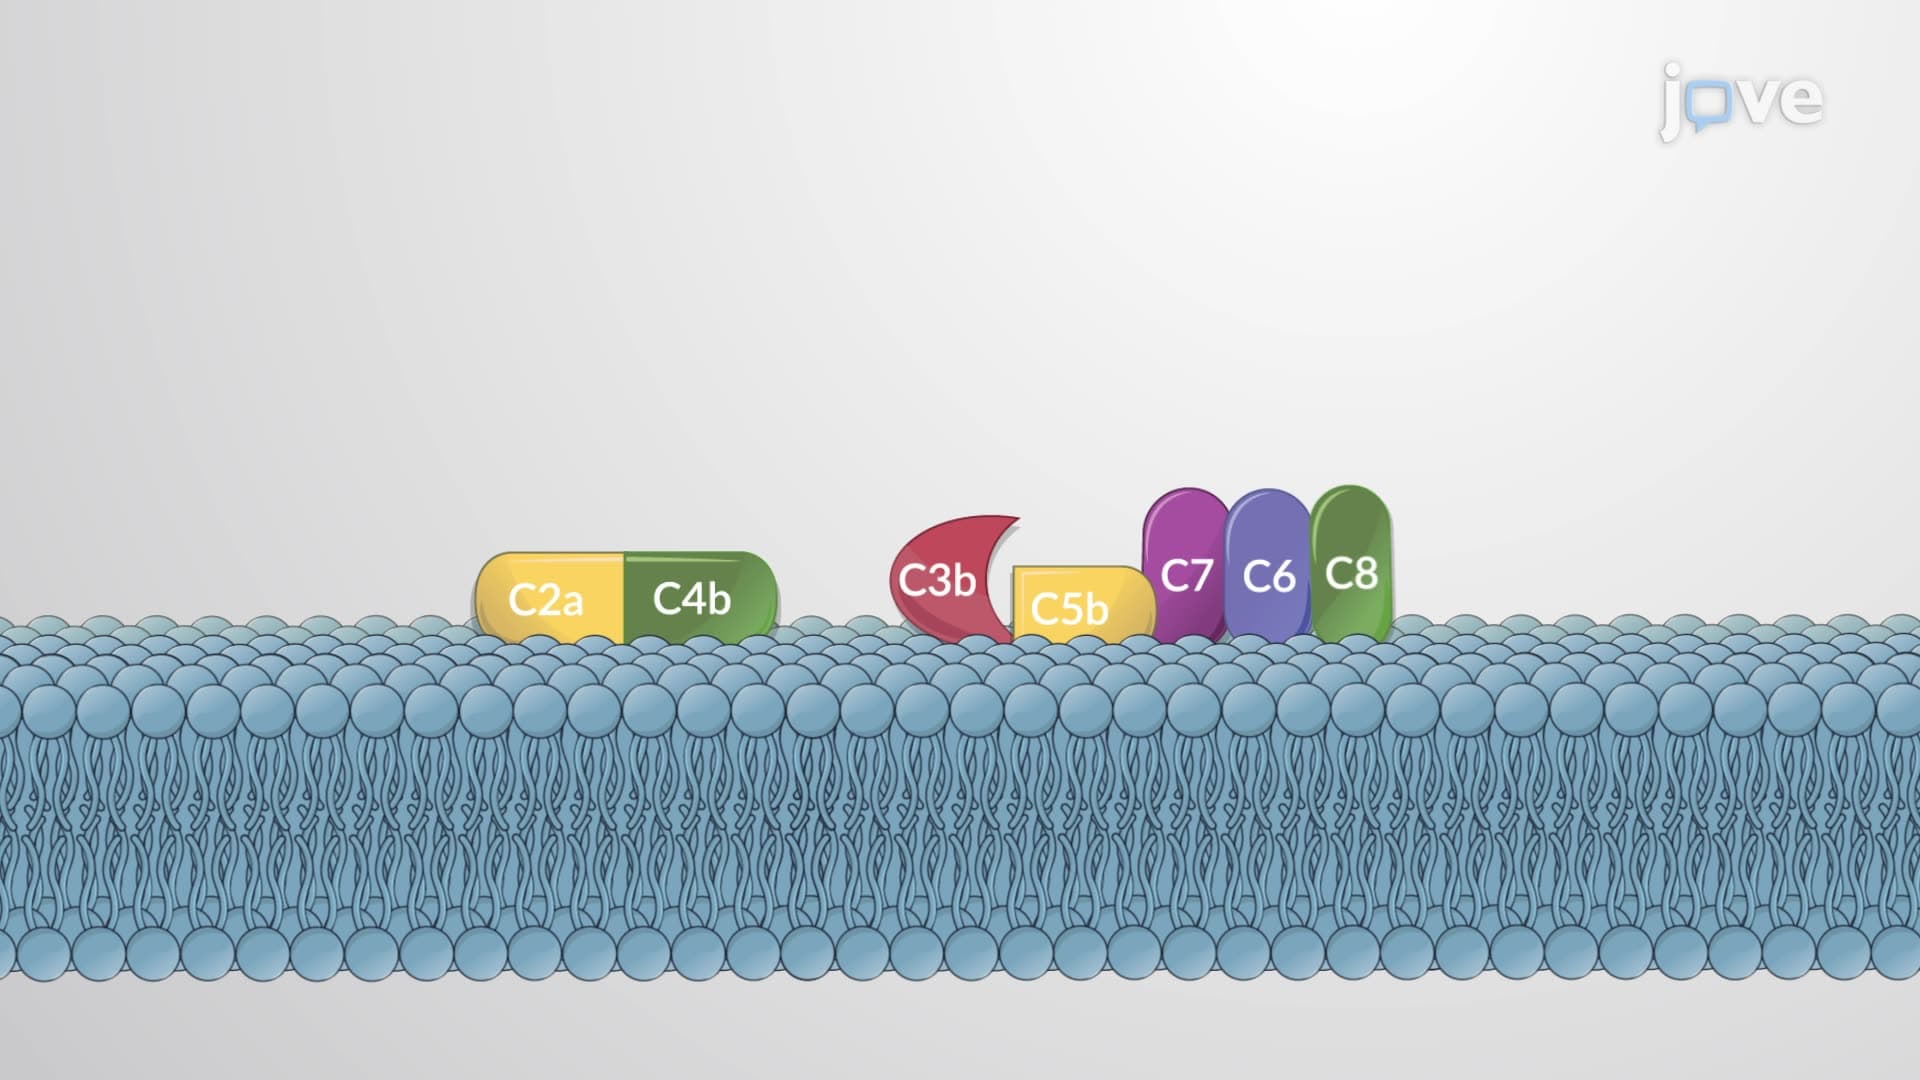
Complement System
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...