Related Experiment Video
Updated: May 10, 2026
A Simple and Rapid Method for Simultaneous Isolation of Primary Islets and Primary Pancreatic Acinar Cells from Mice
Published on: January 9, 2026
Evolution in the diagnosis and treatment of autoimmune pancreatitis: experience from a single tertiary care center
Alper Yurci1, Tyler Stevens, Shetal N Shah
1Digestive Disease Institute, Cleveland Clinic, Cleveland, Ohio 44195, USA.

Background:
Autoimmune pancreatitis (AIP) is a recently characterized disease with specific clinical, radiographic, and histological features. These diagnostic features have been codified in the recently revised HISORt criteria. The aim of this study was to determine how the recognition and management of AIP has evolved at our center since the publication of the HISORt criteria in 2006.
Methods:
We conducted a historical cohort study consisting of patients with AIP based on the revised HISORt criteria seen at our tertiary care center since 1990. Cases were identified from pathology, laboratory, and pancreas clinic databases. The medical records were reviewed to ascertain demographic and clinical characteristics, radiologic and laboratory results, and patient outcomes. When available, prior images and pathology slides were retrospectively reviewed. The clinical outcomes of the patients were assessed following surgical or medical treatment, and compared based on the calendar year of presentation (before or after 2006).
Results:
Forty-seven cases were identified based on the revised HISORt criteria. Of these, 22 were evaluated before and 25 after January 1, 2006. In the early cohort, the diagnosis was frequently missed, including 15 patients that underwent surgical resections. None from the early cohort had a serum IgG4 drawn or mention of possible AIP in the imaging reports. When histology was obtained, the surgical pathologist did not perform IgG4 or Movat stain to allow a histological diagnosis of AIP. Several patients developed diabetes (n=3), calcific pancreatitis with exocrine insufficiency (n=3), proximal biliary strictures (n=7), and pancreatic cancer (n=1) during follow-up. In contrast, patients in the late cohort were less likely to undergo a surgical resection that the early cohort (36% vs. 68%, p=0.042). They were more likely to have a serum IgG4 drawn (80% vs. 0%) and to undergo a corticosteroid trial (44% vs. 0%, p=0.0003). 10/11 patients (92%) who underwent corticosteroid trials had resolution of their symptoms and improvement in structural abnormalities on imaging.
Conclusion:
A growing multidisciplinary awareness of AIP has led to improved diagnostic evaluation, prompter diagnosis, fewer surgical resections, and more frequent corticosteroid trials.


Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
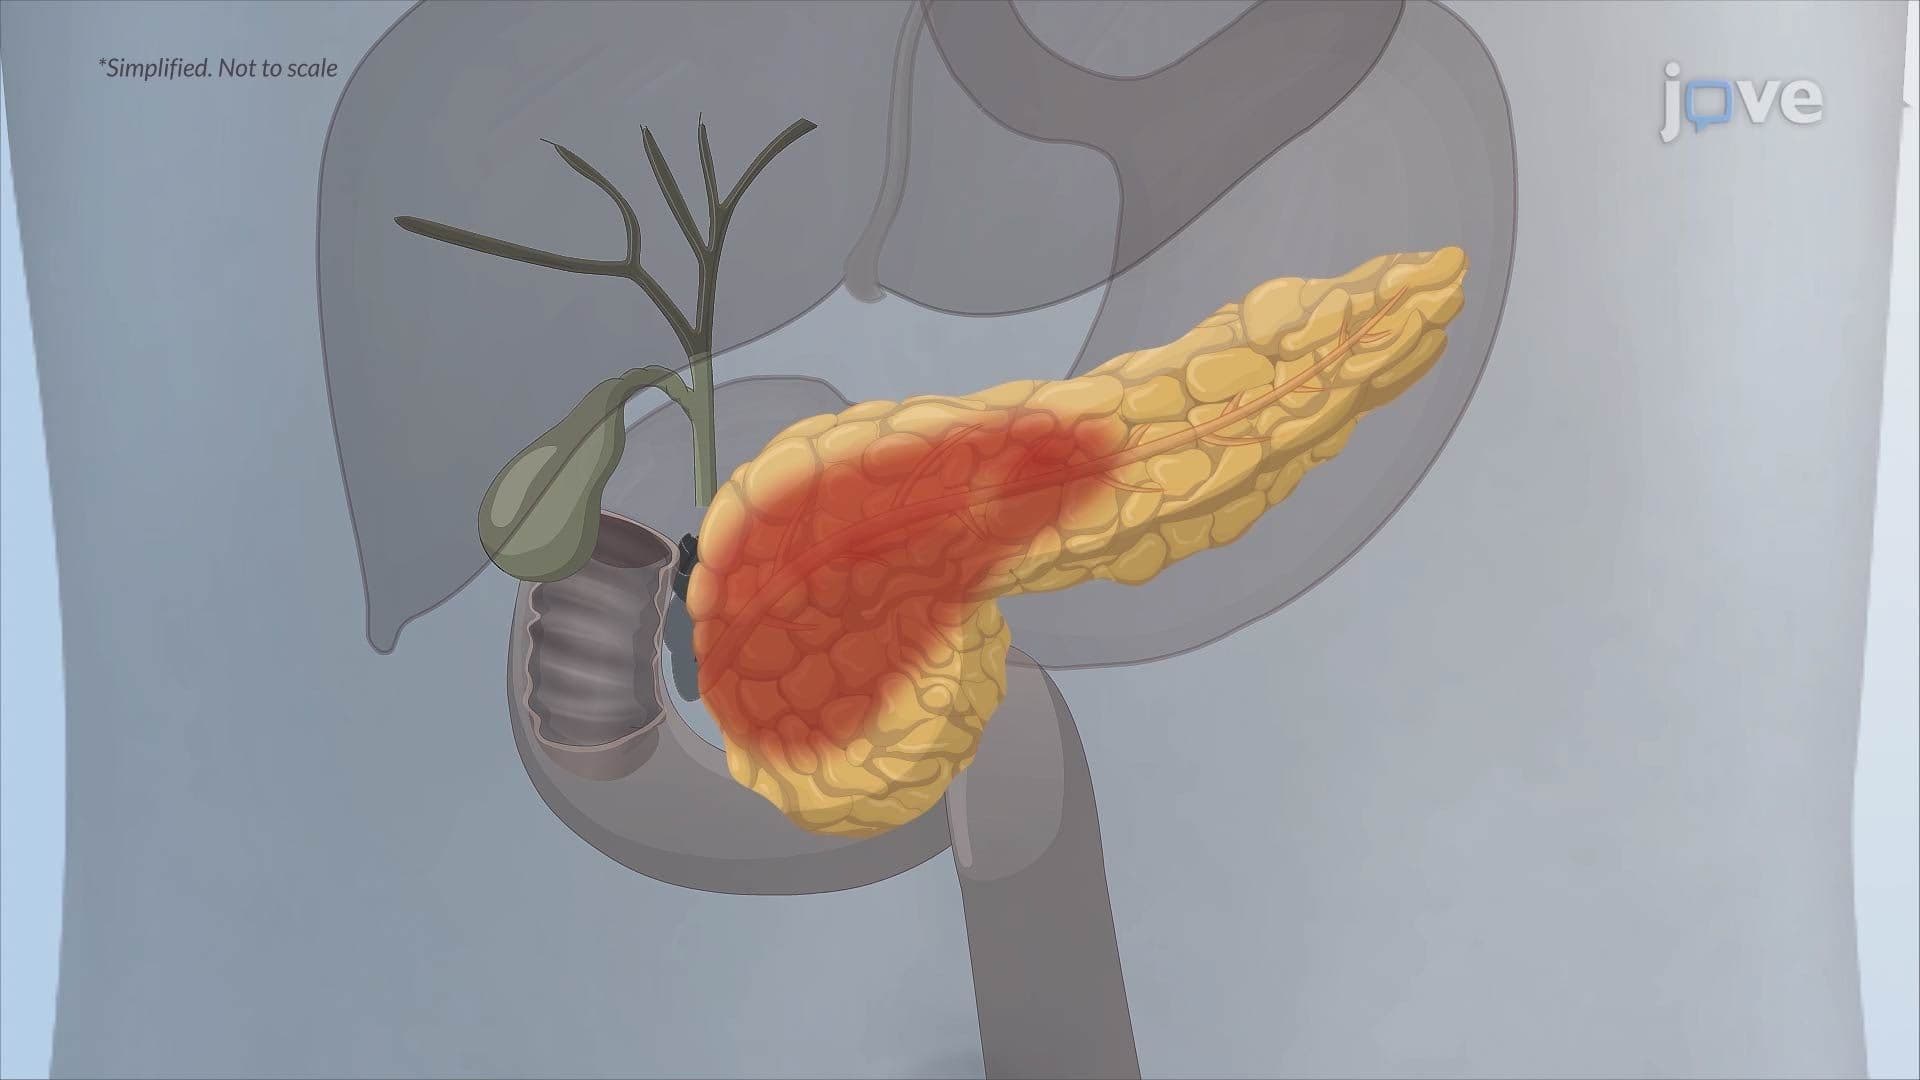
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: