Ruptured temporal lobe arachnoid cyst presenting with severe back pain
Related Experiment Video
Updated: May 10, 2026
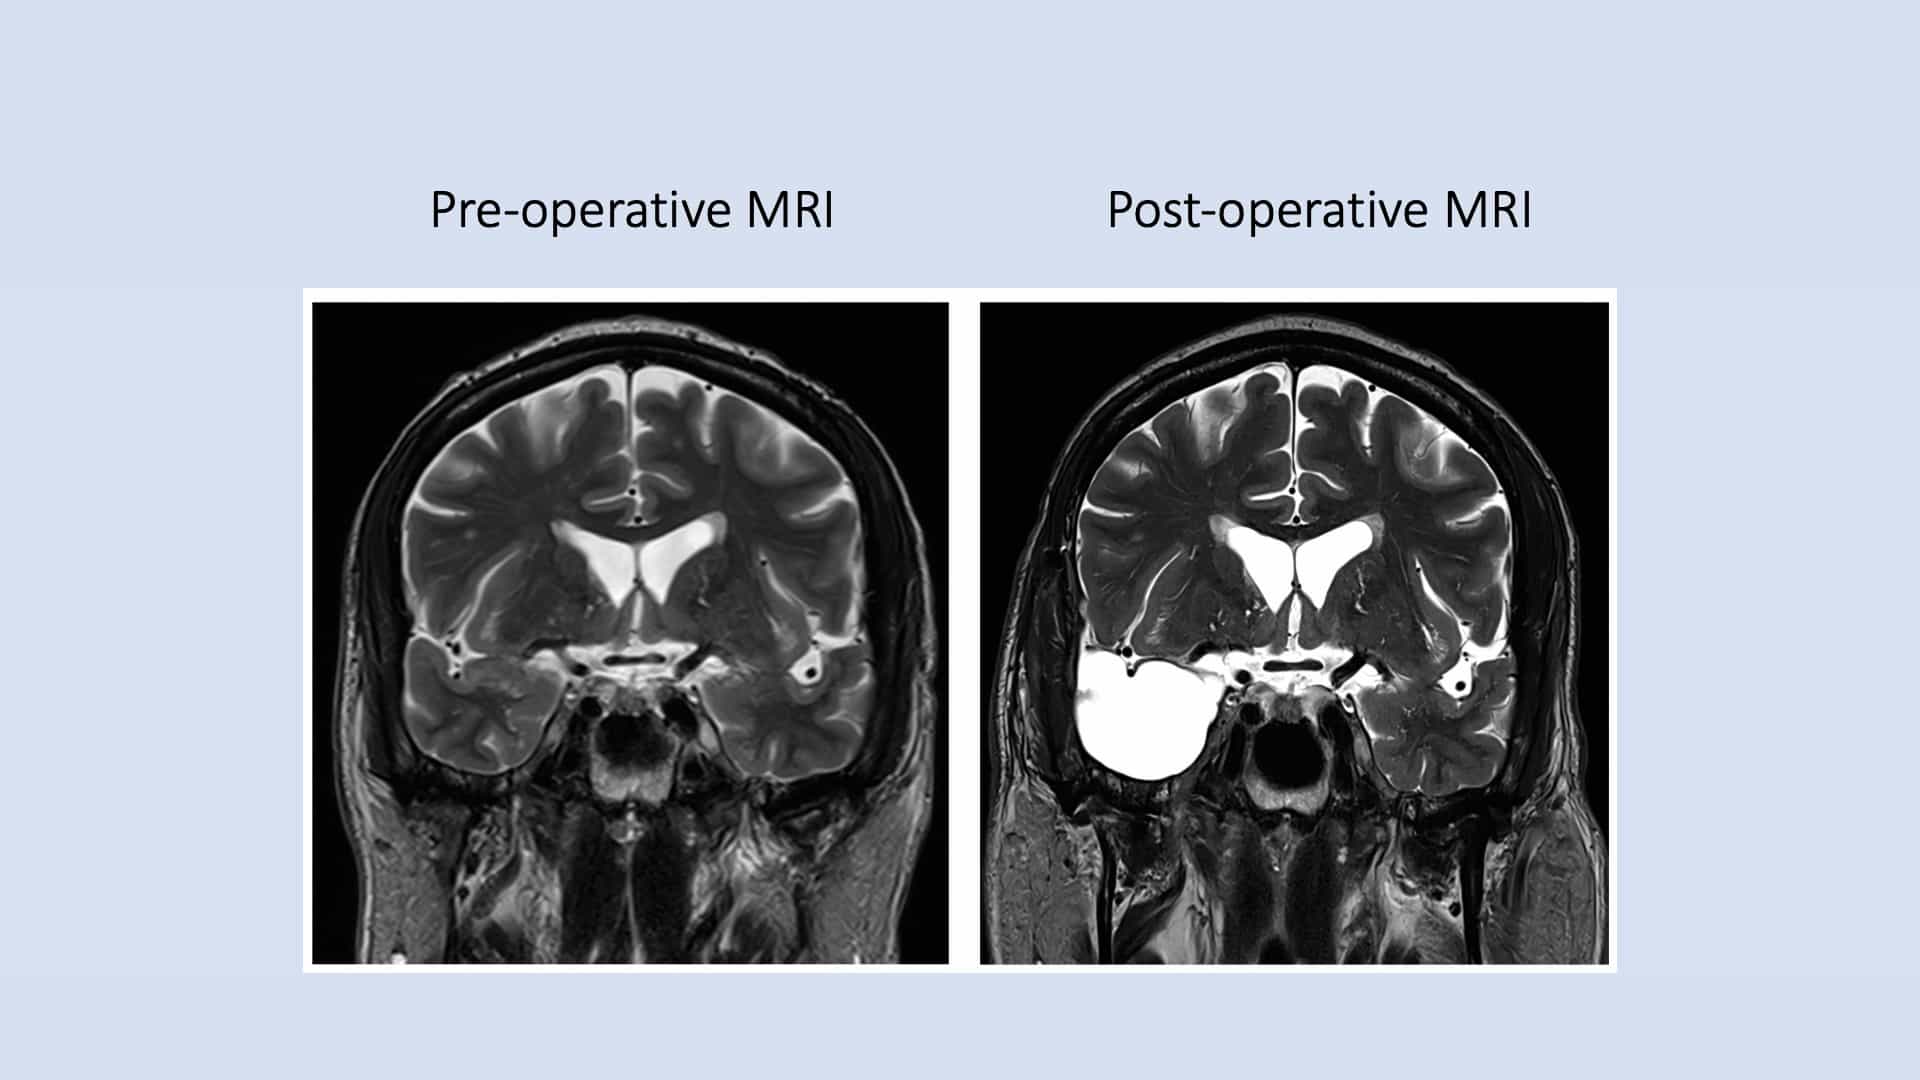
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Subash Lohani1, Richard L Robertson, Mark R Proctor
1Department of Neurosurgery, Boston Children’s Hospital, Massachusetts, USA. subash.lohani@childrens.harvard.edu

Insights
A pediatric arachnoid cyst ruptured, causing spinal and cranial subdural hematomas. Steroid treatment resolved symptoms and imaging findings, avoiding surgery.
Area of Science:
- Neurology
- Pediatrics
- Neurosurgery
Background:
- Arachnoid cysts are common congenital anomalies in children, often asymptomatic but capable of causing symptoms like headaches.
- Rupture of arachnoid cysts, particularly after trauma, can lead to subdural hematomas.
Observation:
- An 11-year-old boy presented with severe back and leg pain.
- Imaging revealed a spinal subdural blood collection and a sylvian fissure arachnoid cyst with intracystic hemorrhage and frontoparietal subdural hematoma.
Findings:
- Intracystic hemorrhage and subdural hematomas associated with a pediatric arachnoid cyst.
- Successful non-surgical management with oral steroids.
- Resolution of cranial and spinal subdural collections and cyst size reduction.
Implications:
- This case highlights a rare presentation of a pediatric arachnoid cyst rupture.
- Non-surgical management with steroids can be effective for associated subdural hematomas.
- Early diagnosis and conservative treatment may prevent surgical intervention in select cases.
Abstract:
Arachnoid cyst is a common congenital anomaly in the pediatric population. The cysts are often asymptomatic, but they can cause headache and other symptoms. Occasionally a cyst may rupture after head trauma producing a subdural hematoma. The authors present the case of an 11-year-old boy who presented after a week of progressive and severe back pain radiating to the back of his thighs. Imaging revealed a spinal subdural blood collection at the L4-S1 level. This finding prompted further cephalad imaging of the spine and the brain, which revealed a sylvian fissure arachnoid cyst with intracystic hemorrhage and frontoparietal subdural hematoma. The child did not have headache at this time, although he had experienced chronic headaches since the age of 4 years. He was treated with a course of oral steroids, which immediately relieved his back and leg pain. Subsequent imaging showed resolution of the cranial and spinal subdural blood collections and diminished size of the arachnoid cyst. No surgical treatment was necessary.
Related Concept Videos
 01:26
Brain Abscess l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:22
Bacterial Meningitis I: Introduction
 01:29
Herniated Intervertebral Disc l: Introduction