Related Experiment Video
Updated: May 9, 2026

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Relationship between volume and survival in closed intensive care units is weak and apparent only in mechanically
Rafael Fernández1, Susana Altaba, Lluis Cabre
1* Director, Intensive Care Unit, Fundació Althaia, Manresa, CIBERES, Universitat Internacional de Catalunya, Barcelona, Spain. † Intensive Care Unit, Hospital G.U., Castello, Castello, Spain. ‡ Intensive Care Unit, Hospital de Barcelona SCIAS, Barcelona, Spain. § Intensive Care Unit, Hospital de Sagunt, Sagunt, Spain. ‖ Intensive Care Unit, C.Hosp.U. de Santiago de Compostela, Santiago de Compostela, Spain. # Intensive Care Unit, Hospital del Mar, Barcelona, Spain. ** Intensive Care Unit, Hospital Virgen de la Luz, Cuenca, Spain. †† Intensive Care Unit, C. Hosp. de Vic, Vic, Spain. ‡‡ Intensive Care Unit, Hospital San Agustin, Aviles, Spain. §§ Intensive Care Unit, Hospital Mateu Orfila, Menorca, Spain. ‖‖ Intensive Care Unit, Hospital Moncloa, Madrid, Spain. ## Intensive Care Unit, Hospital U. Carlos Haya (Hospital Civil), Malaga, Spain. *** Intensive Care Unit, Hospital Virgen de las Nieves, Granada, Spain. ††† Statistical Department, Fundació Parc Taulí, Corporació Sanitaria Universitaria Parc Taulí, Universidad Autònoma de Barcelona, Sabadell, Spain. ‡‡‡ Members of the Sabadell Score Group are listed in the appendix. Hospital Xeral Cies, Vigo, Spain Hospital de Salamanca, Salamanca, Spain Clinica Universitaria de Navarra, Navarra, Spain Hospital Virgen Macarena, Sevilla, Spain Hospital Virgen de la Victoria, Malaga, Spain Hospital Son Llatzer, Mallorca, Spain Hospital Universitario de Getafe, Getafe, Spain, CIBER Enfermedades Respiratorias Hospital Severo Ochoa, Leganes, Spain Hospital Reina Sofia, Murcia, Spain Hospital Virgen de la Concha, Zamora, Spain Hospital Sant Joan de Reus, Reus, Spain Hospital Reina Sofia, Cordoba, Spain Hospital de Cruces, Baracaldo, Spain Hospital Morales Messeguer, Murcia, Spain Hospital General Yague, Burgos, Spain Hospital Universitario de A Coruña, A Coruña, Spain Hospital La Fe, Valencia, Spain Hospital Marques de Valdecilla, Santander, Spain Hospital Infanta Sofia, San Sebastian de los R

Background:
Recent studies have found an association between increased volume and increased intensive care unit (ICU) survival; however, this association might not hold true in ICUs with permanent intensivist coverage. Our objective was to determine whether ICU volume correlates with survival in the Spanish healthcare system.
Methods:
Post hoc analysis of a prospective study of all patients admitted to 29 ICUs during 3 months. At ICU discharge, the authors recorded demographic variables, severity score, and specific ICU treatments. Follow-up variables included ICU readmission and hospital mortality. Statistics include logistic multivariate analyses for hospital mortality according to quartiles of volume of patients.
Results:
The authors studied 4,001 patients with a mean predicted risk of death of 23% (range at hospital level: 14-46%). Observed hospital mortality was 19% (range at hospital level: 11-35%), resulting in a standardized mortality ratio of 0.81 (range: 0.5-1.3). Among the 1,923 patients needing mechanical ventilation, the predicted risk of death was 32% (14-60%) and observed hospital mortality was 30% (12-61%), resulting in a standardized mortality ratio of 0.96 (0.5-1.7). The authors found no correlation between standardized mortality ratio and ICU volume in the entire population or in mechanically ventilated patients. Only mechanically ventilated patients in very low-volume ICUs had slightly worse outcome.
Conclusion:
In the currently studied healthcare system characterized by 24/7 intensivist coverage, the authors found wide variability in outcome among ICUs even after adjusting for severity of illness but no relationship between ICU volume and outcome. Only mechanically ventilated patients in very low-volume centers had slightly worse outcomes.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:15
Respiratory Volumes
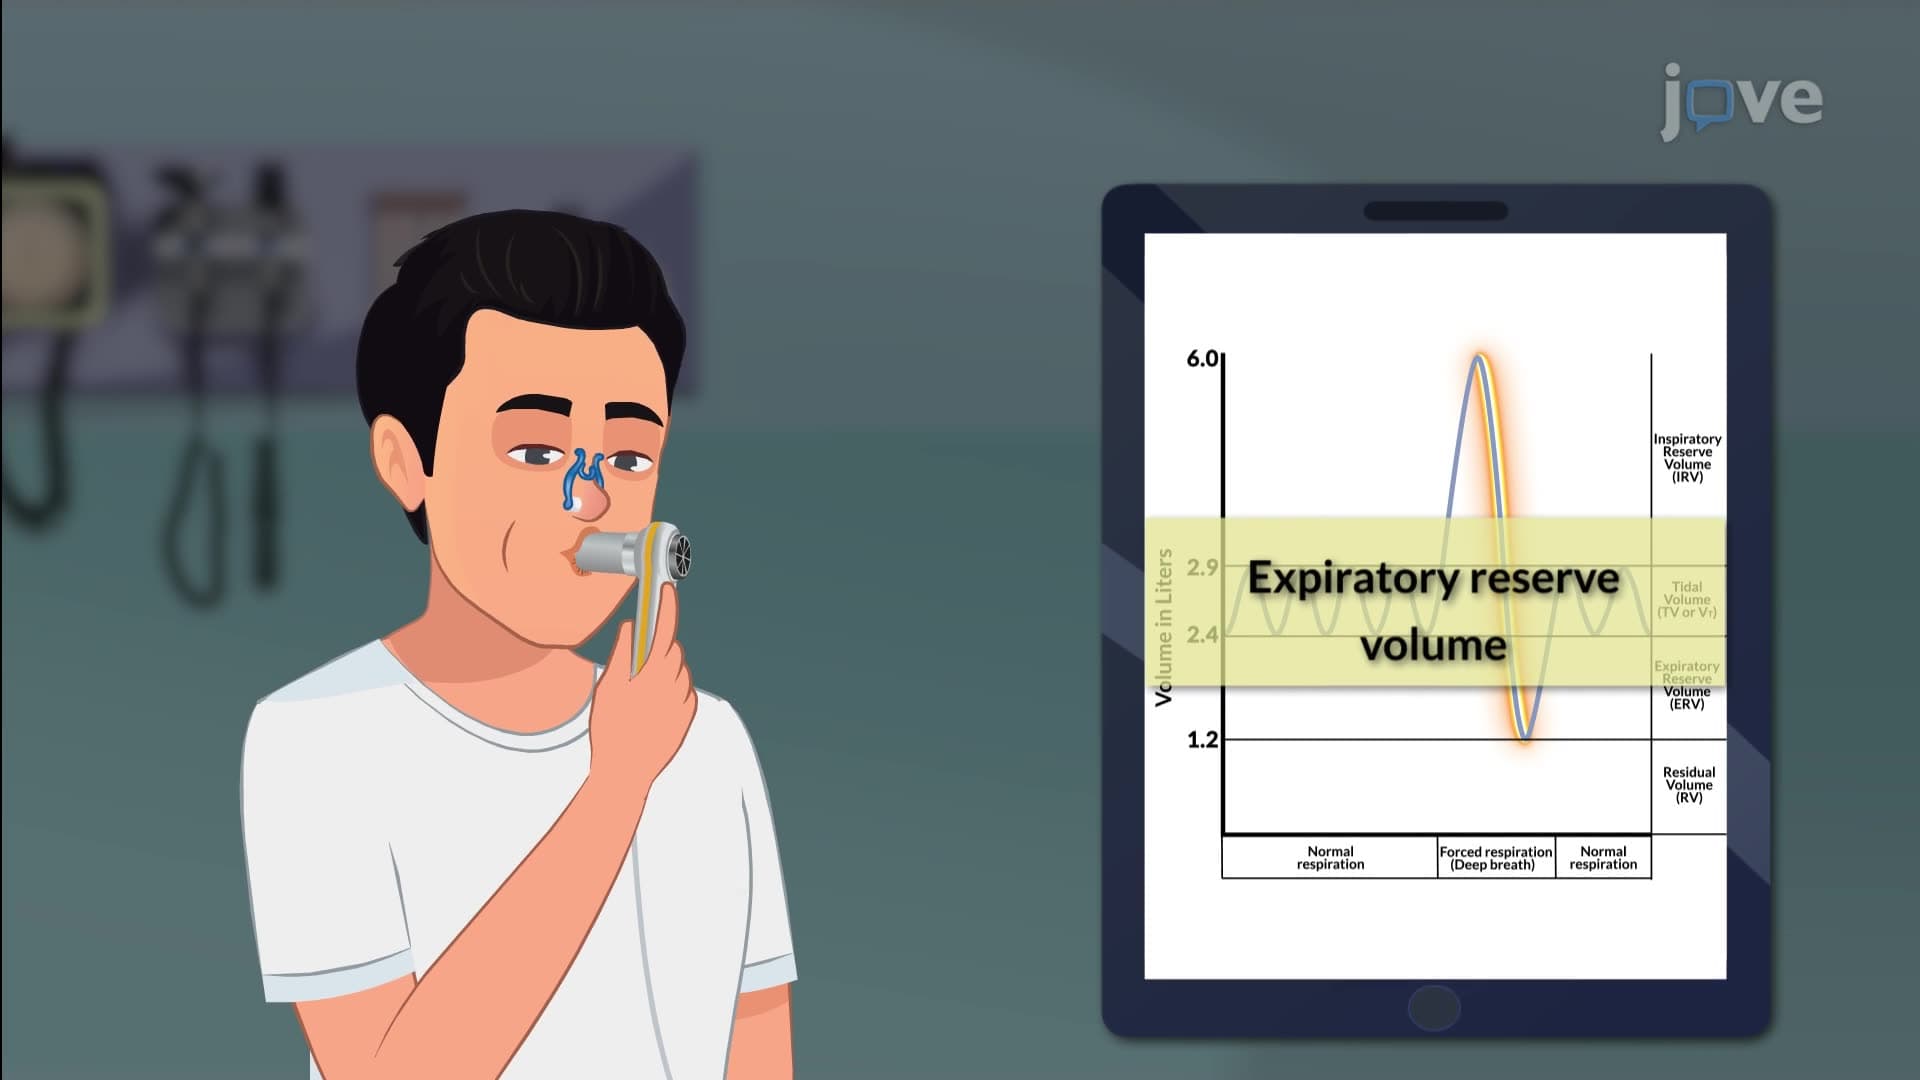
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:22
Respiratory Volumes and Capacities
 01:29
Mechanical Ventilation I: Indication and Settings